Why Anti-parasitics are not such a good idea for COVID: Better untapped ways

With the reported rise of mutants with increased transmissibility and potential immune escape supported by epidemiological and clinical data, the search for a panacea which will cover all strains of SARS-CoV-2 has become a frenzied pursuit. Such haste and grasping any favorable observations, no matter how tenuous, have inundated social media, the press, and placed undue pressure on medical institutions to modify and scale back their warnings about such unsubstantiated treatments and prophylactics, https://www.nytimes.com/interactive/2021/health/coronavirus-mutations-B117-variant.html. The problem is balancing the specific with the non-specific. The former decreases adverse side effects, such as anaphylaxis and Guillain-Barré syndrome (GBS; neurological weakness and paralysis), but is subject to mutation leading to neutralization of effectiveness. The 1976 flu vaccine, I took while in the military and which was falsely associated with GBS, rose public concern and misconceptions and fears because of a historic small increase in GBS risk associated with the vaccine, which was later found to be lower than initially thought. Concerns about vaccine-related GBS risk persist despite comprehensive surveillance of influenza vaccine-related increases showing only one additional case of GBS per million flu vaccinations. In contrast, the risk of flu-related complications is 17 per million cases. A recent study showed no link between COVID-19 and Guillain-Barré syndrome https://www.cidrap.umn.edu/news-perspective/2020/12/study-finds-no-link-between-covid-19-guillain-barr-syndrome and https://academic.oup.com/brain/advance-article/doi/10.1093/brain/awaa433/6031905. The most common trigger for GBS is infection with Campylobacter jejuni, a bacterium that causes gastroenteritis, or infection of the digestive tract, the most common cause of food borne illness. Therefore, benefits of vaccination far outweigh the risks. The use of broad spectrum, non-specific potential treatments have more adverse side effects associated with them, and diluted effectiveness.

What are we up against? Three mutants V367F, W436R, and D364Y, have arisen in Wuhan, Shenzhen, Hong Kong, and France, which have demonstrated higher human ACE2 affinity. This is because of enhanced stabilization of the receptor binding protein (receptor binding domain, RBD). High frequencies of RBD mutations have been identified: V367F with five mutations from France and one Hong Kong mutant, V483A, and G476S mutant from the USA. Lineage B.1.1.7 (also called 501Y.V1) is rapidly spreading in southeastern England. It has 17 mutations which developed prior to its detection in early September 2020, which indicates prior evolution, possibly in a chronically infected patient. B.1.1.7 expanded when SARS-CoV-2 cases were widespread and achieved dominance by outcompeting an existing population of circulating virus, natural selection of virus more transmissible. Dr. Joel Ernst, an infectious disease expert at UCSF, has stated the B.1.1.7 UK variant has been found in 22 states so far, including 72 cases in California, according to the Centers for Disease Control and Prevention.

The variant in South Africa was first detected in Nelson Mandela Bay in samples dating back to the beginning of October 2020. South Africa showed a sharp rise in the number of infected during November 2020, and reported 501Y.V2 to the World Health Organization on 18 Dec 2020. More than 1.3 million people have been infected with the virus in South Africa, highest of any African nation, more than 37,000 South Africans have died from COVID-19. Most new infections are caused by the 501Y.V2 variant.

Mutations have significantly changed the South African virus’ spike protein; the spike protein has now rotated about twenty degrees and can therefore get more deeply into the binding site on cells; thus, the virus can bind better to human cells, enabling it to become a more efficient virus for transmission. The South Africa variant is about 50% more contagious than the original strain. The Western Cape region took 107 days to reach 100,000 cases in the first wave compared to 54 days in the second wave, when the variant appeared. The South African variant has spread to 14 countries. The director of the Centers for Disease Control and Prevention said, 29 Jan 2021, that the South African Covid-19 variant, which was just detected in two people in South Carolina, had already reached the point of community spread in the U.S. On 9 Jan 2021, Japan notified WHO of a new SARS-CoV-2 variant B.1.1.28 detected in 4 travelers from Brazil. This variant has 12 mutations to the spike protein, including 3 mutations in common with 501Y.V2, ie, K417N/T, E484K and N501Y, which potentially can change transmissibility and host immune responses. Brazil has also reported emergence of a similar variant, with E484K mutation, which evolved independently of the variant from the travelers.

By mid January 2021, Dr. Charles Chiu, director of the UCSF-Abbott Viral Diagnostics and Discovery Center, from sequencing results from his lab at UCSF, found a rare variant, that Chiu had only seen in a handful of samples, suddenly jump up to 25% in his samples. Chiu’s team was the first to report the new variant, now called L452R, but within days, diagnosticians at Cedars-Sinai reported the same variant was now making up more than a third of cases in Los Angeles.

These variants suggest specific antiviral measures may be sidestepped by their changes if the measures are targeted too specifically to an antigen. I stated this in an earlier post about monoclonal antibody driving escape mutations by selection pressure. This has been borne out by recent clinical studies. Treatment with bamlanivimab and etesevimab, monoclonal anti-spike antibodies to different epitope targets, of nonhospitalized patients with mild to moderate COVID-19 illness, compared with placebo, showed statistically significant decrease in SARS-CoV-2 viral load at day 11; however, no significant reduction in viral load was seen with bamlanivimab monotherapy. The South African strain has also demonstrated escape from such treatment. It has been observed to completely escape from three monoclonal antibodies, reported by scientists from three South African universities, with the National Institute for Communicable Diseases (NICD), in a paper published on the bioRxiv website (https://bit.ly/2Y0lHEt). In addition, 501Y.V2 showed substantial or complete escape from neutralizing antibodies from COVID-19 convalescent plasma. They concluded reinfection could occur, and the differences in the variant may lead to reduced efficacy of current spike-based vaccines (New COVID-19 Variant Defeats Plasma Treatment, MABs, May Reduce Vaccine Efficacy – Medscape – Jan 20, 2021). Such Dior predictions, have led individuals and physicians to pursue broad-spectrum treatments which make such variations irrelevant.

Didier Raoult’s tarnished claim hydroxychloroquine and azithromycin were effective against COVID-19 has not completely died because of this need for a generalized treatment, even in the scientific community. In a recent ACS paper, the investigators used hydroxychloroquine (HCQ) as a reference template to screen for structural similarity against a library of approximately 4000 approved drugs. The top-ranked drugs, based on structural similarity to HCQ, selected for in vitro antiviral assessment, were zuclopenthixol and nebivolol, which blocked SARS-CoV-2 in vitro infection with EC50 values in the low micromolar range. The anti-SARS-CoV-2 potential of ambroxol, amodiaquine, and its active metabolite (N-monodesethyl amodiaquine) were discussed. They concluded both the pKa (acidity) and the HCQ aromatic core play a role in antiviral activity. These are such broad mechanisms that such studies are academic and may have too many in vivo variable interactions to be clinically relevant (Giovanni Bocci et al. ACS Pharmacol. Transl. Sci. 2020, 3, 6, 1278–1292; publication date: October 14, 2020, https://doi.org/10.1021/acsptsci.0c00131). Unfortunately, another anti-parasitic drug, Ivermectin, has been revisited as a general antiviral after 50 years of study that have not translated into such clinical use https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7251046/pdf/210_2020_Article_1902.pdf and https://www.nature.com/articles/s41429-020-0336-z.pdf. Among the many mechanisms of action of Ivermectin, the most relevant to antiviral activity is as an inhibitor of nuclear transport mediated by the importin α/β1 heterodimer, responsible for the translocation of various viral species proteins. Unfortunately, most of the viruses it is supposed to effect are not inhibited in replication or infection, or at least consistently. For HIV type 1, a study showed that Ivermectin failed to control the nuclear accumulation of telomer repeat factor-1 (GFP-TRF) which can only be transferred by IMPβ1 to the cell nucleus disputing the proposed mechanism. Researchers concluded that Ivermectin is not a specific inhibitor for IN-IMP α/β interaction, but it appears to be a specific inhibitor of cargos that are dependent on the heterodimer, making its predicted antiviral activity in a host even more suspicious. Law of diminishing returns seems to come into play with Ivermectin treatment. Virus out runs capacity. In pigs with circovirus 2, in the first 24 hrs, Ivermectin reduced viral load by 41% and 28.2%, However, in 48 hrs, it reduced viral load 28.8% and 15.7%, at the same treatment concentrations. Evidently, it decreases in drug efficacy at later time points of infection. In a recent study among adults with mild COVID-19, a 5-day course of ivermectin, compared with placebo, did not significantly improve the time to resolution of symptoms. The findings did not support the use of ivermectin for treatment of mild COVID-19 https://jamanetwork.com/journals/jama/articlepdf/2777389/jama_lpezmedina_2021_oi_210022_1614808764.76432.pdf. In spite of all its years of use in Veterinary Medicine, to prevent heartworms in dogs and other worms in livestock, I have never heard of a veterinarian using it to treat viral infections. Also, I don’t see Ivermectin listed in the Overview of Antiviral Agents, Pharmacology, in the Merck Veterinary Manual. For Ivermectin to be effective against SARS-CoV-2, in cell culture, the concentrations had to be in the microgram per ml range, blood levels of Ivermectin are at safe therapeutic doses in the 20–80 ng/ml range.

The National Institutes of Health (NIH), under pressure from clinicians, has dropped its recommendation against the inexpensive antiparasitic drug Ivermectin for treatment of COVID-19, and the agency now states it can’t recommend for or against its use, leaving the decision to physicians and their patients. “Results from adequately powered, well-designed, and well-conducted clinical trials are needed to provide more specific, evidence-based guidance on the role of ivermectin for the treatment of COVID-19,” according to new NIH guidance released recently. Some clinical studies showed no benefits or worsening of disease after its use; however, others reported shorter time to resolution of disease. This may be tied to viral load or just an unreliable, unpredictable response.

Some have already failed clinical trials (such as hydroxychloroquine) and some seem counterintuitive (like the immunosuppressant cyclosporine) so caution must be taken in extrapolating these results and they only be considered for suggesting possible clinical testing candidates. They found nine drugs with antiviral activity in lung epithelial cells: 7 of the drugs have been used in humans, 3 FDA approved in the United States (cyclosporine, dacomitinib, and salinomycin), and ebastine (an anti-histamine) approved outside the United States (https://www.cell.com/action/showPdf?pii=S2211-1247%2821%2900273-4). Some of the immunosuppressive and ant-histamine anti-SARS-CoV-2 activities may be explained by the linkage of the host response to the virus to the peculiar anti-parasite, anti-tumor immunity and its adverse effects in COVID.

Other non-immune-mediated drugs are being considered. The government is paying Merck & Co about 356 million USD to fast-track production of one of its potential treatments under Operation Warp Speed. The funding will allow the company to deliver up to 100,000 doses by 30 June 2021, if successful and FDA clears the treatment for emergency use. It is called MK-7110, designed to minimize damaging effects of an overactive immune response to COVID-19. Another promising drug is plitidepsin (aplidin), 27.5 times more potent than remdesivir in cell culture. The mechanism of action against SARS-CoV-2 is through inhibiting eEF1A, a key cellular protein in proliferation and growth (the eukaryotic elongation factor 1 α, eEF1A). During protein translation, eEF1A recruits aminoacyl t-RNA to the ribosome and translocates the growing polypeptide from the ribosomal A site to the P site. Therefore, the drug inhibits viral protein production and, subsequently, viral replication. It’s potential toxicity, because of this non-specificity, is on protein synthesis, growth and healing. The viral production was inhibited at 8-12 hours but was not significant after 24 hours of infection. Therefore, it must be used early in infection based on these in vitro and animal studies https://science.sciencemag.org/content/sci/early/2021/01/22/science.abf4058.full.pdf. Recently modeling efforts and in vitro cell culture studies have examined repurposing other FDA approved drugs as antivirals to treat COVID. These include the old anti-tapeworm drug niclosamide. It has shown broad efficacy against viruses including SARS-CoV-2. This salicylanilide’s antiviral activity is based on its ability to prevent acidification of endocytotic compartments, blocking membrane fusion and infection of the host cell. Early viral studies showed that the efficacy of salicylanilides was derived from the anilide ring, the important role of the N− H group in shuttling protons into the endosome. Niclosamide’s reduction of infection in cells without interacting directly with any viral components presents the possibility of anti-COVID-19 therapeutics with broad activity against current and future variants of the virus, but also may dilute out its effectiveness as seen with antihelmintics like ivermectin and increase the possibility of side effects (Steven Blake et al., Salicylanilides Reduce SARS-CoV‐2 Replication and Suppress Induction of Inflammatory Cytokines in a Rodent Model, https://doi.org/10.1021/acsinfecdis.1c00253
A, ACS Infect. Dis.).

How do we reconcile broad-spectrum, non-specific treatments to counter natural selection of viruses resistant to specific antibody or cellular immunity against requirements to avoid off-target and diluted-out effects of non-specific treatments ? First, the current vaccines may induce broader coverage immunity than illustrated by monoclonal antibody or convalescent plasma responses to infection. Even the difference between male and female immune responses, females having more effective T cell cellular immune responses than males’ B cell dominated antibody response, indicates broader immune coverage from the same SARS-CoV-2 antigens https://science.sciencemag.org/content/sci/371/6527/347.full.pdf. The Th17 response to COVID-19 also indicates a more generalized polyclonal immune response. So don’t write off the current vaccines yet. Second, I have alluded to, in earlier posts, that aptamers which can be selected synthetically to many targets on the virus and be changed rapidly, can also link these anti-ligands to specific pre-existing antibody or immune cells to rapidly mobilize the immune system against the virus and even convert the pathogenic virus into an autogenous endogenous vaccine after directly neutralizing it. The original route of administration was by inhalation to enable self-application of the treatment/prevention. However, these approaches are yet to get out of the basic research laboratory.
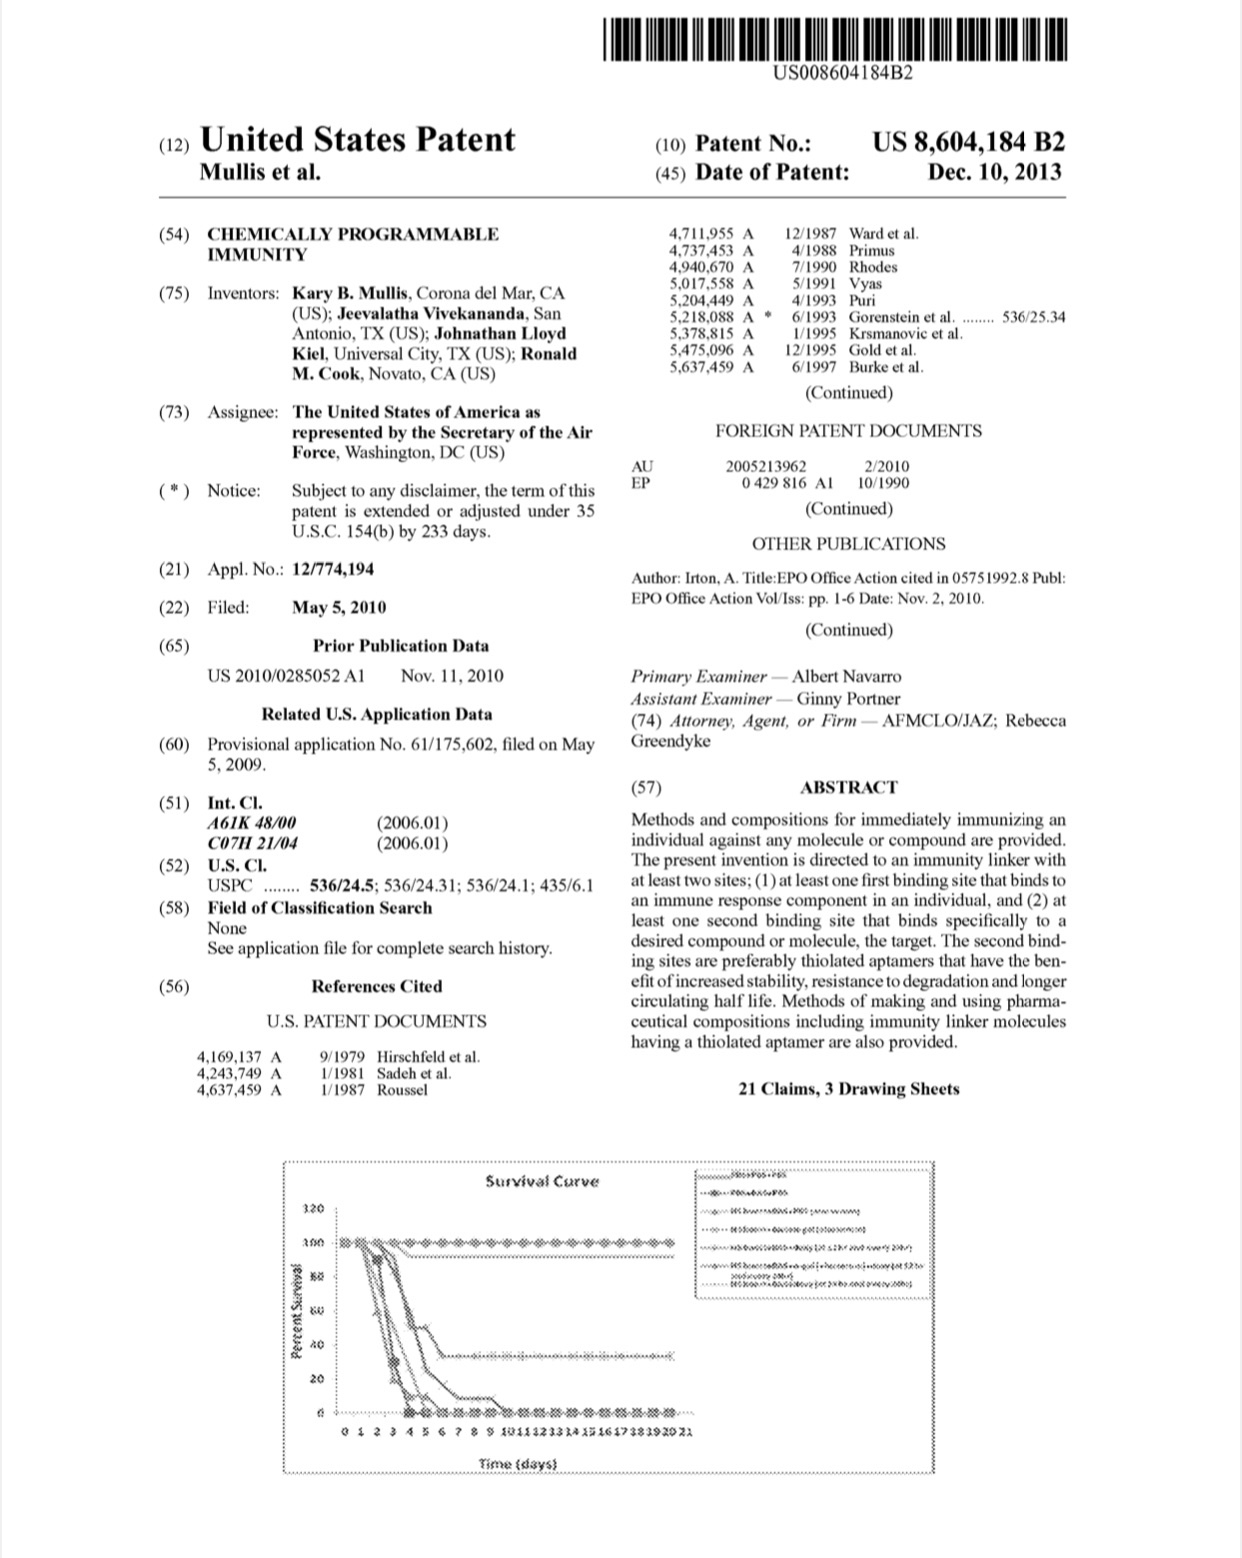
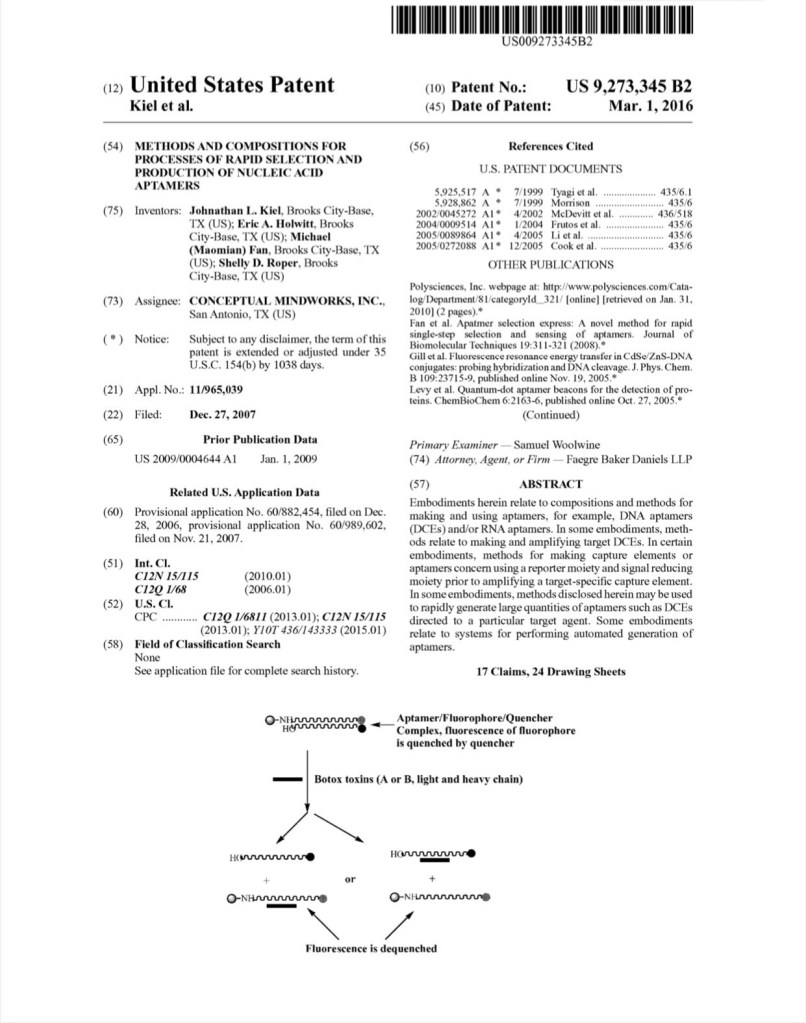
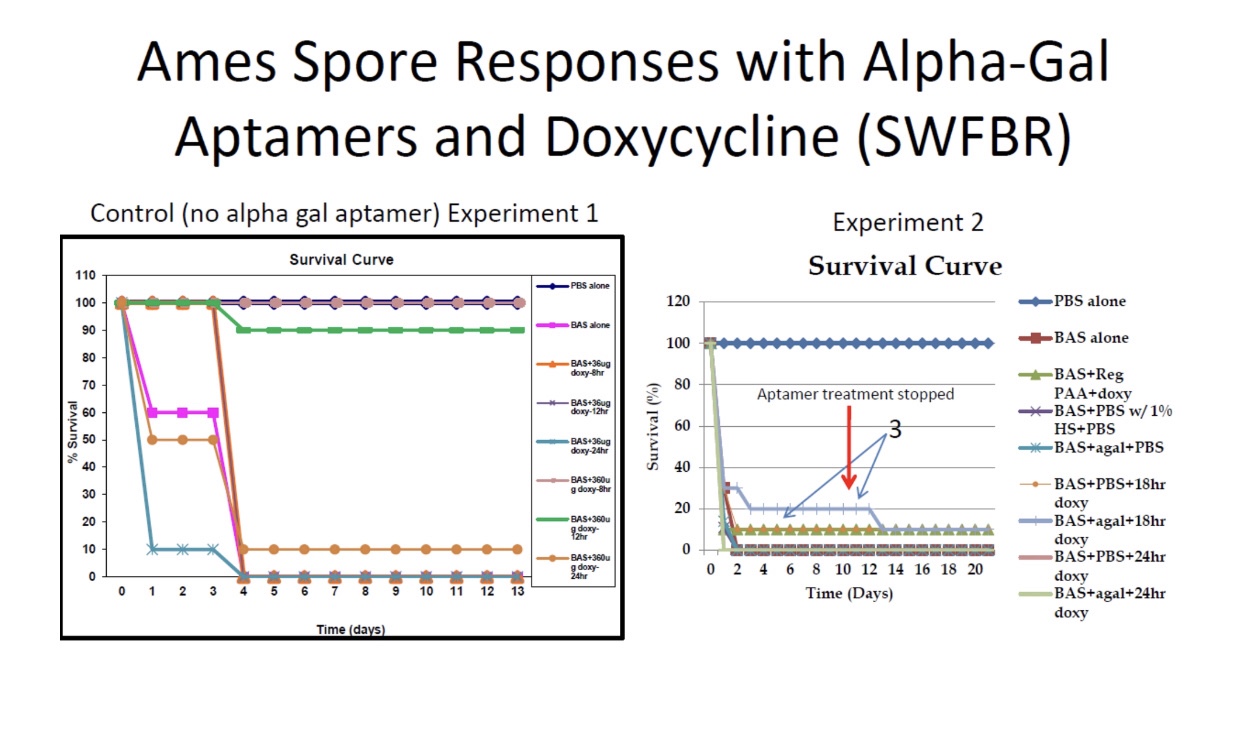
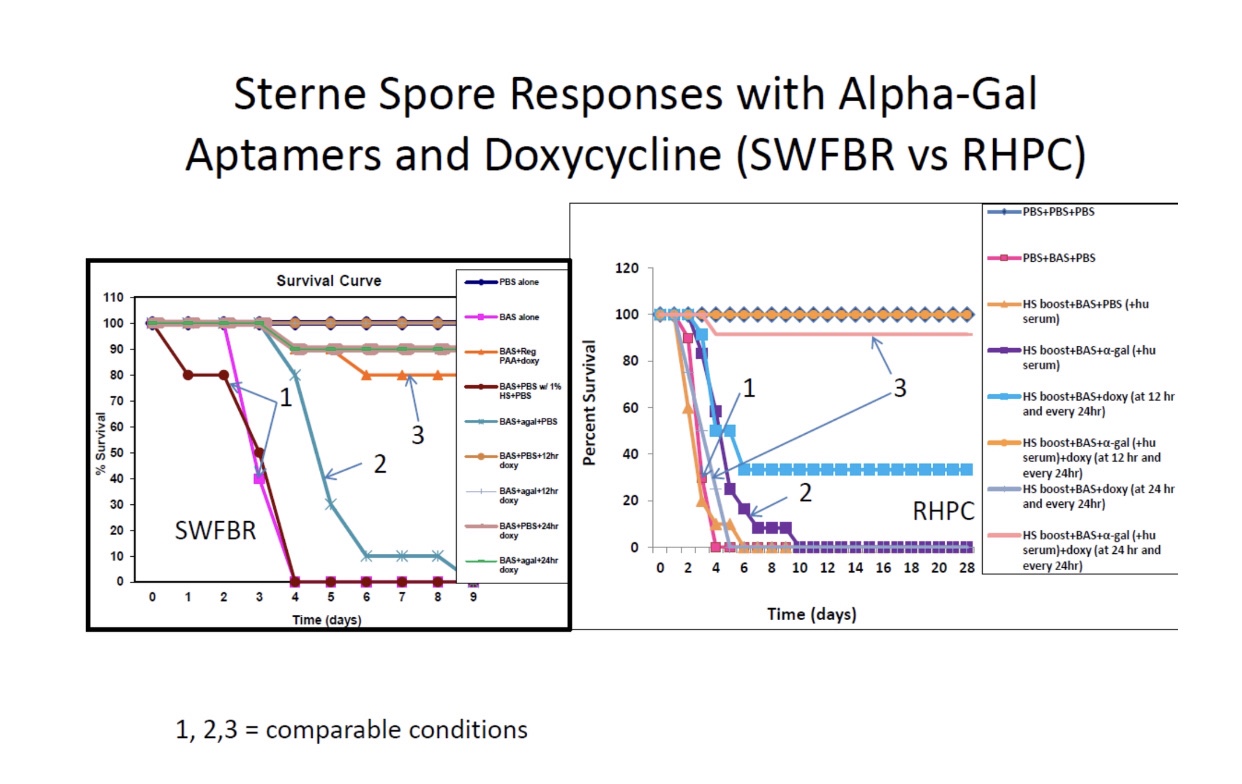
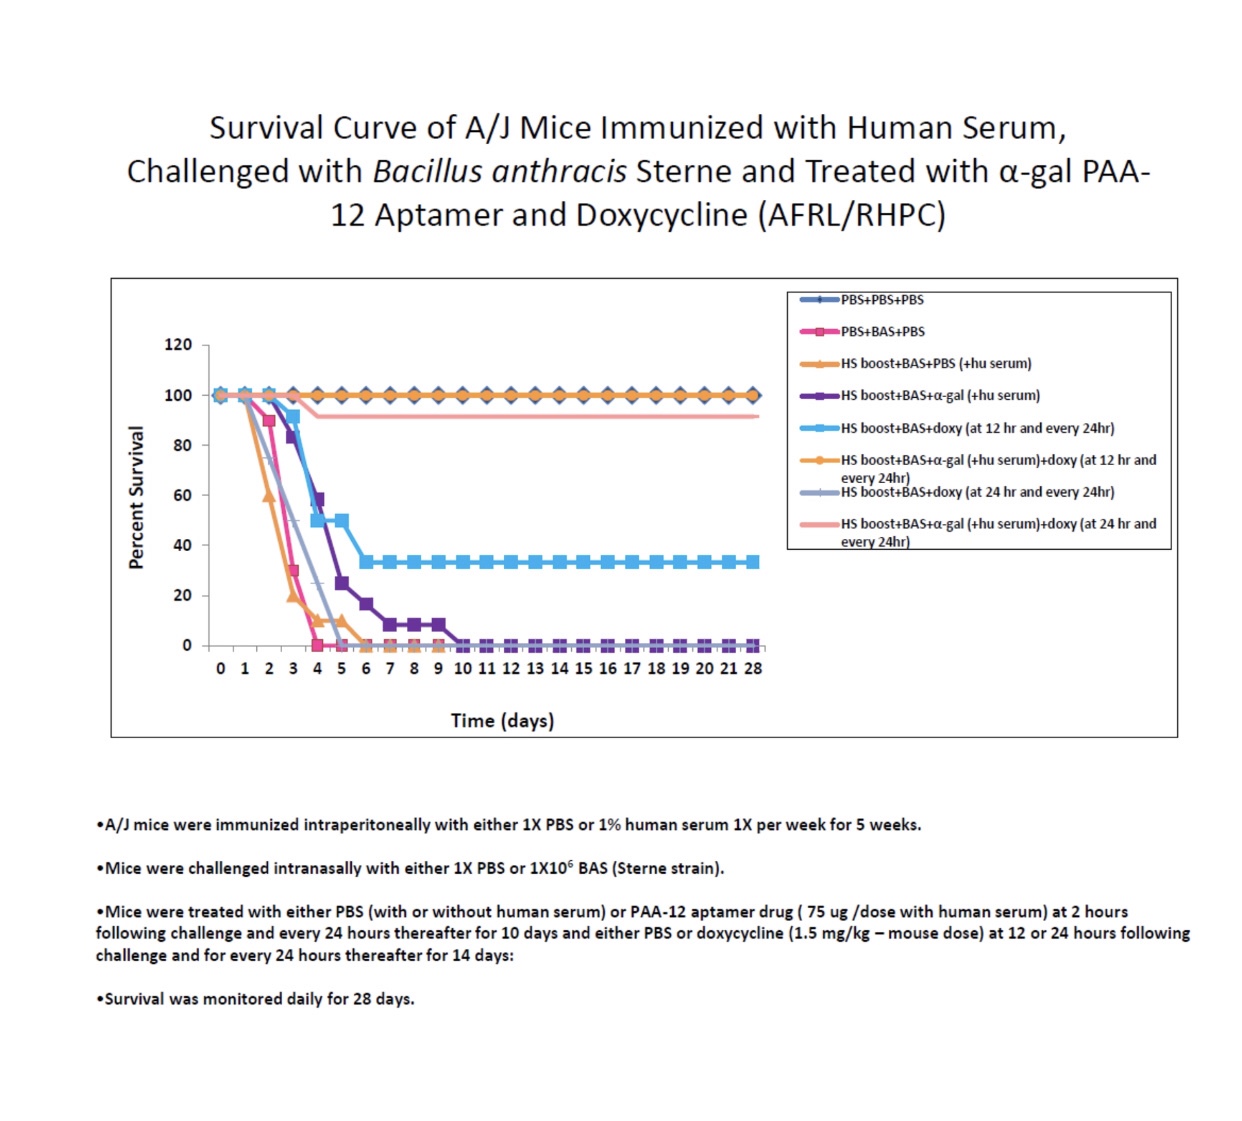
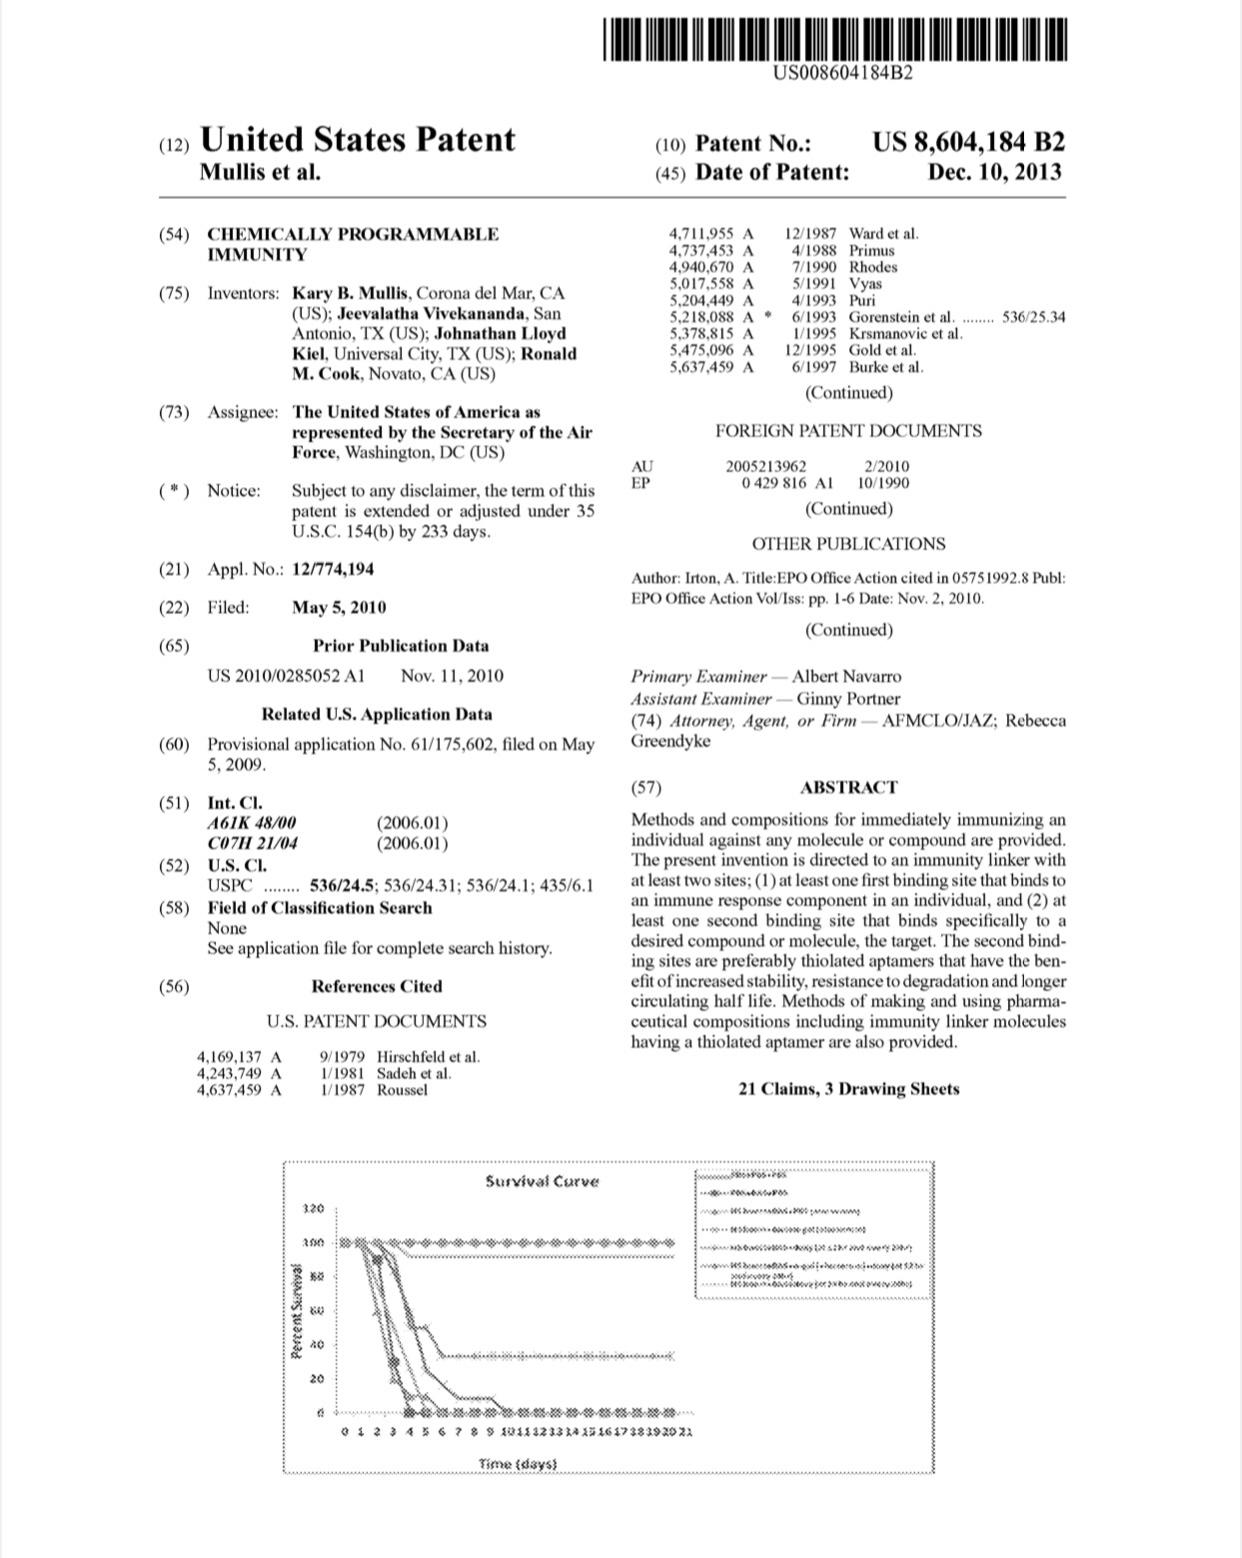
Demonstration of the concept of re-directing the immune system is illustrated by data in this patent showing that previous inoculation with human serum (stand-in for a vaccination) helps decrease lethality of inhaled anthrax spores through an alpha-gal carbohydrate component of aptamers, against which antibody in the human serum is naturally immune, and a linked component of the same aptamers selected in vitro to bind to the protective antigen (PA) of the anthrax toxin. The mouse antibody against the human antibody against the alpha-gal on the aptamers is directed to mediate immune inactivation of the whole toxin, reducing the lethality of anthrax from the spores. Even more remarkable is that the aptamer was delivered by inhalation as well.
Method of making aptamers against any infectious disease agent rapidly on demand
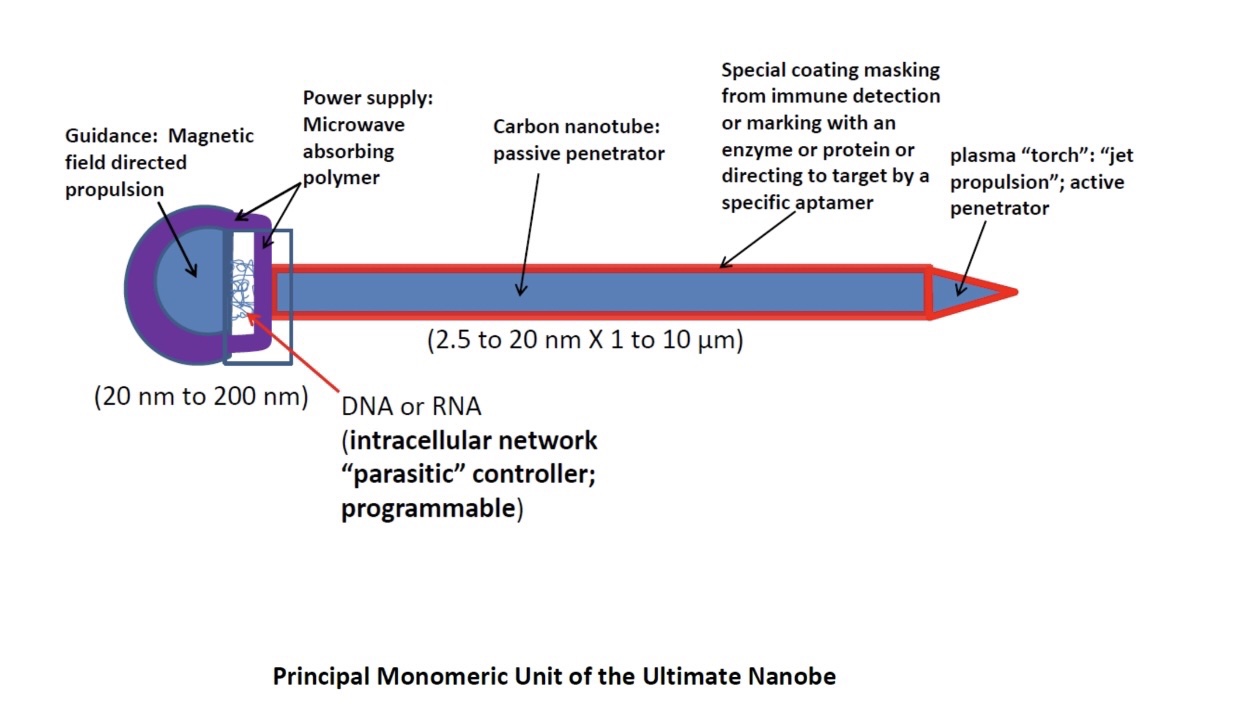
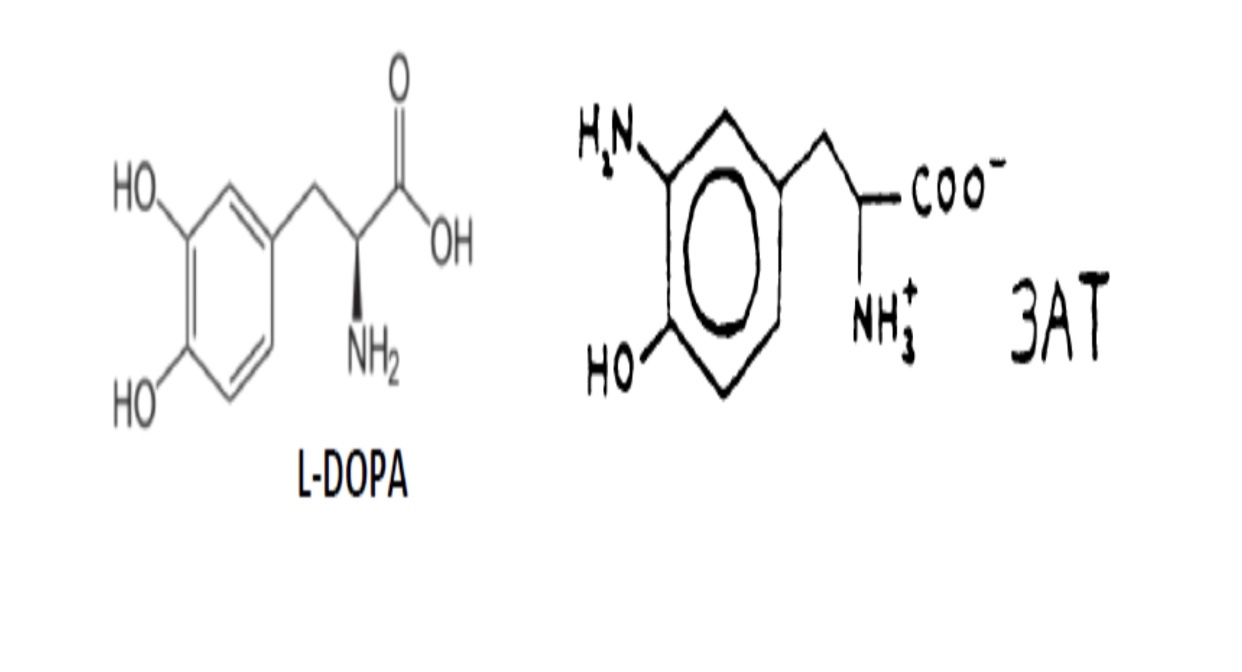
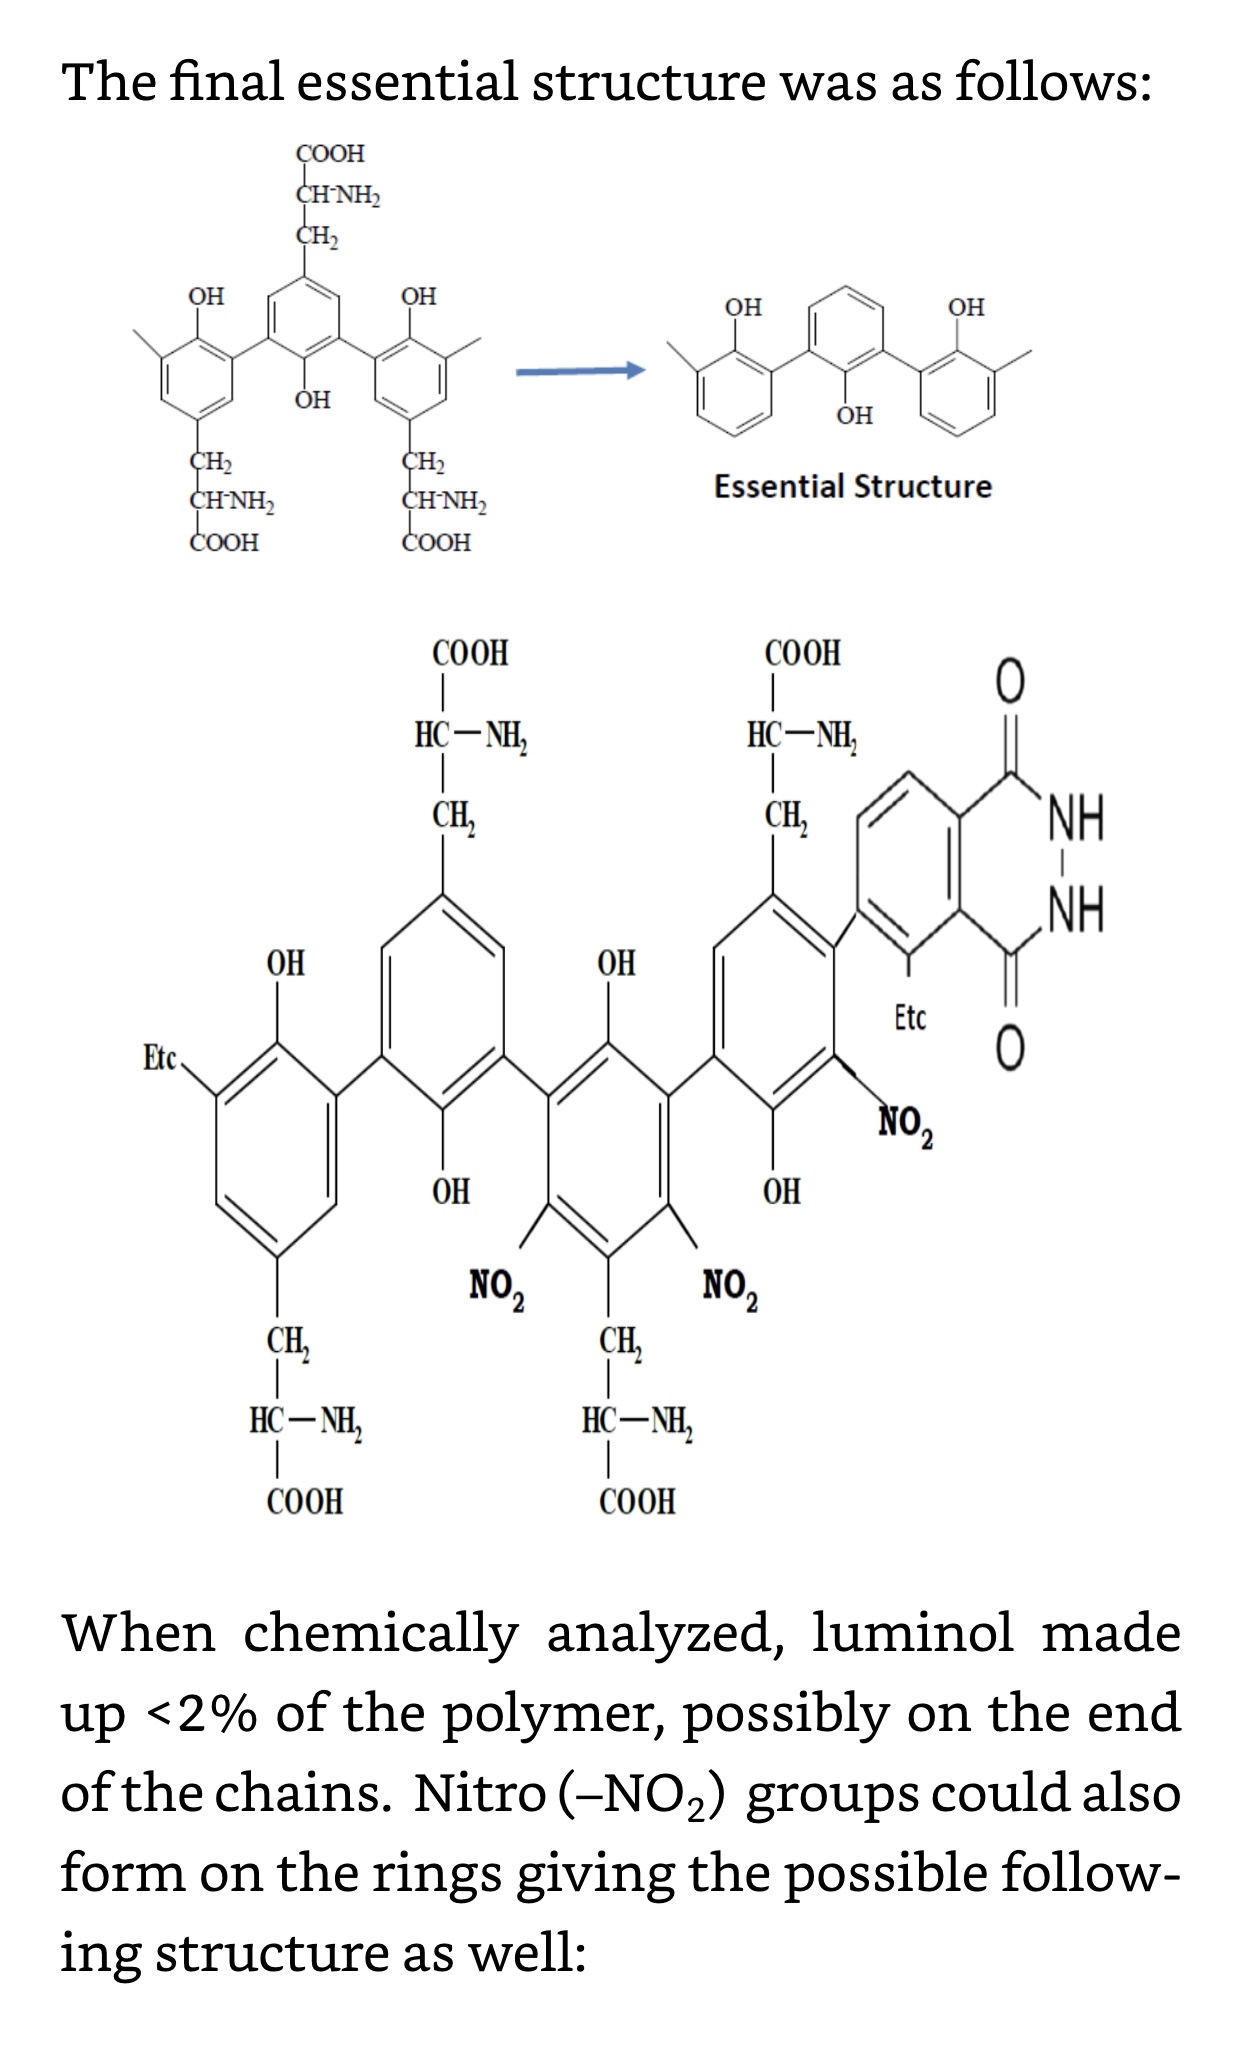
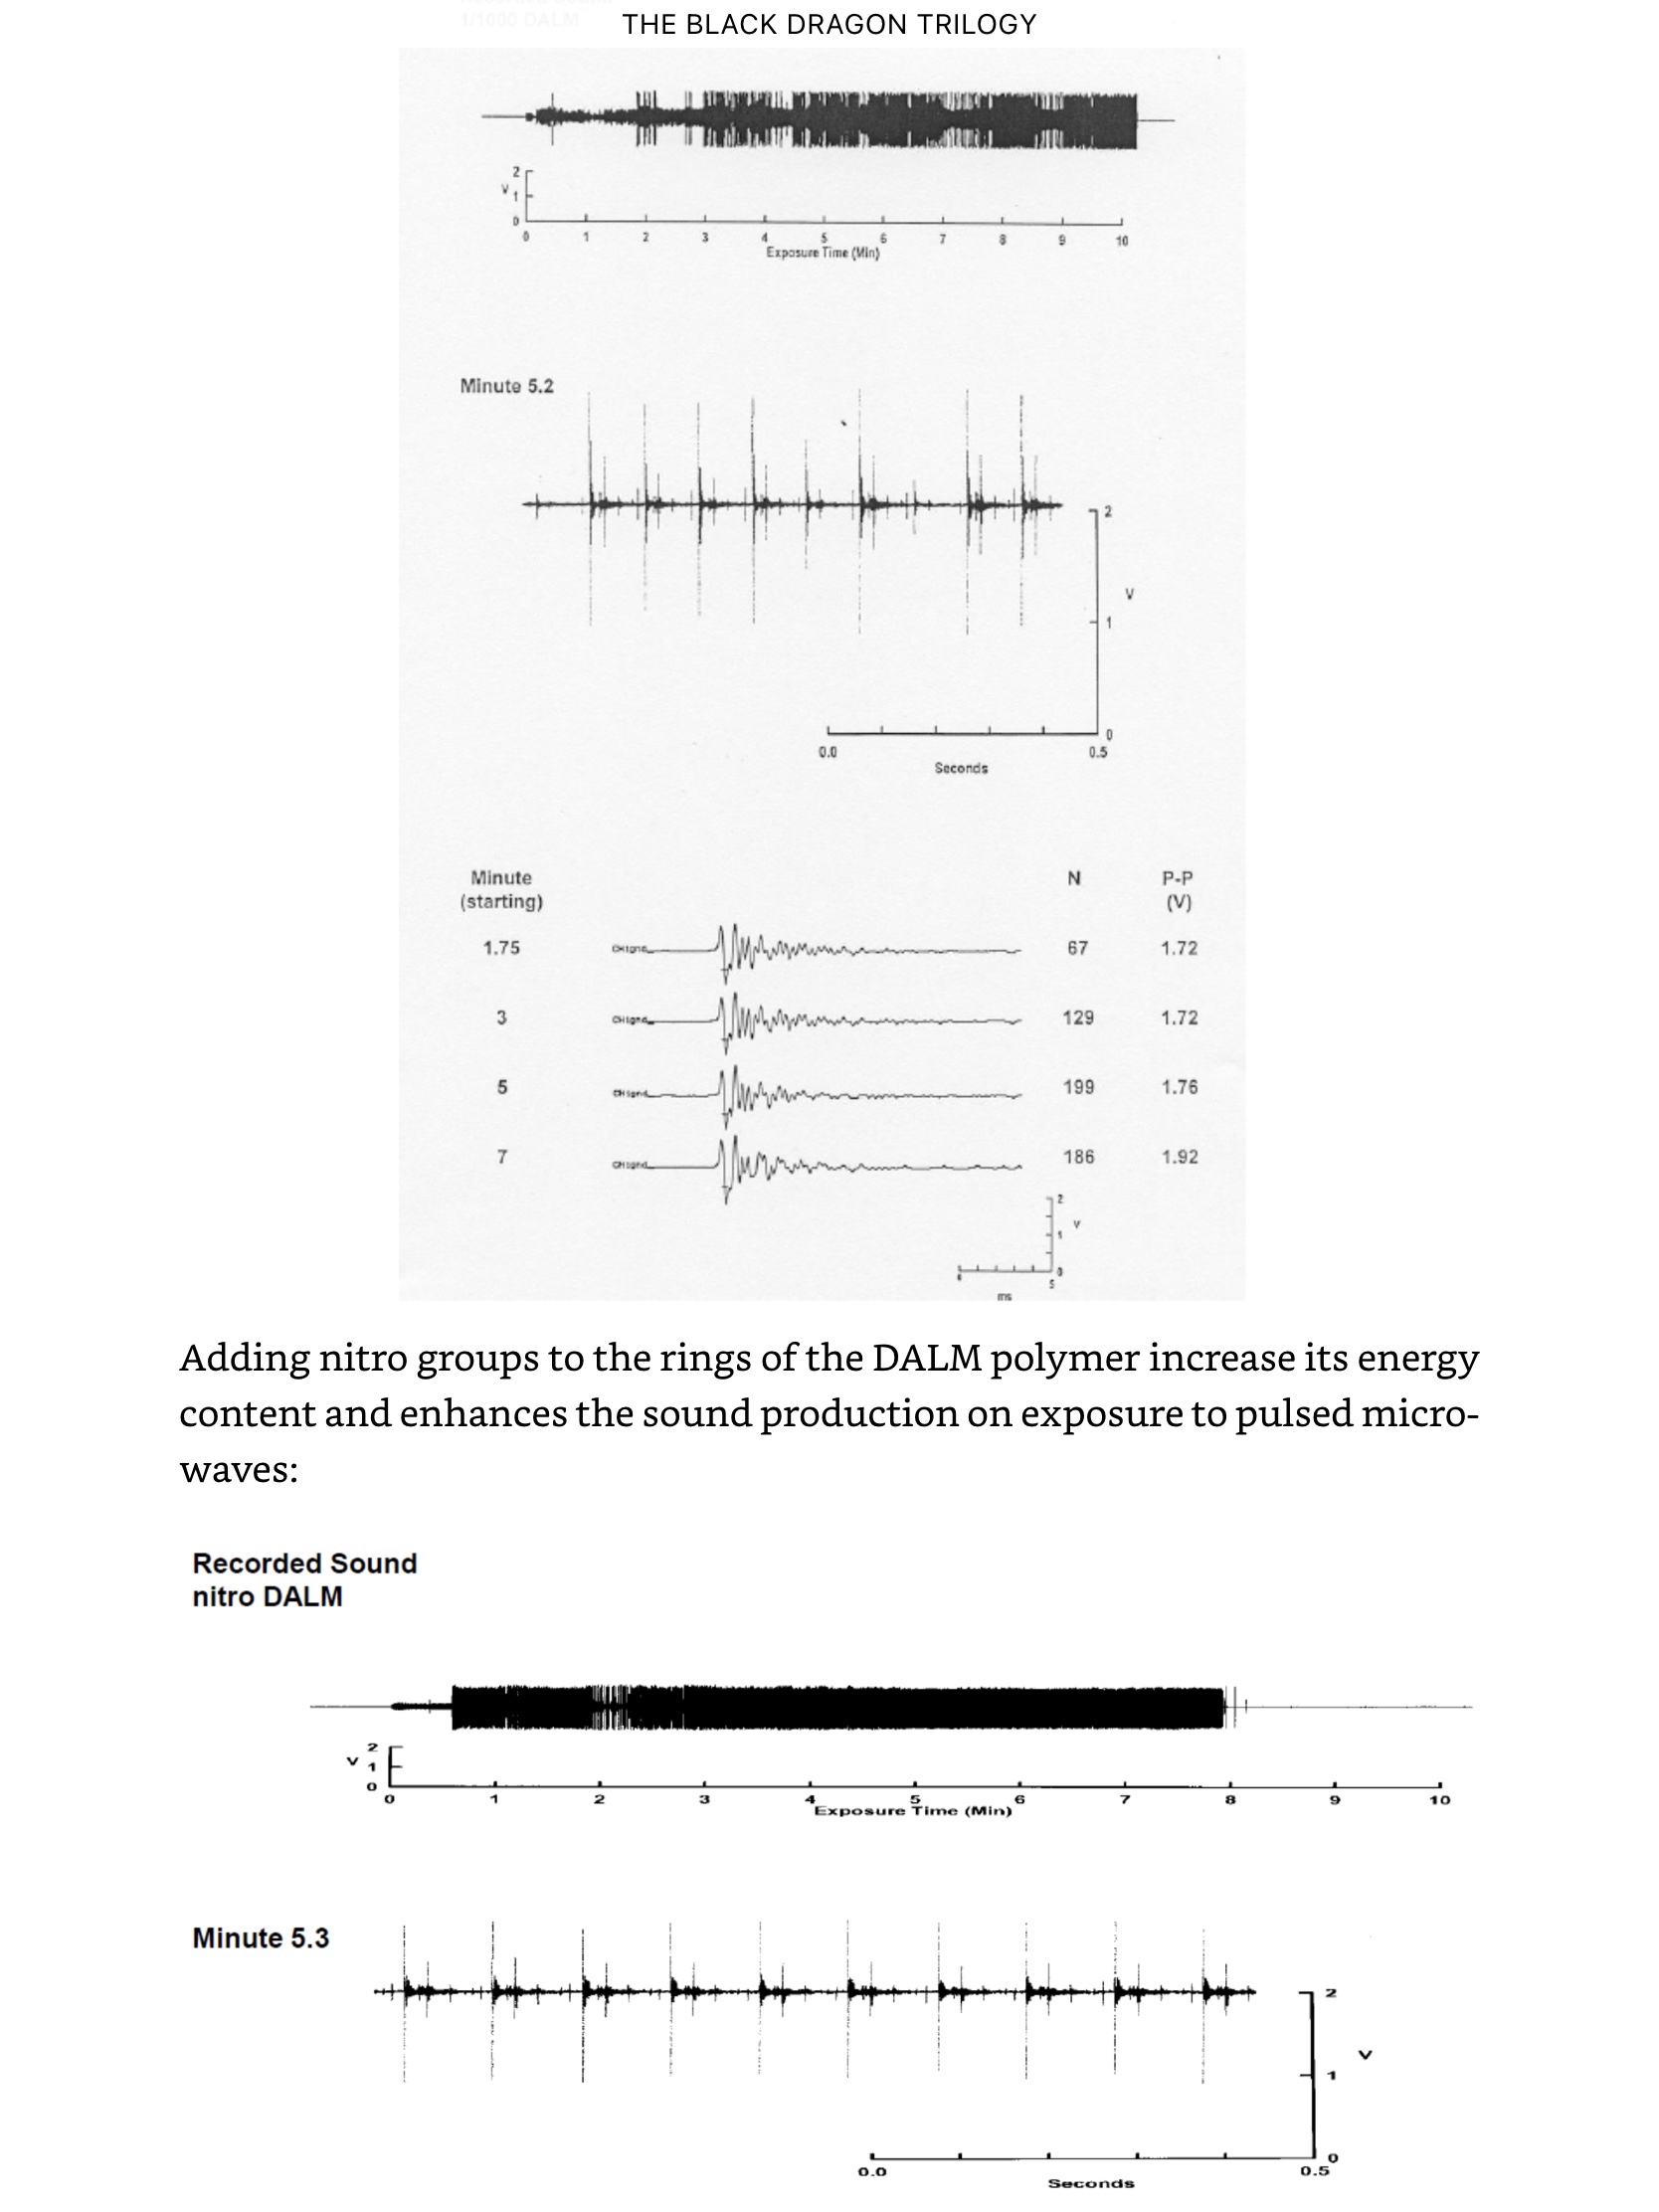
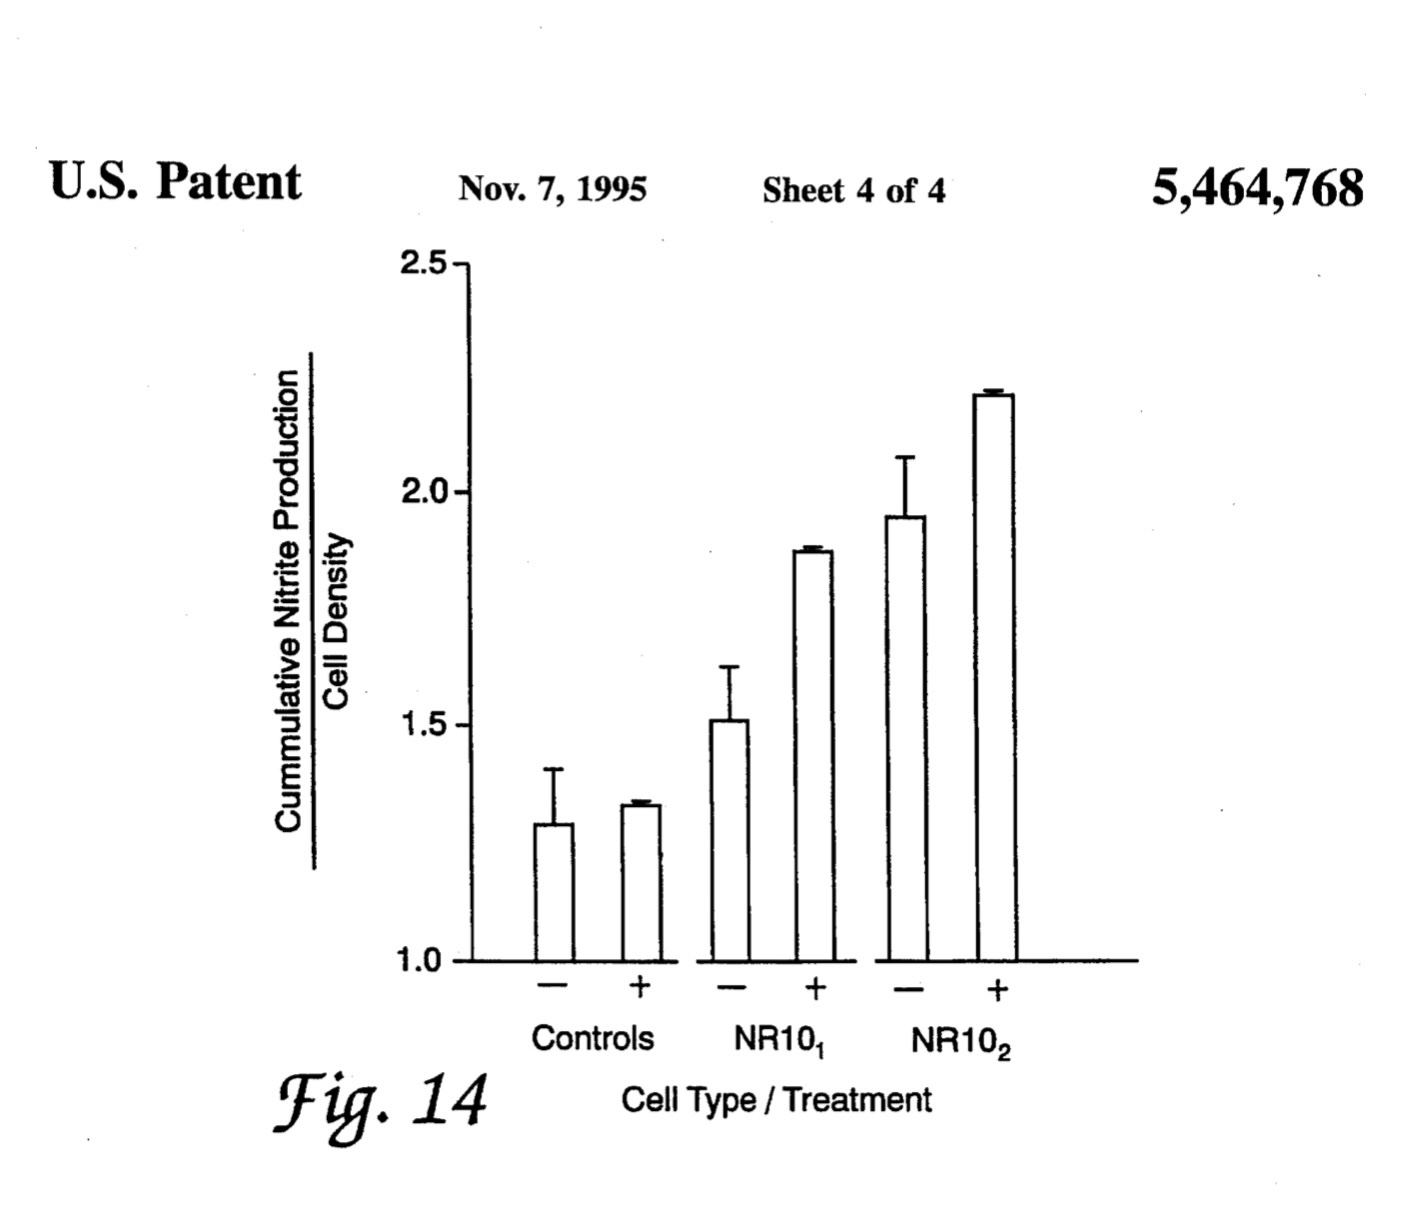
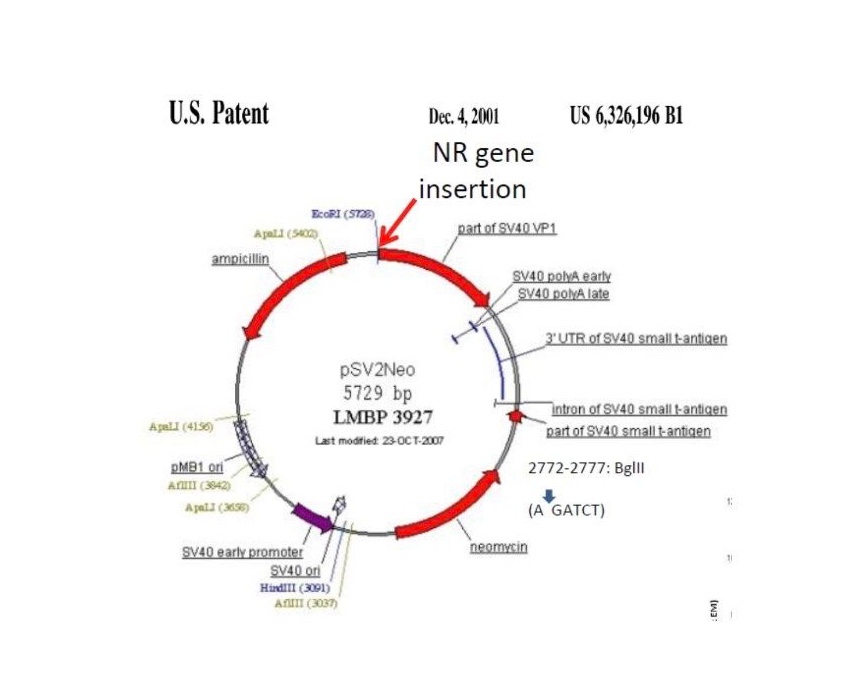
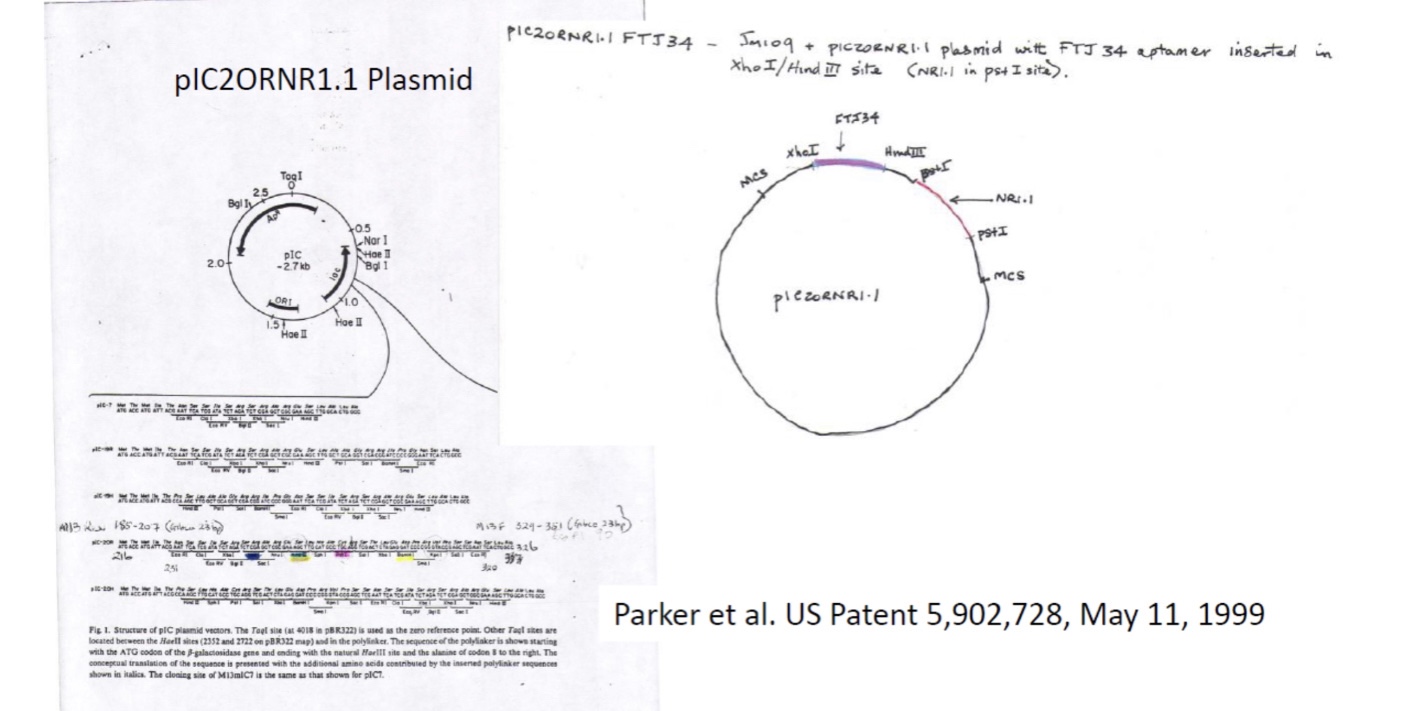
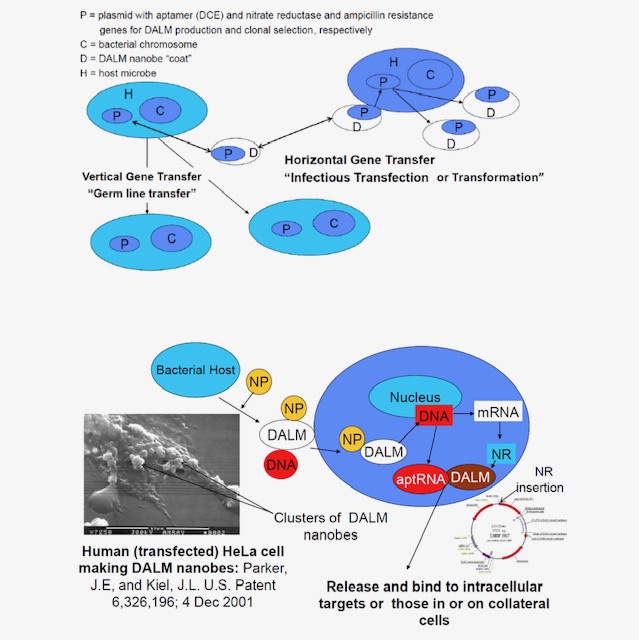
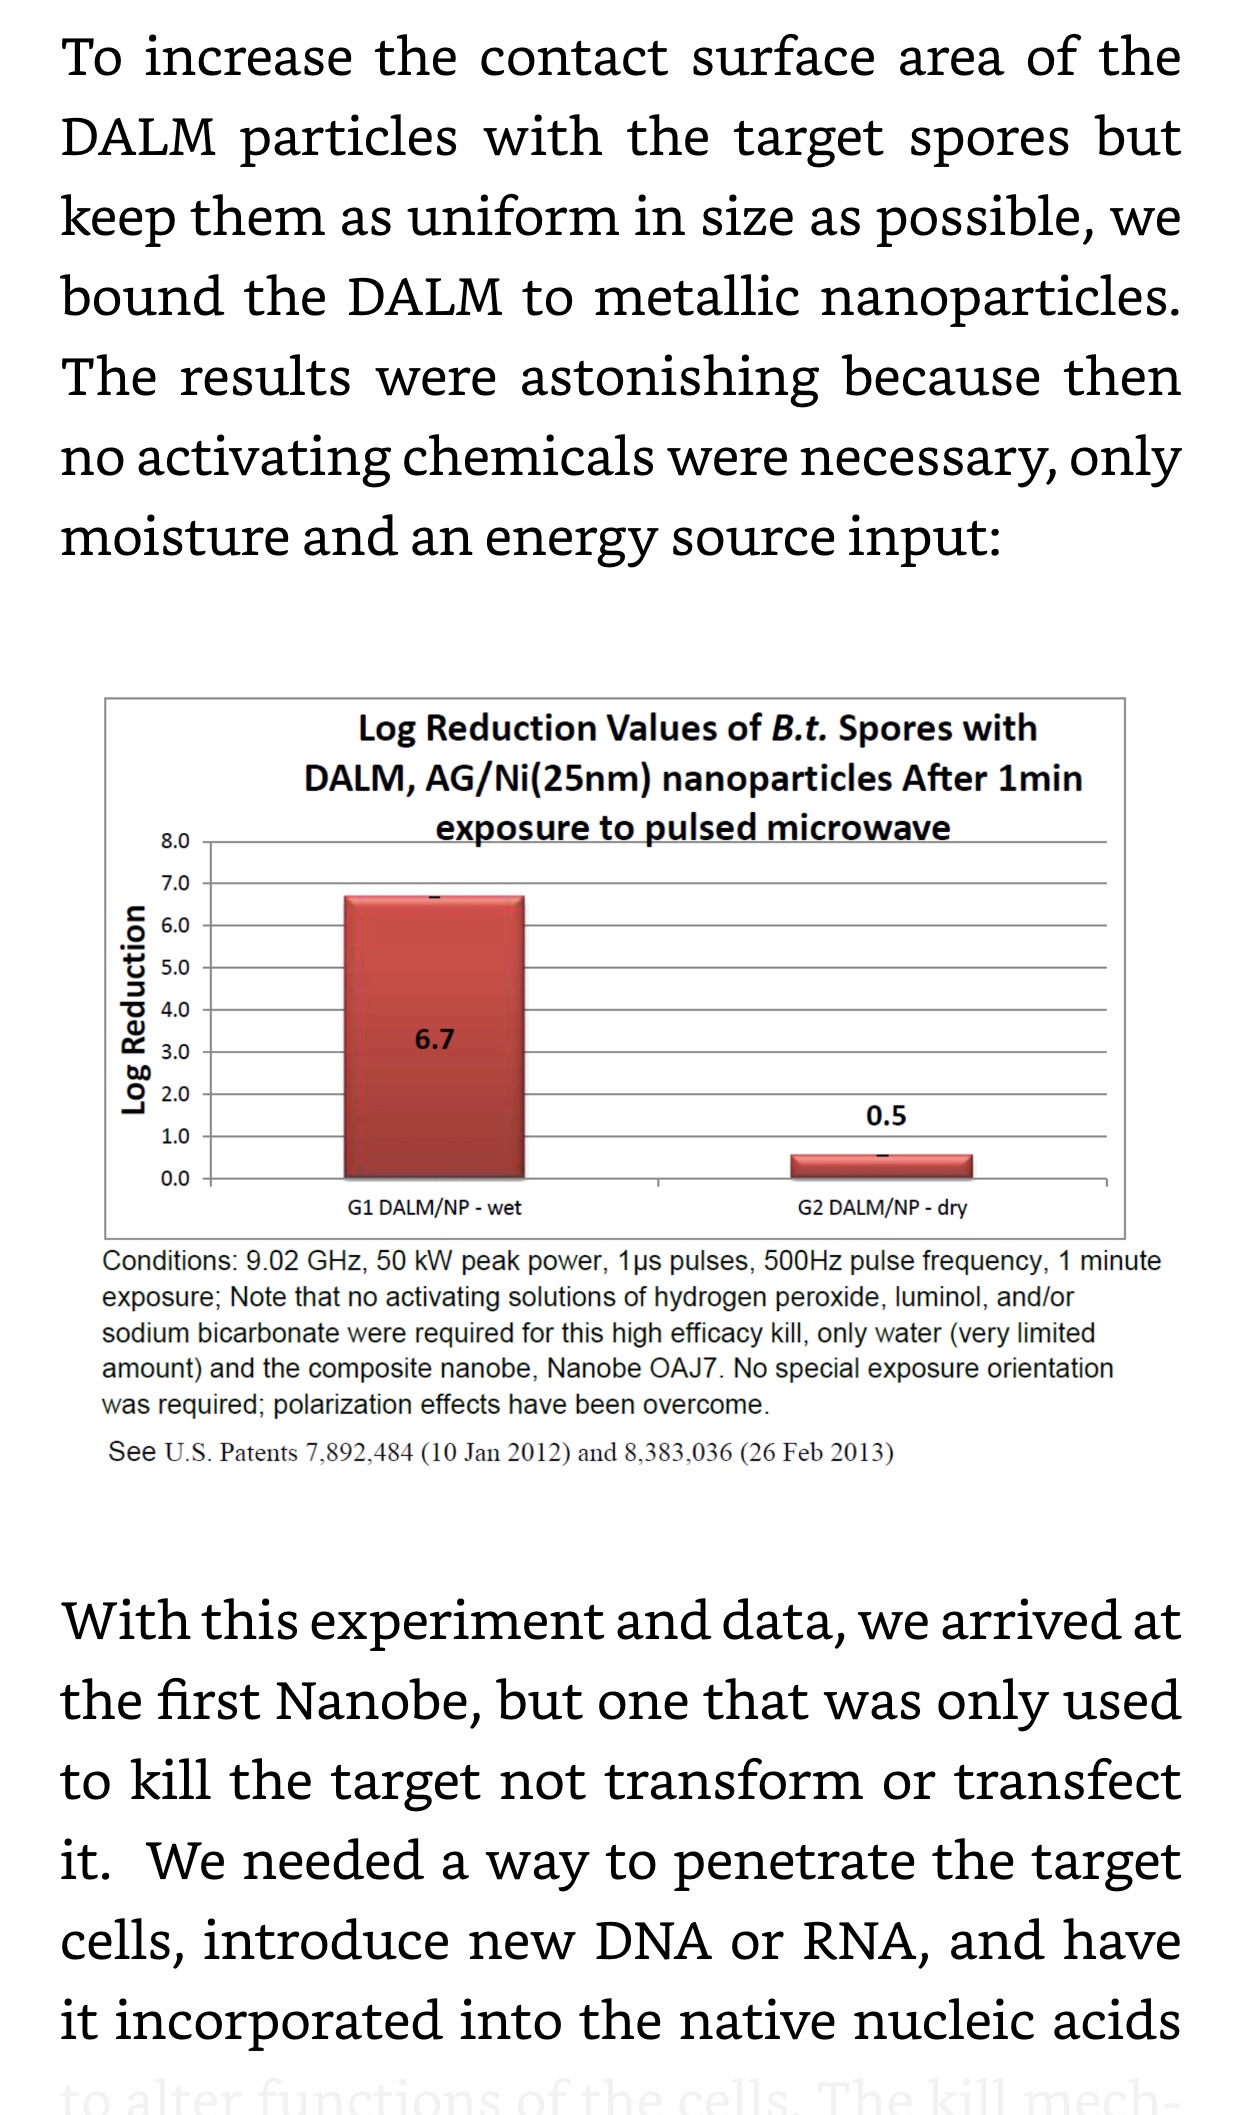
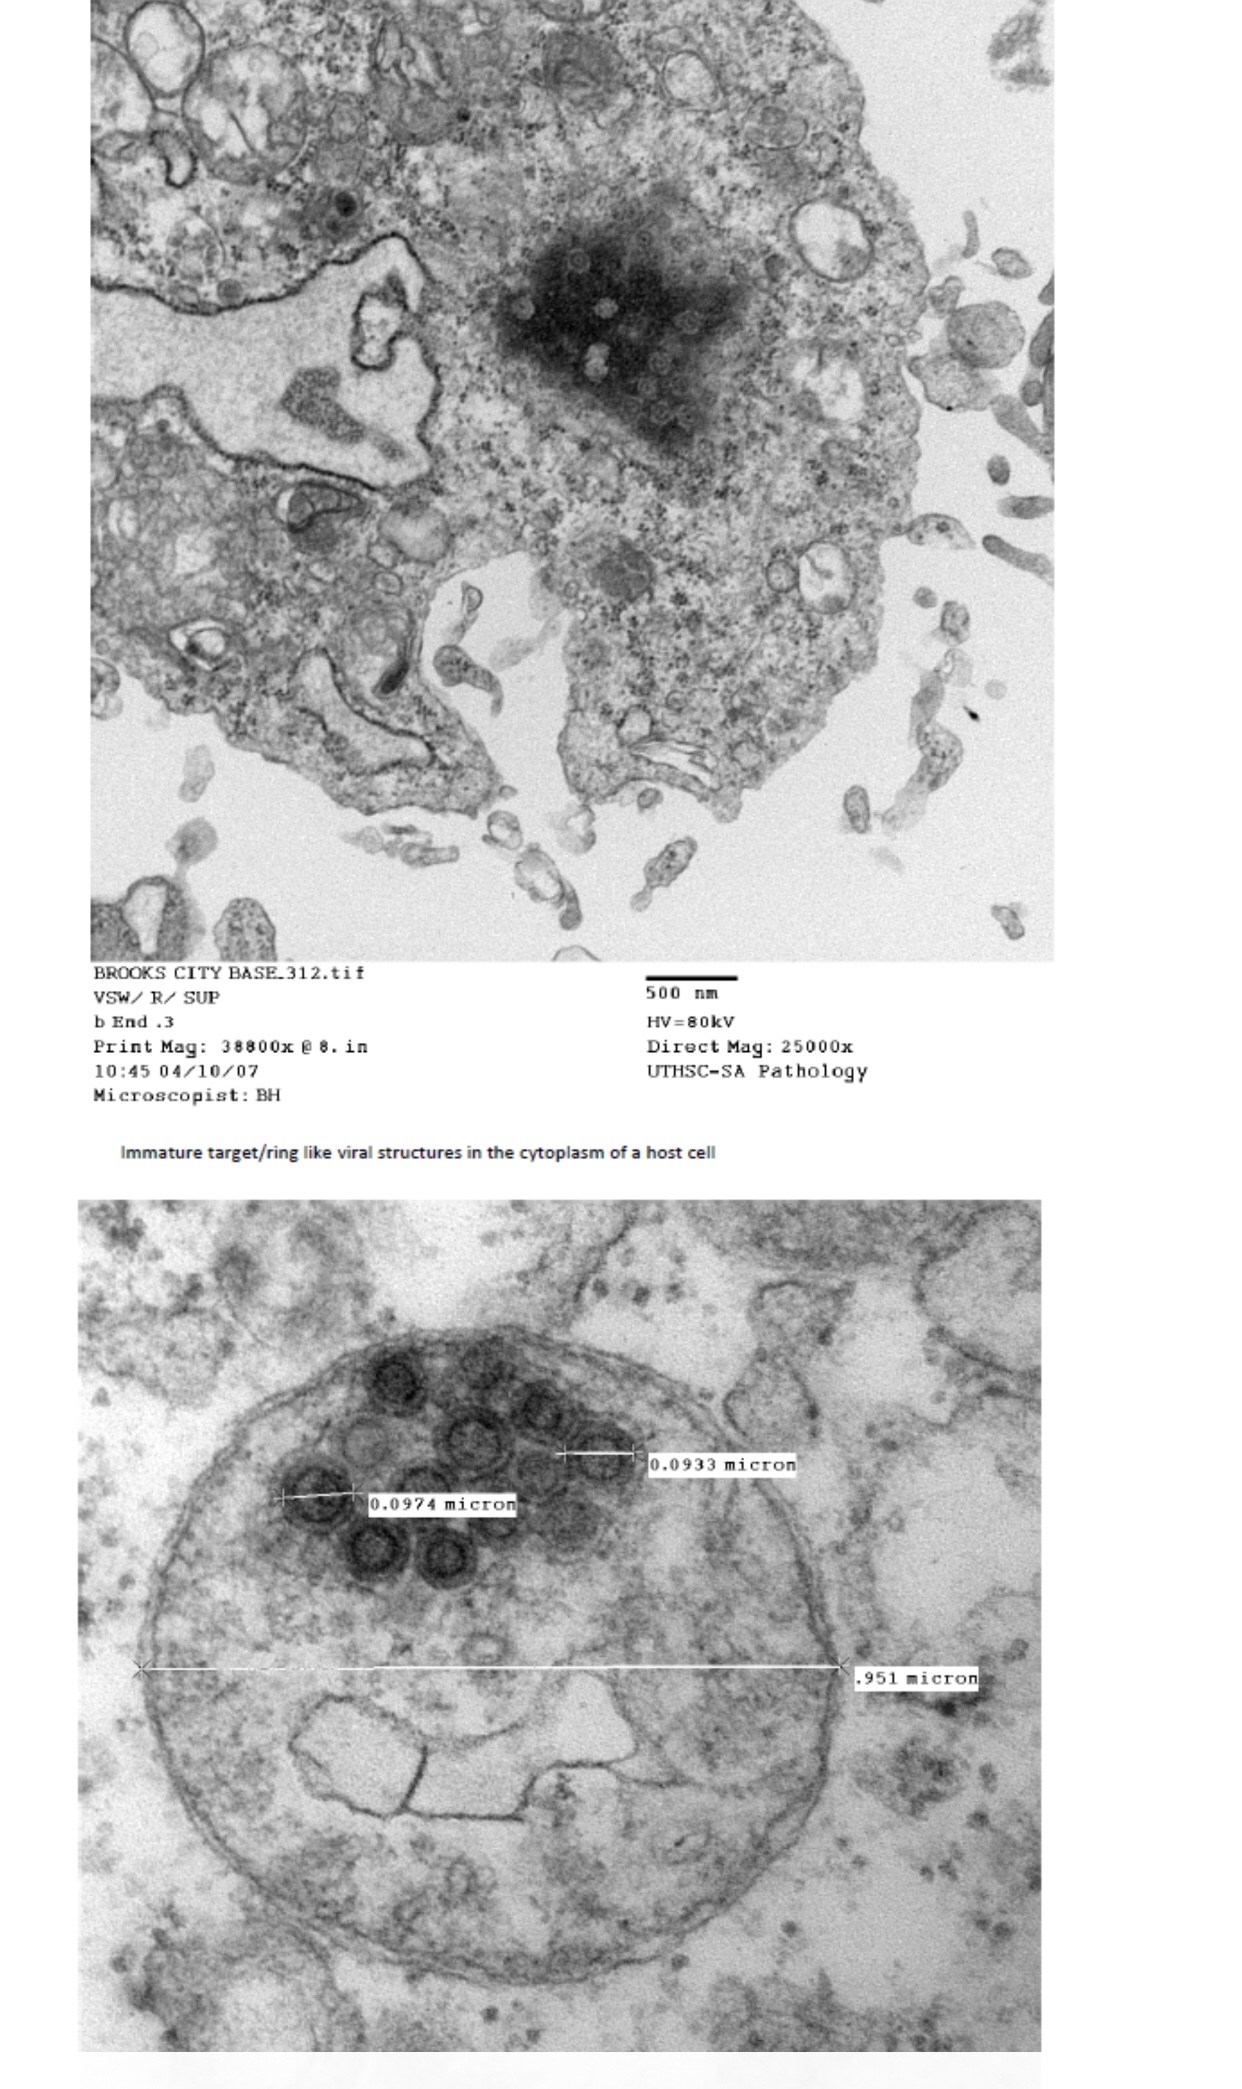
Better untapped way: Synthetic Nanobes can carry the nitrate reductase gene, an alpha virus (VEEV) RNA dependent RNA polymerase gene, and pathogen-specific aptamer sequences as well as aptamer immune cell and existing antibody linker aptamer sequences which re-direct existing immunity immediately toward new antigens such as those developed in a new variant pathogen mutant—tit for tat anti-virus selected mutations. These Nanobes can become adapters for old vaccine to new variants of pathogenic viruses and the Nanobes become self-replicating RNA forms that can move from cell to cell in the host, but still have a fail-safe self-destruct mechanism (non-ionizing electromagnetism radiation absorption to destruction) and regulating nutrients required for replication — nitrate and 3-amino-L-tyrosine. This should be seen as a tool for new treatments and rejuvenation of the effectiveness of old vaccines to address new variants, not a panacea but an enduring platform.
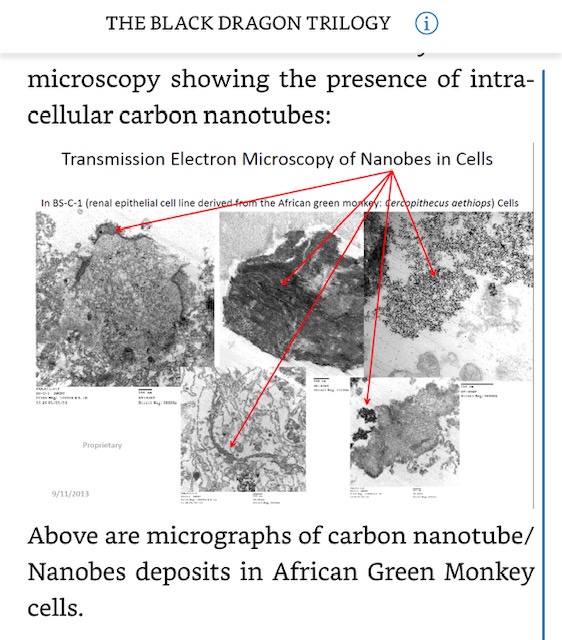
Showing carbon nanotubes can carry genes into cells
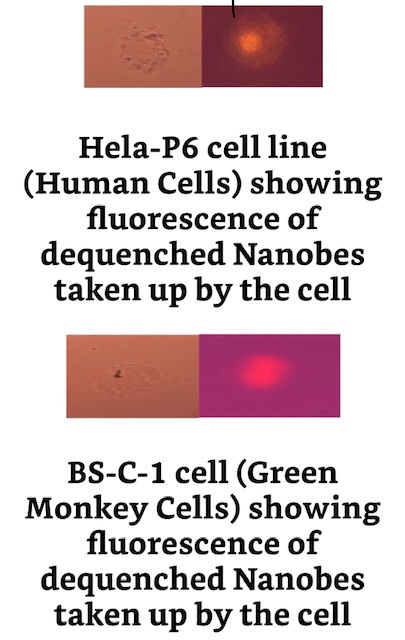
Another method of tracing the movement of gene-bearing Nanobes into living cells: fluorescence

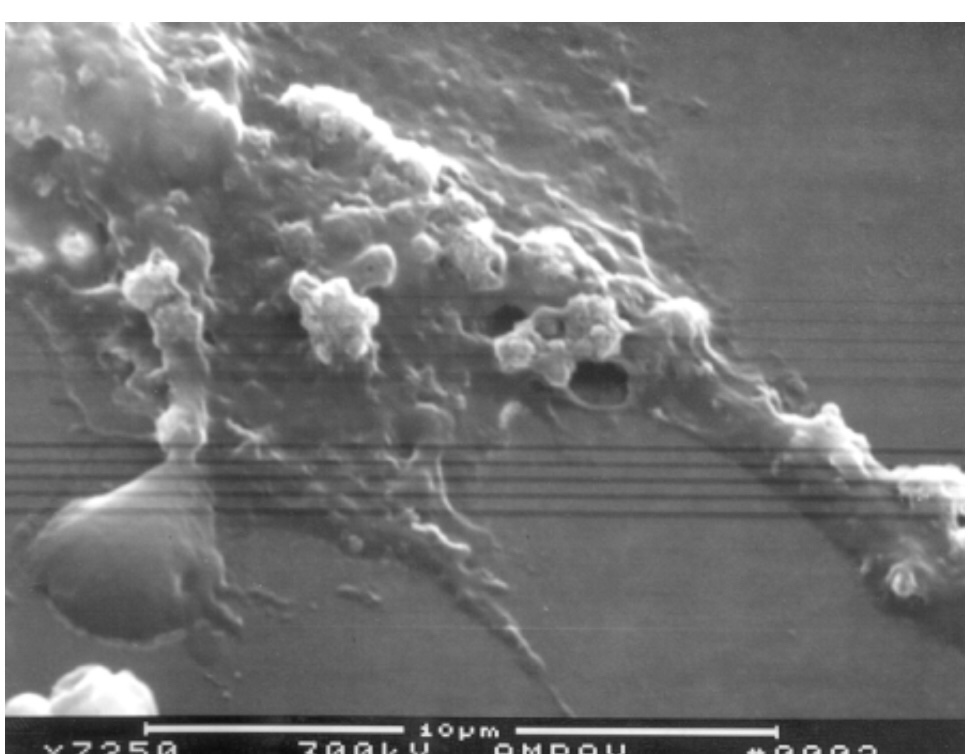
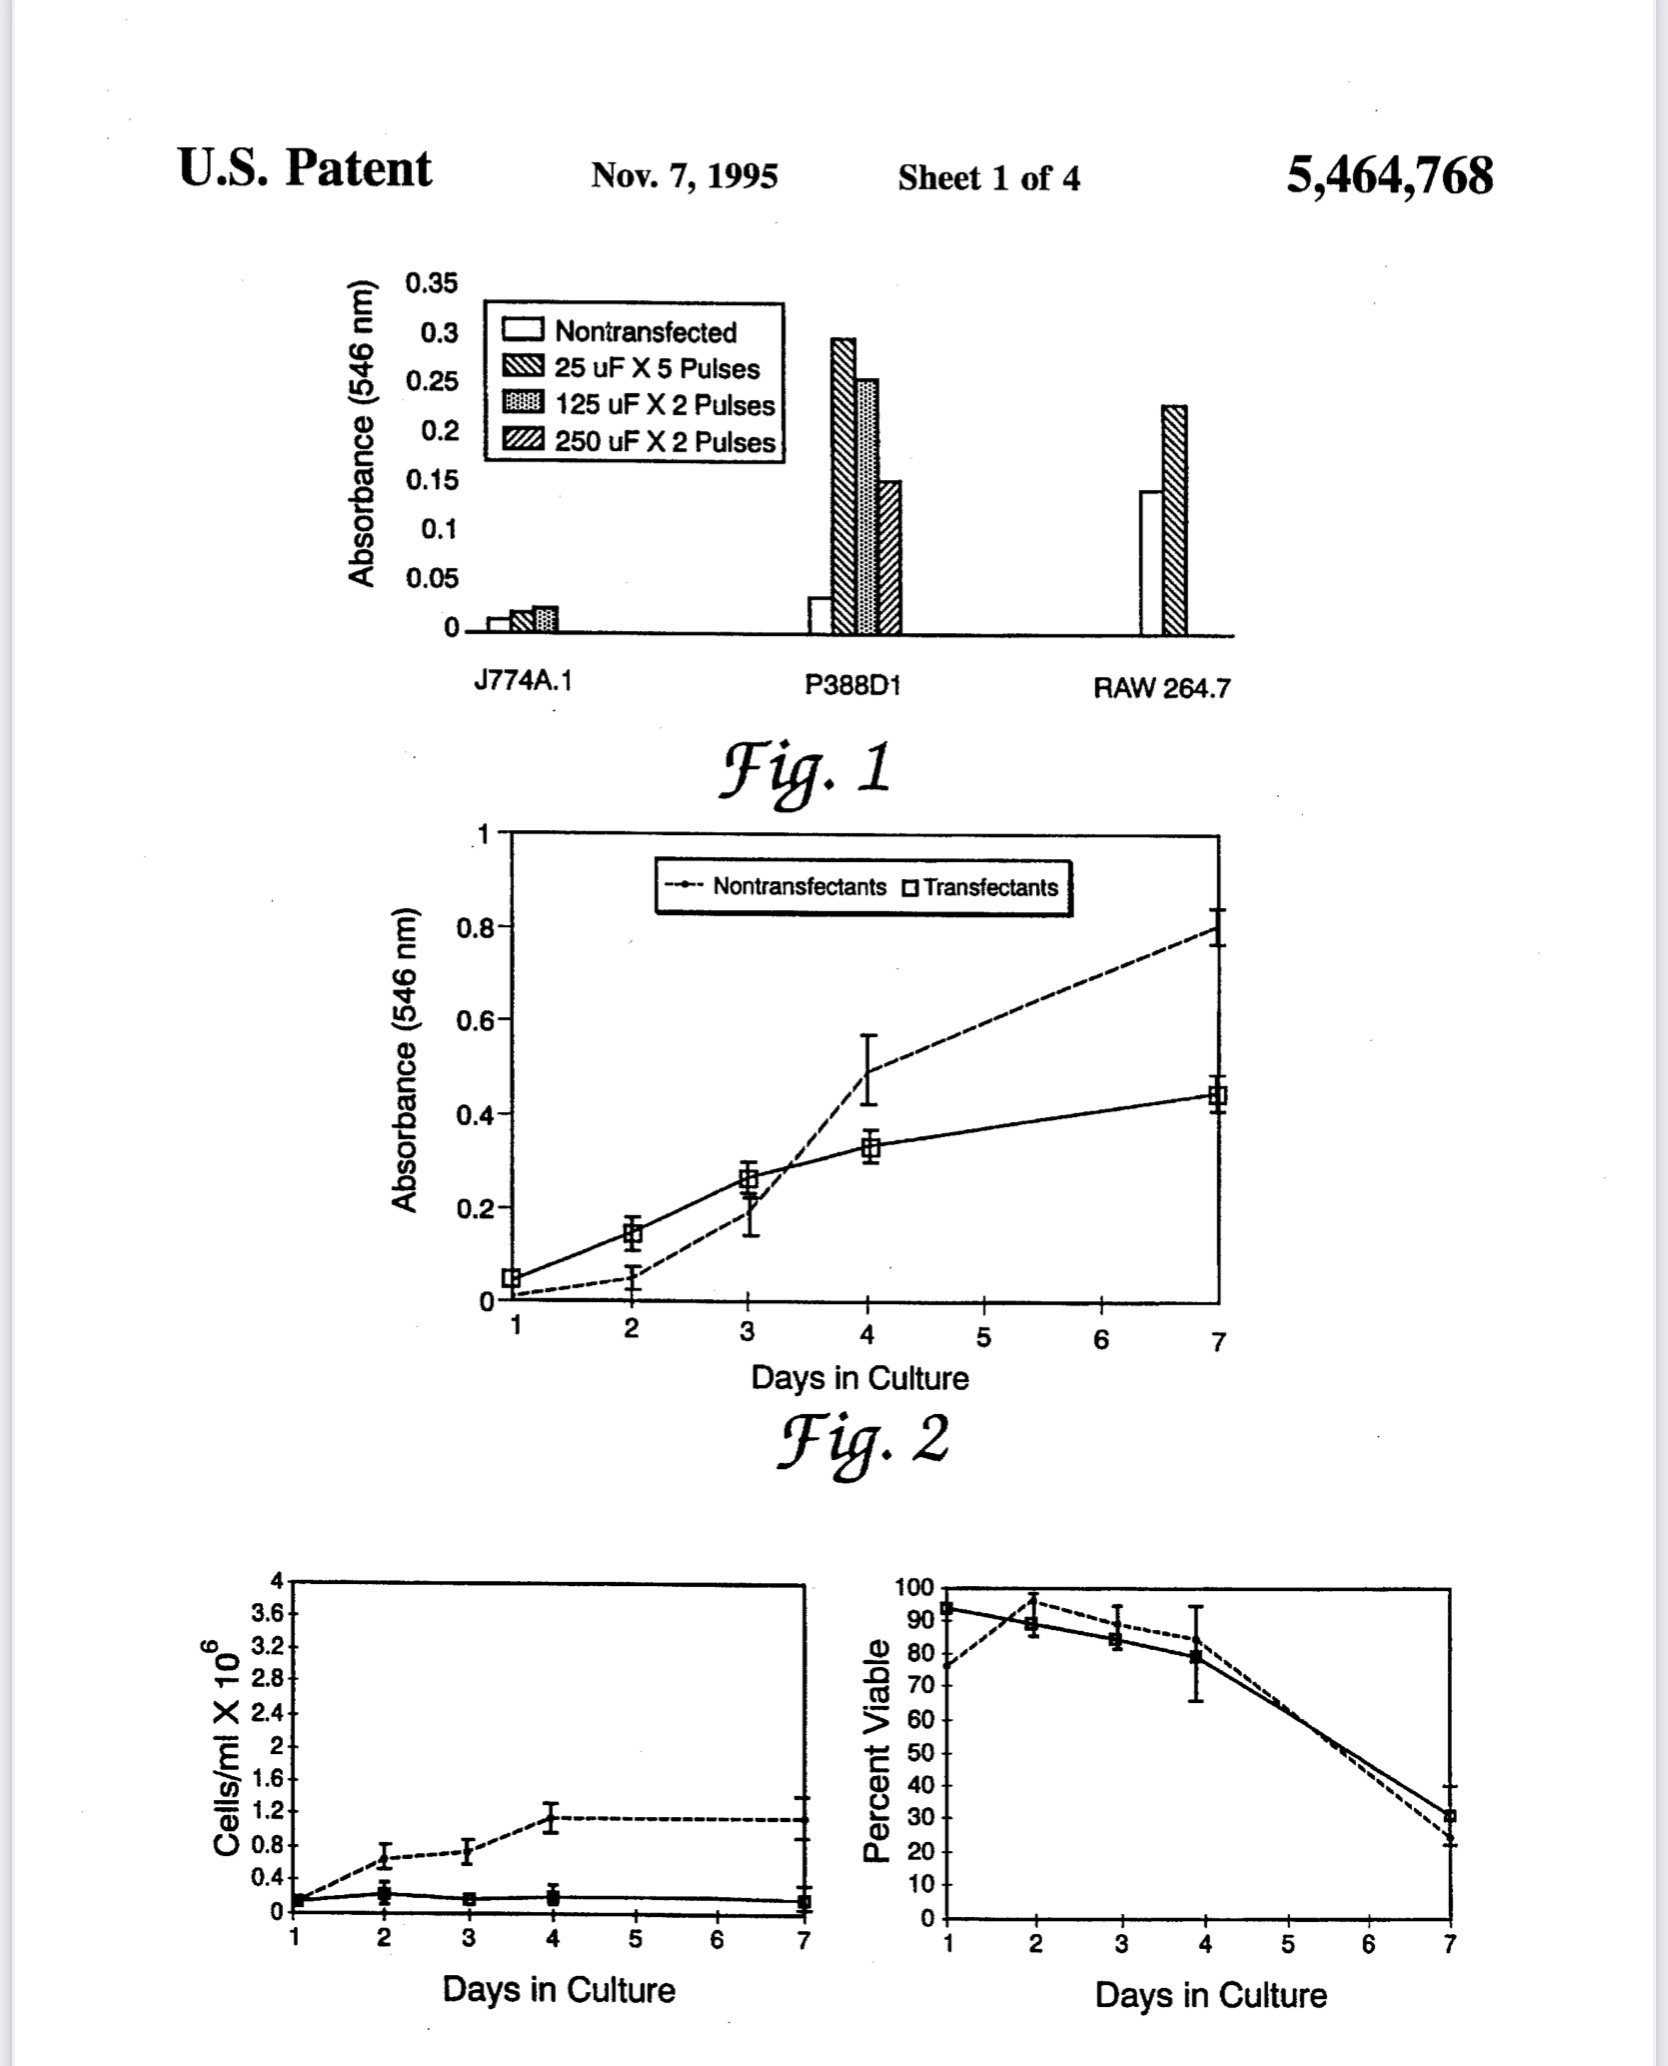
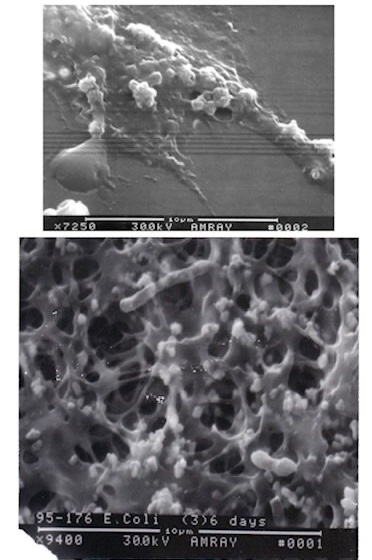
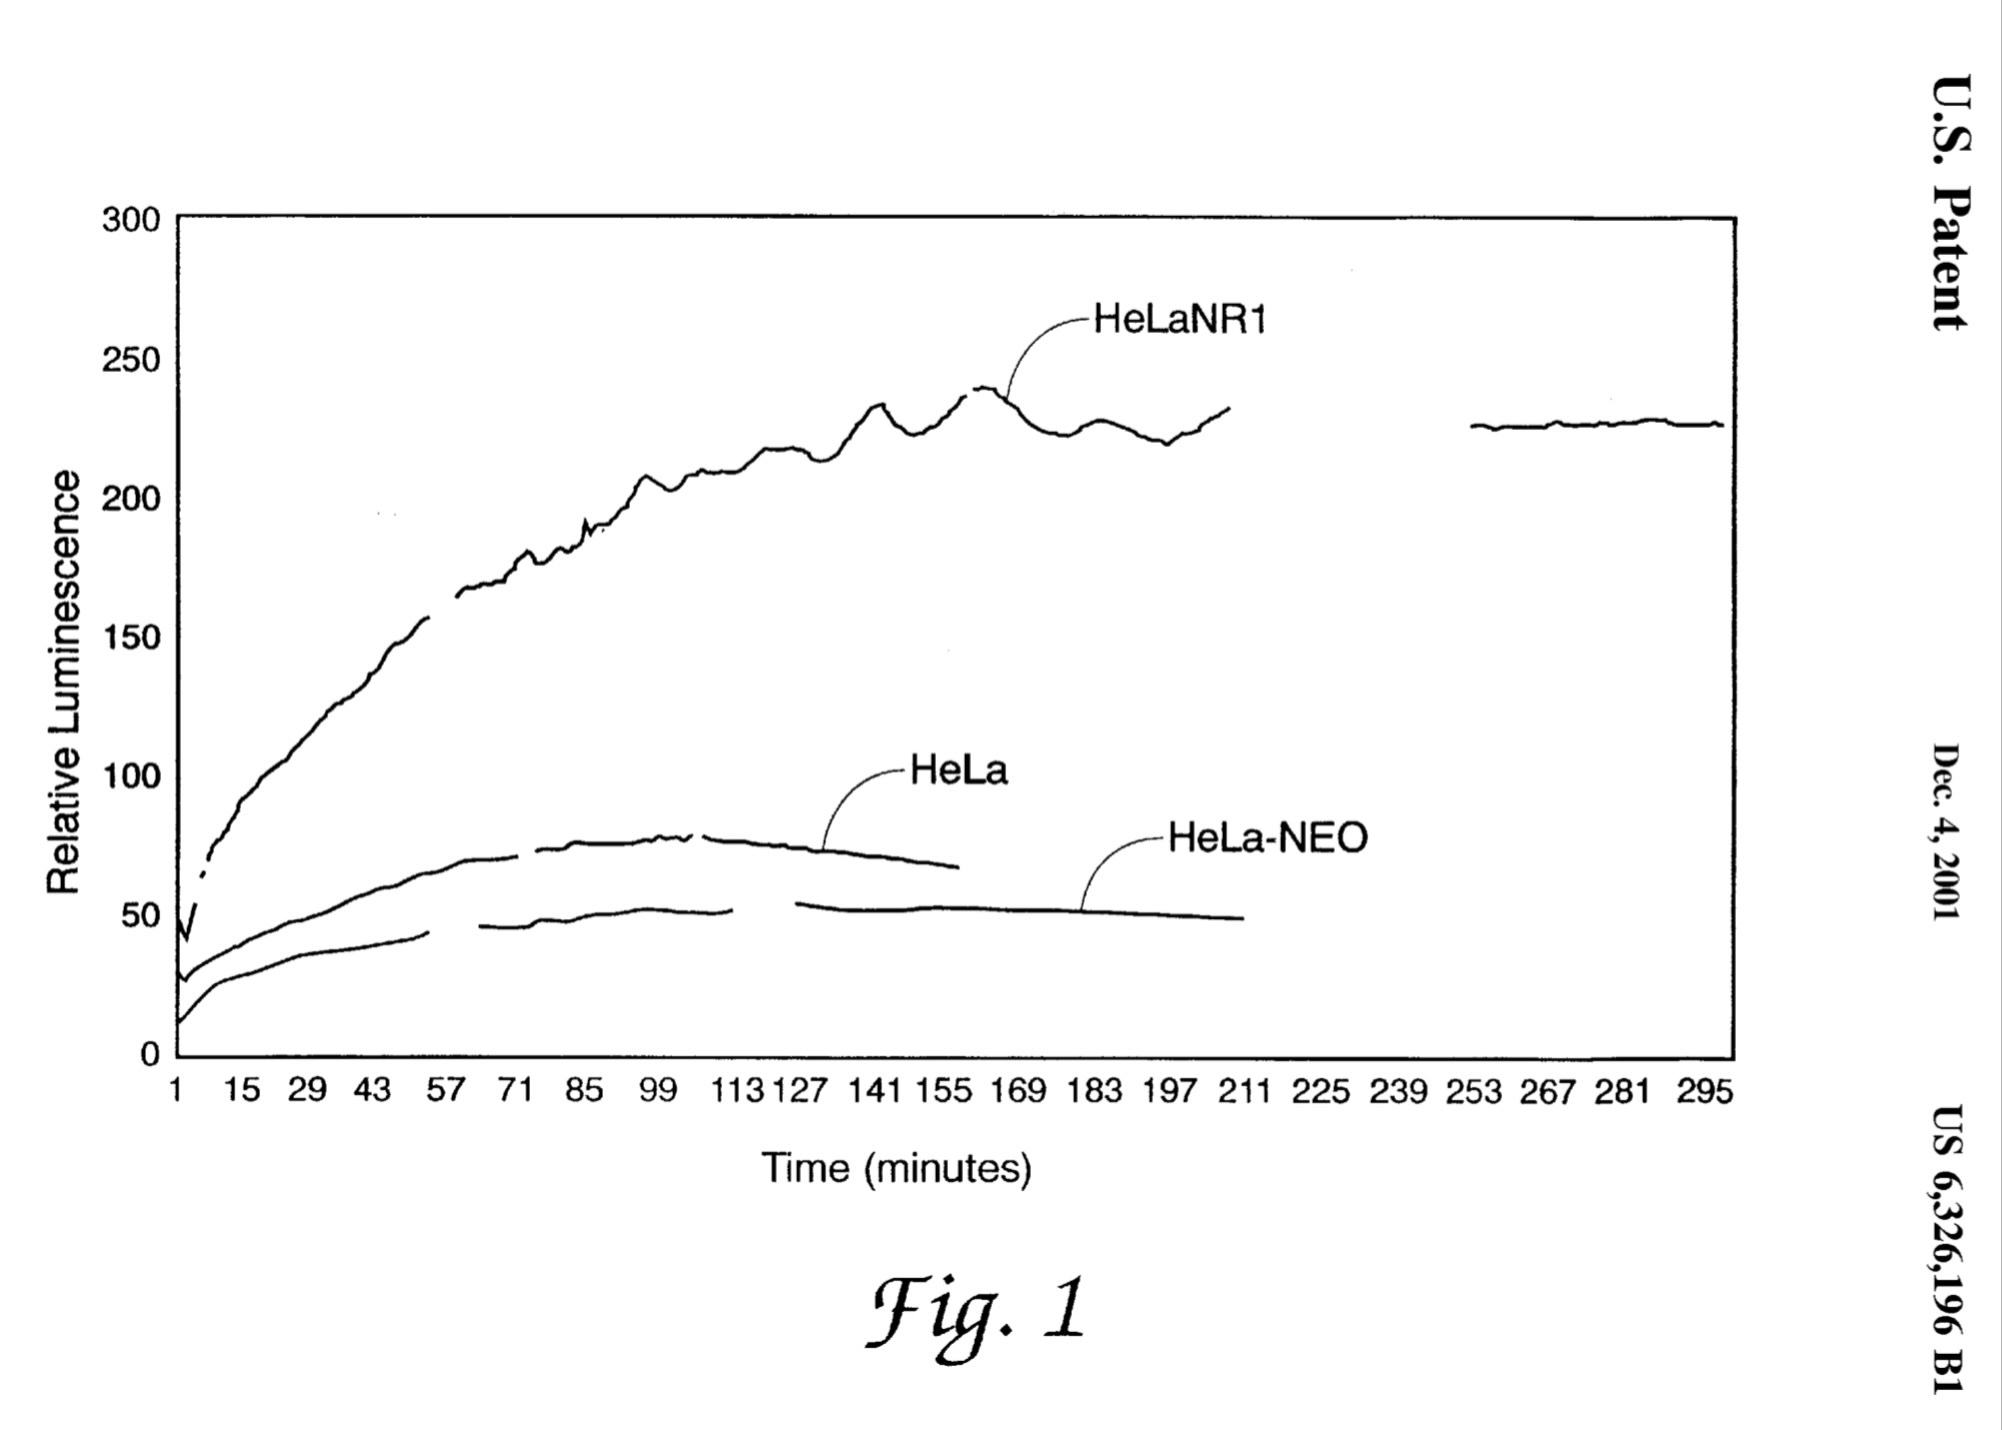
HeLa-NR1cells producing and extruding biosynthetic clusters of polymer nanoparticles (white) capable of carrying cell-synthesized RNA
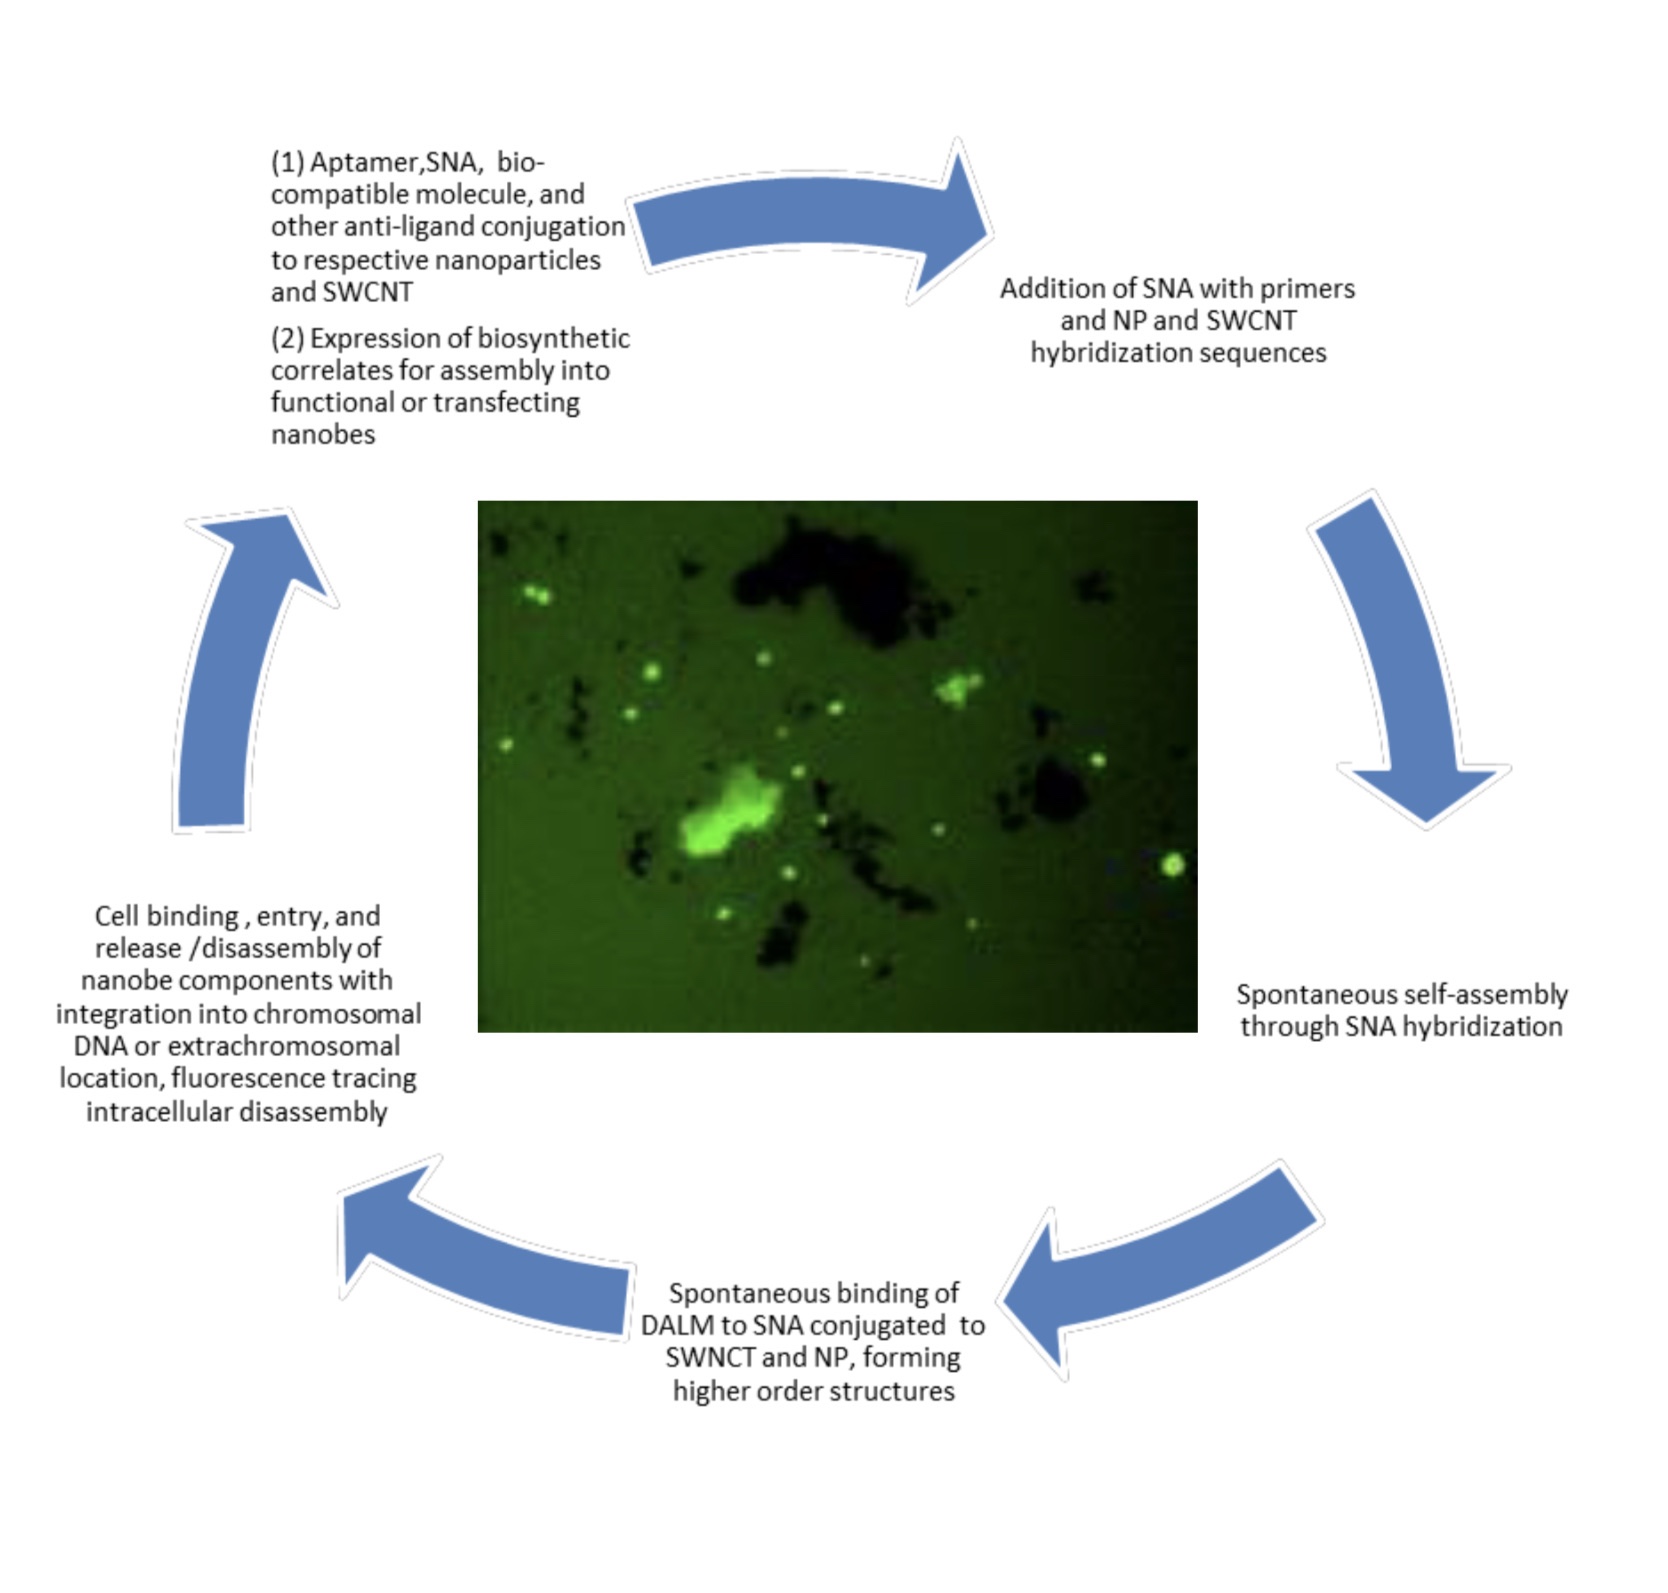
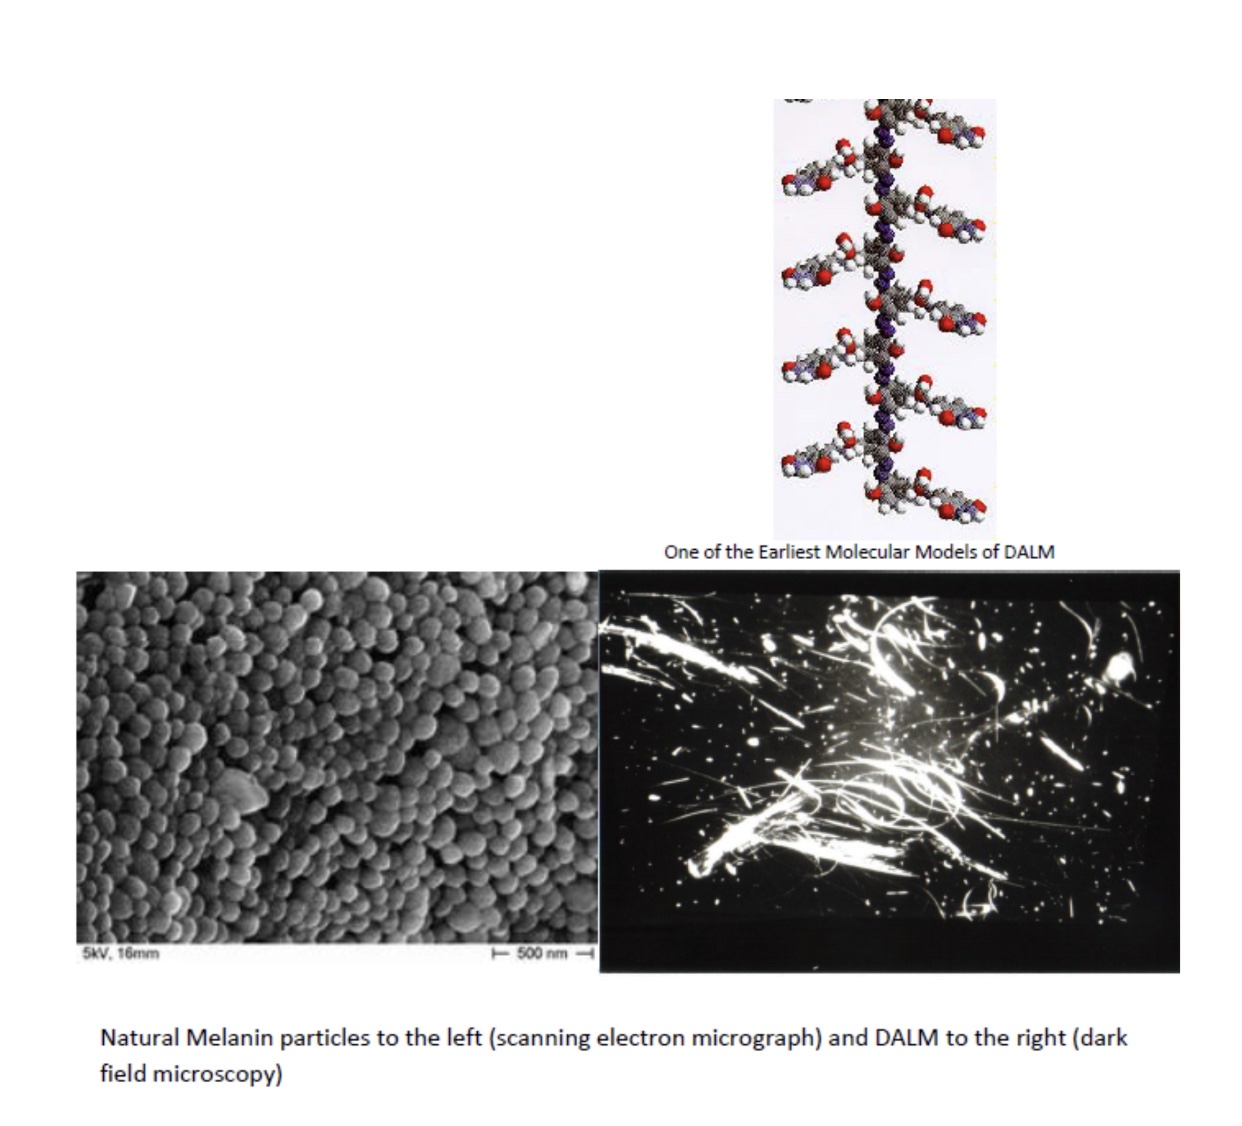
The cycle of totally synthetic Nanobes to totally self-replicating biosynthetic Nanobes. SNA= small synthetic nucleic acid; SWCNT= single walled carbon nanotube; NP= nanoparticle; DALM= diazoluminomelanin; the photomicrograph is of live cells in culture expressing Green Fluorescent Protein (GFP) after transfection with totally synthetic Nanobes carrying the gene.

Old Men Dream Dreams: Celebration of 40 Years of Research Fading Away

January 31 is the anniversary of my receiving my PhD and embarking on my One Health career. The following excerpts are from my book collection, The Black Dragon Trilogy. They are not just history. They are for now, especially in the time of COVID along with all my previous posts, and show how relevant my studies have been to COVID-19 and more to come. Acts 2:17 : “In the last days,’ God says, ‘I will pour out my Spirit upon all people. … Your young men will see visions, and your old men will dream dreams.” Everyone eventually faces their last days.

I give my own professional life story not to win your sympathy, admiration, or brag, but to show that there are different, no less authentic, paths than the academic one to great discoveries and these should not be discarded by society but judged on their stand-alone-merit. After all great things have come out of a little patent office in Switzerland. One Health is my story. The acceptance of a message should not be based on the authority of the messenger but the content of the message.

“I was eager to return to academia, to research. Because of my financial limitations, I decided to commit longer to the USAF by entering the Air Force Institute of Technology Civilian Institutions Program to obtain my PhD. I wanted one in biochemistry because I thought the molecular approach was the future of microbiology and the response to infectious agents, immunology. The USAF wanted me trained as a field microbiologist to go to Indonesia or Egypt and serve in one of the Navy field infectious disease surveillance laboratories for encephalitis virus or blood flukes (schistosomiasis) in those countries respectively. The Navy does not have veterinarians or veterinary specialists so at that time the USAF provided them and later the Army. I convinced the USAF program manager that I could get a double interdisciplinary PhD in both biochemistry and microbiology in 3 years (the limit on the length of the program for each student). I entered Texas Tech University Health Science Center, School of Medicine, Graduate School, in the Departments of Biochemistry and Microbiology, as one of their first PhD students, in the summer of 1977 at Lubbock, Texas. My dissertation research was on the cytotoxic mechanisms of peroxidases, a principle antimicrobial and anti-parasitic enzyme in granulocytes and macrophages of animals and humans. I wanted to study the effects of eosinophilic peroxidase on blood flukes (an animal counterpart of Schistosoma called Heterobilharzia americana) but my graduate committee and the safety officer would not approve of my keeping my infected snails in an aquarium in the laboratory. Therefore, I turned to peroxidase killing cancer cells. Most of the research at that time, in the laboratories there, was focused on cancer treatments. I found the Novikoff hepatocarcinoma in rats an available and convenient model already being studied in the Biochemistry Department. My biochemistry professor was studying immobilized enzymes, so I decided to immobilize peroxidase and glucose oxidase on implants in rats with this cancer. The usually fatal cancer was cured in most cases if the implants were placed at the right time and place in the rats. This led to a patent with the USAF and university. However, except for legal action and hard feelings over the patent rights, not much ever came of this laboratory “curiosity”. In 1979, just prior to me finishing my last year of my PhD, I was commissioned as a regular officer Captain in the USAF. Soon after, the Vet Corps of the USAF was dissolved, leaving the only Vet Corps being in the Army. I was transferred to the USAF Biomedical Science Corps. The powers to be tried to get me to transfer to the Army Vet Corps and gave me the tour of USAMRIID, the US Army Medical Research Institute of Infectious Disease, to entice me to transfer, but I decided not to transfer. I had to go to my next assignment at Brooks AFB, Texas, the School of Aerospace Medicine, at San Antonio, Texas. I had not finished writing my dissertation at the end of the 3-year term at Texas Tech so I requested a 6 month extension because I knew that I might not be given the time to complete it at my new assignment and get my degree. I finished my dissertation and graduated from the TTHSC in Jan 1981 with my interdisciplinary PhD in biochemistry and microbiology. My new research assignment was not in microbiology or biochemistry. I was to become a veterinary research officer in radiobiology, specifically non-ionizing radiation bioeffects, the bioeffects of radar, microwaves and radiofrequency radiation. I spent the first few weeks trying to find out what that was by reading Professor Ted (E H) Grant’s book. “The Dielectric Behaviour of Biological Molecules in Solution” (Oxford University Press, 1979). I worked in this area from 1981 until about 2000, sponsored primarily by the Air Force Office of Scientific Research. In 1994, I received the Air Force Basic Research Award for work on the mechanisms of radio frequency radiation bioeffects. I stayed involved in Veterinary Microbiology and passed the board exams for the American College of Veterinary Microbiologists, with prior tutoring from some of my professors and colleagues at Texas A& M Vet School, Dr Syed Naqi and Dr Richard Hidalgo (most recently at the Louisiana State University School of Veterinary Medicine at Baton Rouge. LA). I became a consultant to the Surgeon General of the USAF in Veterinary Microbiology (I believe the last one). This involvement was put to use in 1989, just in time, to develop a field assay for determining the viability of anthrax spores, for use in the first Iraqi War. In 2002, I became the Senior Scientist for Counterproliferation and Electromagnetic Effects of the then Air Force Research Laboratory, Brooks AFB, Tx. I retired 6 May 2011, forced retirement, after I decided not to move to Wright Patterson AFB, Ohio, as part of the Base Realignment and Closure Act implementation closing Brooks City-Base (formerly Brooks AFB). So, ended the tenure of the last Senior Scientist for Counterproliferation and Electromagnetics Bioeffects in the USAF. After retirement, I became an independent consultant serving the Defense Threat Reduction Agency in Biological Agent Defeat and in the Cooperative Biological Engagement Program in Azerbaijan (until a disagreement in approach with the prime contractor forced me to resign) and Kazakhstan until 2015. I was also accepted as a Charter Diplomate of the newly boarded specialty of Veterinary Parasitology in April 2011. I will not go into the details, but since my retirement I tried on many occasions to get employed by the USAF electromagnetic research group as a contractor or annuitant temporary employee and contacted many of my old colleagues in academia looking for a job in research, but no one would even respond or give me an interview.”— The Black Dragon Trilogy by JOHNATHAN KIEL
https://a.co/e2PwEwK

My professional mission was to stop biological agents, whether nefarious or natural, in non-permissive territory, not letting them enter the US or its territories, and to protect our military, and by extension, civilian populations, by developing detection, isolation and identification methods and neutralization and decontamination technologies and ways to confirm the kill. COVID has become my worst case scenario of an uncontrolled strategic biological agent (weapon). I had hoped “I would be welcomed back to the fight” and that “This time I know our side will win,” but my participation looks like it is not to be, even for a patriot.

Even tarnished by his claim hydroxychloroquine and azithromycin were effective against COVID-19 does not diminish Didier Raoult’s record at Faculté de Médecine et de Pharmacie, Unité de Recherche sur les Maladies Infectieuses et Tropicales Emergentes, being the leading expert on rickettsia in the world. I heard him present at the 5th International Meeting on Rickettsiae and Rickettsial Diseases, Marseille, France, in May 2008. I don’t understand Americans’ problems with the French; some of my best collaborations were with the the Institute Pasteur in Paris and CIRAD, Centre de coopération internationale en recherche agronomique pour le développement in the Caribbean. Like in the movie Casablanca, I have flown from Paris to Marseille across Africa, then the plane to Lisbon. Sometimes I wish my wanderings were like these old romantic movies, not so serious and difficult, and unglamorous but necessary. Nonetheless, I got my Ilsa, married going on 48 years. “We will always have Paris.”
Last achievements
Sealing the collaboration with a toast

My final guidance written so it may not be forgotten: “These books approach the same place, the convergence, where Pathogenic Ecology intends to be, where nature has maintained these pathogens in sylvatic and wild cycles for millennia awaiting the disturbances which lead to epidemics and pandemics among humankind and their domestic animals.”— The Black Dragon Trilogy by JOHNATHAN KIEL
https://a.co/barCq6l.

Last Word on COVID-19 and SARS-CoV-2 for 2020: Know the Enemy who we are Keeping Close: Straight Talk

This post is a summary in lay, non-technical terms, of what we know about COVID and the virus that causes it, amongst its kind. I will couch this description in military terms and as if the virus enemy is a sentient being because of my military background. The analogy is only for illustration and not proof of what I say. Our story, in late 2019, early 2020, began with a foreboding of the consequences of our happy hurried ignorance of larger life and the cost of practicing ignorance of it when confronting it head on : “Violent Delights, Violent Ends: Fire and Powder, Kiss and Consume”, “I fear too early, for my mind misgives some consequence yet hanging in the stars shall bitterly begin this fearful date with this night’s revels, and expire the term of ….. life ….. by some vile forfeit of untimely death….” William Shakespeare, Romeo and Juliet, Act 1, Scene 4”. There is an elegance in design in what we have faced and experienced when we look past the undeniable tragedy, which should never be forgotten as a great battle is remembered, which we must admit we have lost to learn from it, in our ongoing war with microbes, and the missteps that led to it. We started with underestimating our enemy. After all, most physicians’ experience with coronaviruses is the cold-causing, self-limiting, take-an-aspirin-and-call-me-in-morning ones successfully treated by benign neglect. Even the serious ones like SARS 1 (Severe Acute Respiratory Syndrome Virus, from civet cats, originally from bats), which appeared in 2003 and disappeared in 6 months, and MERS (Middle East Respiratory Syndrome Virus, from camels, originally from bats), which has only spread slowly in the Middle East and Northern Africa, were largely ignored as harbingers of something worse to come. In our arrogance and ignorance, we thought they disappeared or were restricted because of expert human interference; we ignored the warning of “some consequence yet hanging in the stars” of something much worse. Not only physicians fed this false security (besides the inevitable politicians at the top), but also veterinarians, who thought coronaviruses were under control. We have seen coronaviruses pervasively in dogs, cats, cattle and birds, but largely of the young, from self-limiting, and diminishing as agents necessitating prevention by vaccination, especially in dogs, to vaccination effective, but not fully optimal control (focusing on the pregnant females or newborns to produce immunity even if transient or against disease but not infection), in preventing large economic losses in intensive bovine, porcine, and poultry production. This requirement makes their use routine and necessary in agriculture, especially in preventing respiratory disease losses in poultry, and losses in calves and pigs from hemorrhagic diarrhea and shipping fever complex in finishing out beef cattle. However, in birds, live attenuated vaccine viruses have been detected circulating in wild bird populations, leading to potential recombination with or mutation to pathogenic strains. Only in the virus that causes Feline Infectious Peritonitis (FIP), which is usually 100% fatal in young cats showing signs but showing few signs, if any, and self-limiting when the kittens are infected with a less lethal strain of the virus (most often), was there evidence of something persistent and on occasion much more lethal. Presently, veterinarians are attempting to treat FIP with the same antiviral drugs as COVID over very protracted times, prolonging life but struggling to get cures. Not even this foreshadowing of the enemy becoming capable of new more insidious and dangerous strategies was heeded. One health appeared to learn nothing from these experiences until the stealthy tragedy of COVID was upon the world. The FIP lesson of a virus that is highly infectious and widespread in close collections of cats, which could largely be ignored and not even worth vaccination, could on occasion, when symptomatic, kill with such lethality, was attributed solely to a rare emergence of a selected highly lethal strain. However, although it appears again and again, it never seems to get an epizootic foot hold, killing only a few or one cat in a close knit group. Where does it go? Why does it keep coming back in such a limited way? No very satisfactory answers. But it surely appears to have an uncanny, but not as well developed, resemblance to the COVID modus operandi—myth of a largely non-symptomatic disease, low overall mortality, until in reality it becomes severely symptomatic and then lethality jumps sky high. These characteristics feed the denial and false claims of inflated lethality for COVID. Unfortunately, this feeds more careless spread of the virus. Could this be its evolutionary “intent” ? The major strategy change of the COVID virus from the others, especially animal ones (although all coronaviruses are zoonotic, the cold ones appearing to have originated in rodents, cattle and some unknown animal eons ago), has been to sparing the young of disease, although still being asymptomatic in most age groups, except the old and infirm. Its infectivity in cats, minks and ferrets, says SARS-CoV-2 (originating in bats) is still very much an animal virus. It still holds in common with all coronaviruses the goal of not burning through a host population so as to prevent herd immunity and always to have susceptible individuals in that population to maintain them indefinitely. Even in the most densely populated and numerous mammals in nature, perhaps only second to humans, bats, coronaviruses only infect about 10% of a given group at a time. The viruses, including SARS-CoV-2, continue to evolve by mutation and selection toward being more efficient at infection and transmission within close, tight social groups but falling off quickly when moderate barriers, like masks and good ventilation, and social distancing are implemented. Pathogenicity and lethality tend to be held in check except in individuals in a population that do not contribute to maintenance of the virus in the population, like the elderly and infirm who do not reproduce individuals vulnerable to infection and transmission. Why is COVID different from animals in these respects of populations? The answer may lie in that animal viruses establish carriers by preferring gastrointestinal infections that are not easily cleared and chronically shed transmissible virus. In other viruses, like influenza, especially in migratory birds and water fowl, it is predominantly a GI rather than respiratory virus, which most effectively maintains the birds as a reservoir rather than incapacitating or killing the birds, which would limit their ability to spread the viruses. The COVID virus has chosen a more unorthodox method to assure maintenance and transmission in the human population, although with time I believe we will find more and more asymptomatic GI shedders (by monitoring sewage which has begun) https://onlinelibrary.wiley.com/doi/full/10.1002/jmv.25825 and https://www.medrxiv.org/content/10.1101/2021.01.08.21249379v1. It has chosen to enhance anti-parasite immunity like that used by the hosts to control parasitic worm, pathogenic protozoan and fungal infestations and infections. This response often controls the number of parasites to a tolerable, but not immediately lethal, level and prevents further infestation (a process called premunition), but does not totally eliminate the parasite. In children, this form of innate non-specific immunity often rapidly clears an infection without inducing long term immunity. Therefore, they are allowed to survive, grow and reproduce more naive vulnerable individuals after spreading the virus in the population. They are also vulnerable to re-infection as they grow older. Adults can mount this type of immunity but then develop specific adaptive long term immunity, but unfortunately also “memory” of the initial innate response with a vengeance. If this “remembered” non-specific response becomes overt or is activated, as it is highly vulnerable to do, by non-viral stimuli, it can lead to autoimmunity and pro-inflammatory nonspecific disease, which has been observed in “long haulers”. The fatal severe COVID is a continuum of the infection from inapparent widespread tissue infection to a late activation of this parasite immunity to the extreme, death, without a break. This type of incomplete immunity is beneficial for resisting parasites and in tumor immunology because it is highly effective locally, but suppressed systemically to avoid collateral damage to normal self tissues.

I have observed an artificial reproduction, perhaps enhancement, or at least a mimic, of this type of reactive oxygen species innate immunity early in my research career. I described it in my first book . “Even though weaker, nonspecific cytotoxicity was expected with glucose oxidase and horseradish peroxidase, they were used. Very malignant Novikoff hepatocarcinoma (including metastases) in rats, spontaneous mammary adenocarcinomas in rats, L1210 leukemia in mice, B16 melanomas in mice, and carcinogen-induced squamous cell carcinomas in hamster cheek pouches all responded to regional or local injections of the cross-linked enzymes in saline and glucose solution. The Novikoff hepatocarcinoma responses were 50 to 100% cures in animals treated. Lactoperoxidase could be substituted for horseradish peroxidase, and similar results were obtained. However, galactose oxidase substitution or the absence of either the glucose oxidase or the respective peroxidase in the preparation failed to bring about tumor regression. L1210 leukemia in outbred white mice showed 50% cures. Treatment of B16 melanoma prolonged life from 23 days postinoculation of controls to 37 days with treatment. However, no simple dose-response curve was demonstrated..Also, smaller squamous cell carcinoma tumors responded better (some with cures) than did larger cheek pouch tumors, which did not respond at all..No direct injury to normal tissue was observed in histopathological sections of treated animals. However, some animals with heavy tumor loads (P388 lymphoma, L1210 leukemia, some with Novikoff hepatocarcinoma) died more quickly when treated than did untreated controls due to an apparent “necrotic crisis” from dying tumor tissue.”— Type-B Cytochromes: Sensors and Switches by J.L. Kiel. https://a.co/aJEAVsl. I was acutely aware of the relationship between oxidase/peroxidase innate non-specific immunity and resistance to parasites and cancer because I entered Texas Tech University Health Science Center, School of Medicine, Graduate School, in the Departments of Biochemistry and Microbiology, as one of their first PhD students, in the summer of 1977 at Lubbock, Texas, with the intent to study this anti-parasitic mechanism. My dissertation research was on the cytotoxic mechanisms of peroxidases, a principle antimicrobial and anti-parasitic enzyme in granulocytes and macrophages of animals and humans. I wanted to study the effects of eosinophilic peroxidase on blood flukes (an animal counterpart of Schistosoma called Heterobilharzia americana) but my graduate committee and the safety officer would not approve of my keeping my infected snails in an aquarium in the laboratory. Therefore, I turned to peroxidase killing of cancer cells.

This highly localized approach is necessary because parasites and cancers disguise themselves as normal host tissue and this type of immunity must attack them without confusing them with normal tissue, which could be fatal or at least highly damaging to normal tissues and organs. It is a very delicate balance that could go either way. Therefore, any treatments or vaccines must direct a response that limits early replication of the virus and do not trigger an overt systemic parasite immune response. Hopefully, the current vaccines and treatments currently being evaluated will do this.

As a final personal note, I dealt, in my professional lifetime, with trying to address these mechanisms in other infectious zoonotic diseases and where infectious agents come from, go to between outbreaks, and how to stop them from re-emerging and spreading. By my measure, what has happened with COVID-19 would have been a total failure if it had been in my purview of investigative and applied functions and responsibilities. I spent the first third of my career investigating the non-specific responses to chemical, biological, and radiation insults, especially non-ionizing electromagnetic radiation, microwaves and radiowaves, and the second two thirds investigating means to detect hidden infectious agents and to stop re-emergence of infectious agents from between outbreaks. You may question my authority and knowledge in this area and assume I should have some honored and respected position in academia or industry after my retirement from serving the military and nation. I do not. It appears the arts and sciences of attribution and Counterproliferation of biological agents, natural or nefarious, are so specialized that there is no venerable honored academic or industrial positions or no longer governmental positions that meet with my qualifications. Since my retirement in 2011 and being turned down many times for academic positions, I have only been called on by the federal government when emergency situations required my services and was summarily dismissed when the crisis passed. However, when the crisis occurs, as with COVID, is when my talents are least but albeit still critically effective if heeded. I thought that even at 71, I might be valuable in sharing my experience, knowledge and insights with those who need to follow me in these pursuits, which I did in the military, but am not allowed to do now except by my books, past publications and currently this blog. I will continue as long as one person reads this blog and am able to continue.

A Hypothesis for “Long Haulers“ of COVID-19: A T Cell that just can’t forget (Th17) and keeps fighting Ghosts

How can symptoms of COVID-19 persist after the virus is gone? The answer may lie in the type of immune response triggered by SARS-CoV-2, which resembles one more familiar to those studying the immune response to worm to protozoan parasites. I mentioned this in earlier posts citing observations of clinical characteristics of COVID and how they resembled the response to a parasite rather than a virus. Parasite immunology more closely resembles tumor immunology than that of responses to many viruses and bacteria. This cross reactivity between tumor immunology and the immune response to SARS-CoV-2 has been dramatically illustrated in a recent case of a rare remission of advance Hodgkin lymphoma in conjunction with COVID (https://onlinelibrary.wiley.com/doi/10.1111/bjh.17116). The host must mount a different kind of response to parasites because of their many strategies to evade the immune system, the innate and adaptive components. Therefore, animals and humans have developed a different series of cellular and humoral components unique to parasites, but often with potentially severe collateral damage to normal tissues and organs. There is a delicate balance between controlling a parasite infestation so that it does not consume the host and so completely destroying the parasites that the host “burns down the house to get rid of the rats”, auto destruction of the host in the process of eliminating the parasite and confusion between parasite antigen and self antigens (autoimmunity) https://downloads.hindawi.com/journals/iji/2014/651503.pdf. The remaining “memory” of this response, after the virus is gone, is continuously reactivated by a broad range of stimuli https://jlb.onlinelibrary.wiley.com/doi/epdf/10.1189/jlb.0313113. This primitive process, discussed in my book Type B Cytochromes: Sensors and Switches and cited in previous posts, is built on anticipatory responding to potential pathogens, toxins and physical insults before those insults are actually known or specifically identified. This is good for evolutionary survival but can lead to unnecessary overt nonspecific responses and collateral damage. What is the evidence for such a hypothesis in regards to COVID-19 and how might it lead to treatments, especially for long haulers? As stated in a previous post, the immune response of hospitalized COVID-19 patients falls across a spectrum of immune responses in 3 categories: (1) antiviral (some macrophages and dendritic cells, natural killer cells, cytotoxic T cells, helper and suppressor T cells, antibody making B cells and plasma cells, and gamma interferon; other interferons made by tissue cells: alpha and beta); (2) anti-parasitic granulocyte white blood cells (some special B cells that make IgE, eosinophils, basophils (in tissue mast cells), and all kinds of biochemical mediators: histamine, Prostaglandins, leukotrienes, and kinins); and (3) anti-bacterial and fungal (granulocyte: neutrophils, and monocytes and macrophages). COVID-19 can move through all three types. The worst and most likely cause of the long hauler syndrome is type 2 which was meant for worms and other multicellular localized parasites and can be locally severe and if generalized, fatal. The serum concentrations of IL-17A (a protein that recruits monocytes and neutrophils to an inflammatory site produced by Th17 lymphocytes) and IFN-γ, but not TNF-α or IL-6 (the pro-inflammatory culprits), decrease with age of patients (this might argue against Th17 memory cells being the source of long haulers); therefore, gamma interferon’s ability to prevent viral replication but not induce oxidative damage to host cells, as with TNF-α, is more important in children’s responses. However, as stated in a previous post, evidence supports decline in soluble IL17A receptors, which block TNF-alpha and interferon gamma production by competing with the cellular T17 cellular receptors, leads to more severe COVID19 (supporting Th17 cell involvement). Adults show a more robust T cell response to the viral spike protein compared to pediatric patients shown by increased expression of CD25+ on CD4+ T cells and the frequency of IFN-γ+CD4+ T cells. Also, serum neutralizing antibody titers and antibody-dependent cellular phagocytosis are higher in adults than in pediatric COVID-19 patients. The neutralizing antibody titer increases with age while the IL-17A and IFN-γ serum concentrations decrease. Children seem to be resistant to the severe effects, except in some instances when they display multiple organ inflammation, Kawasaki-like syndrome, because they produce a lot of the anti-inflammatory cytokine IL10. The responses of neonates compared to adults change from increased IL-10 as neonates to balanced IL-10/T helper type 1 (Th1)/Th2/Th17 cytokine levels early in life. This allows protection from pathogens but reduces the chances of severe inflammatory reaction. Th17 cells are the most probable mediators in many human autoimmune and chronic inflammatory disorders, including psoriasis, Crohnˈs disease, rheumatoid arthritis, Multiple Sclerosis, and uveitis https://www.frontiersin.org/articles/10.3389/fimmu.2018.01112/full. The development of pathogenic Th17 cells relies on signals from multiple cytokines: IL‐1, IL‐23, and IL‐6. TGF‐β (transforming growth factor) can promote Th17 development and induces a Th17 response which promotes intestinal muscle hypercontractility that drives worm expulsion. TGFβ-activation by dendritic cells yields this Th17 induction and intestinal contractility and facilitates the expulsion of the parasite Trichinella spiralis in mice. This unique immune response to intestinal helminth expulsion beyond that of classical Th2 driven immunity, highlights the importance of IL-17 in parasitic disease. Th17 protection against parasites is very broad spectrum extending to Th17 cells’ providing robust protection against Trypanosoma cruzi, the intracellular protozoan parasite that causes Chagas disease. Parasites that establish long term chronic infections suppress Th17 immunity by modulation of antigen-specific CD4+ T responses. This is seen in human infection with the worm parasite Strongyloides stercoralis https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4546867/pdf/nihms-704134.pdf. Th17 cells of infected people showed significantly decreased responses upon antigen-stimulation, but following treatment, significantly increased the antigen-specific responses of Th17 cells. Th17 cells produce pro-inflammatory cytokines, including IL-17A, IL-17F, and IL-22. This cytokine production not only promotes accumulation of immune cells, such as macrophages, neutrophils and lymphocytes, at inflammatory sites, but also can cause collateral tissue damage. Other Th17 cells can negatively regulate immune responses by secreting immunosuppressive factors, such as IL-10 as noted in the response of children to COVID. Th17 cells are required for vaccine-induced protection from pulmonary infection with the pathogenic fungi Coccidioides posadasii, Histoplasma capsulatum, and Blastomyces dermatitidis, fungal pathogens causing systemic mycoses in humans. IL-17 is required for neutrophil and macrophage recruitment to the lungs. This balance is evidently what helps dispose of or suppress parasites and perhaps SARS-CoV-2 virus, or, if out of balance, severe acute or chronic persistent long hauler pathologies https://www.thermofisher.com/us/en/home/life-science/cell-analysis/cell-analysis-learning-center/immunology-at-work/t-helper-17-cell-overview.html. Some in vitro experiments suggest a benefit from Vitamin D because of its effects on Th17 cells. These cells are characterized by the chemokine receptor CCR6, RORC expression, and production of IL-17A, IFNγ, and TNFα. Using rheumatoid arthritis (RA) as a model of autoimmune disease, investigators demonstrated that pro-inflammatory memory CCR6+ Th cells can switch into anti-inflammatory cells by treating them with the active vitamin D metabolite 1,25(OH)2D3. Memory CCR6+ Th cells were sorted from healthy controls or treatment-naïve patients with early rheumatoid arthritis (RA) and cultured with or without 1,25(OH)2D3. Vitamin D3 inhibited pro-inflammatory cytokine production, IL-17A, IL-17F, IL-22 and IFNγ, in memory CCR6+ Th cells from both healthy controls and RA patients. This inhibition was accompanied by induction of anti-inflammatory factors, IL-10 and CTLA4 https://www.frontiersin.org/articles/10.3389/fimmu.2019.01504/full. Perhaps, this approach provides a means to test the hypothesis that Th17 memory cells are the root cause of long haulers. Also, antioxidants may help because the pro-inflammatory cytokines enhance the production of reactive oxygen species which are mediators of the anti-parasitic effector mechanism and collateral pathology. These benefits remain to be seen.

The anti-parasitic immune response leading to long haul and neurological disease has gained further support in a new paper showing the involvement of the cytokine CCL11, eosinophil chemotactic protein and eotaxin-1 (https://www.biorxiv.org/content/10.1101/2022.01.07.475453v1.full.pdf).

COVID Vaccines: The Danger of Over Interpreting In Vitro Studies: We are more than the Sum of Our Parts

Concerns over the safety of vaccines and effectiveness of non-pharmaceutical control measures have led to and will lead to worse outcomes for COVID, especially in the US, where such resistance has led to tragic devastation. Therefore, any over interpretation of worst case scenarios will lead to self-fulfilling apocalyptic outcomes. This can only be prevented by open and honest assessment of risk/cost/benefits of any such approaches https://www.medrxiv.org/content/10.1101/2021.01.29.21250653v1.full.pdf. The latest most concerning challenges to vaccines are their potential to instigate autoimmunity, allergic reactivity, their ability to enhance infectivity, and their loss of effectiveness because of the appearance and rapid spread of mutant strains of SARS-CoV-2. Another more common place and older concern for attenuated vaccines is their possible reversion to pathogenic forms. I will start with this last concern first because it has some well-documented clinical examples. The earliest was with the first vaccine, smallpox vaccine, cowpox or now vaccinia (DNA from an early 1902 sample of smallpox vaccine showed that it was 99.7% similar to horsepox virus, now extinct). This vaccine is a close attenuated relative of smallpox virus, usually only causing localized lesions, skin vesicles, followed by erosions and ulceration, at most resulting in a single scar. However, it can cause generalized vaccinia, with widespread reddening, inflammation and pealing of the skin and on very rare occasion heart damage and even death (eczema vaccinatum, accidental inoculation, and progressive vaccinia). The spread of the virus from inoculation sites during active infections to others, especially amongst children, was common in the past. But we must never forget that without this vaccine, smallpox could have never been eradicated. We would still be living with its up to 30% mortality and life-long disfigurement.

A lesser known reversion was seen with Venezuelan Equine Encephalitis modified live virus vaccine, TC-83 virus, was developed as an anti-biological warfare vaccine in the early 1960’s at USAMRIID (US Army Medical Research Institute of Infectious Diseases) and transitioned to a commercial horse vaccine in the 1970’s and eventually was replaced with a killed vaccine. VEEV was attenuated into TC-83 by 83 serial passages in guinea pig heart cells. It was first tested extensively in horses during the 1971 Texas VEE epizootic. Although the vaccine produces viremia, fever and leucopenia in horses, neutralizing antibodies are generated with protection from VEEV challenge. TC-83 produces seroconversion in about 80% of humans (neutralizing antibody titers ≥20) but mild to moderate flu-like symptoms. TC-83 is the result of only 2 attenuating mutations among the 12 mutations that accompanied in vitro passage of the Trinidad donkey strain. These mutations could revert in vaccinees, which also presented a risk of epizootic amplification. To produce a more stably attenuated VEEV vaccine candidate, the virulent Trinidad donkey genome was cloned in cDNA and attenuated by inserting either point mutations or a PE2 cleavage-signal mutation combined with an E1 gene resuscitating mutation. The latter strain, called V3526, is safe and immunogenic for mice and nonhuman primates, and appears superior to TC-83 in rodents. V3526 has a lower risk for environmental transmission and distribution. TC-83 was transmitted by mosquito vectors and was isolated in mosquitoes collected in Louisiana during the 1971 VEE epizootic/epidemic. Efforts were made to improve its safety by genetic modification to prevent its ability to infect insects. This recombinant virus further attenuated TC-83, but was completely unable to infect mosquito cells or mosquitoes in vivo. Currently, commercial equine vaccines marketed in the U.S. consist of inactivated TC-83, often combined with inactivated eastern and western equine encephalitis viruses.

“The small and simple VEEV has one more trick which it shares with the plant Tobacco Mosaic Virus; it can resurrect itself from broken pieces. The nsP4 sequence in VEEV is very similar to the replicases of three plant viruses, including Tobacco Mosaic Virus. The Brooks Lab performed a critical experiment using the RetroXpress (TM) system of Clontech derived from a retrovirus which could transfer genes but could not infect and replicate, my group at Brooks constructed a new virus that contained the nsP4 sequence inserted into this platform and expected that the new virus could infect cells but not replicate. It not only infected (transfected) marker genes into the target mammalian cells but also formed plaques of transformed cells (those which resembled cancer cells and formed uninhibited growth mounds of cells). These grew and multiplied in the cell culture. A new complete infectious virus had formed. How? Tobacco Mosaic Virus has been shown to repair and reactivate after exposure to UV with the help of an unknown plant nucleic acid repair system (Multiplicity Reactivation: Recombination). Since we inserted only the nsP4 protein into the host cells co-infected with the defective retrovirus, we proposed that the new virus used cellular RNA dependent RNA polymerase in conjunction with the expressed nsP4 to form a repair complex which constructed a chimera virus from the retroviral pieces and other unknown viral nucleic acid components inherently present. Perhaps, the infections by killed virus from killed vaccines previously reported were not just because of contamination with whole live virus but with components which survived the formalin damage and were reassembled into whole restored infectious virus, albeit at a less effective infectious dose of original broken pieces. Intact VEEV will produce a transmissible infection with as little as 12 PFU (plaque forming units equivalent to 10 virions for a multiplicity of infection of 1 but more likely 10X10 = 100 virions). I have speculated that these broken viruses, if reconstituted from broken virions or free RNA would require 10e6 units to make one intact virion.” — The Black Dragon Trilogy by JOHNATHAN KIEL. https://a.co/gtIO9aR
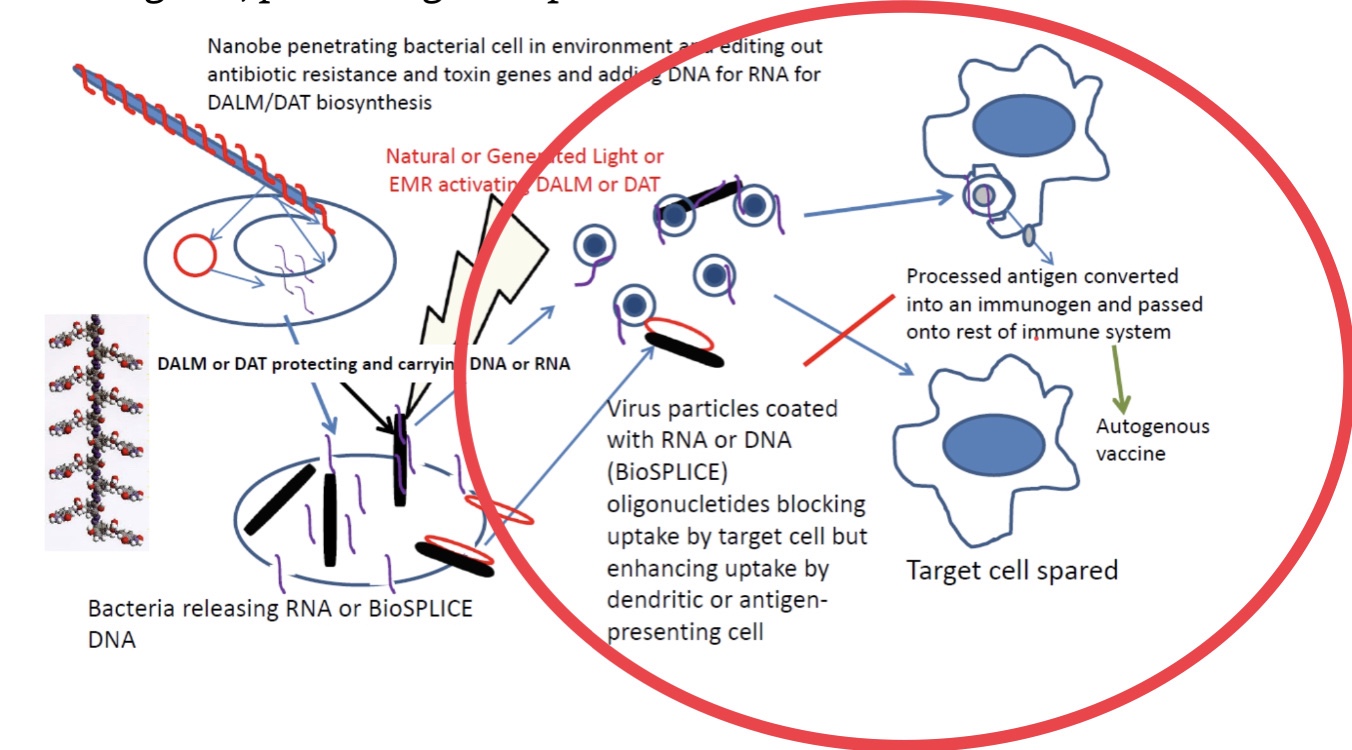

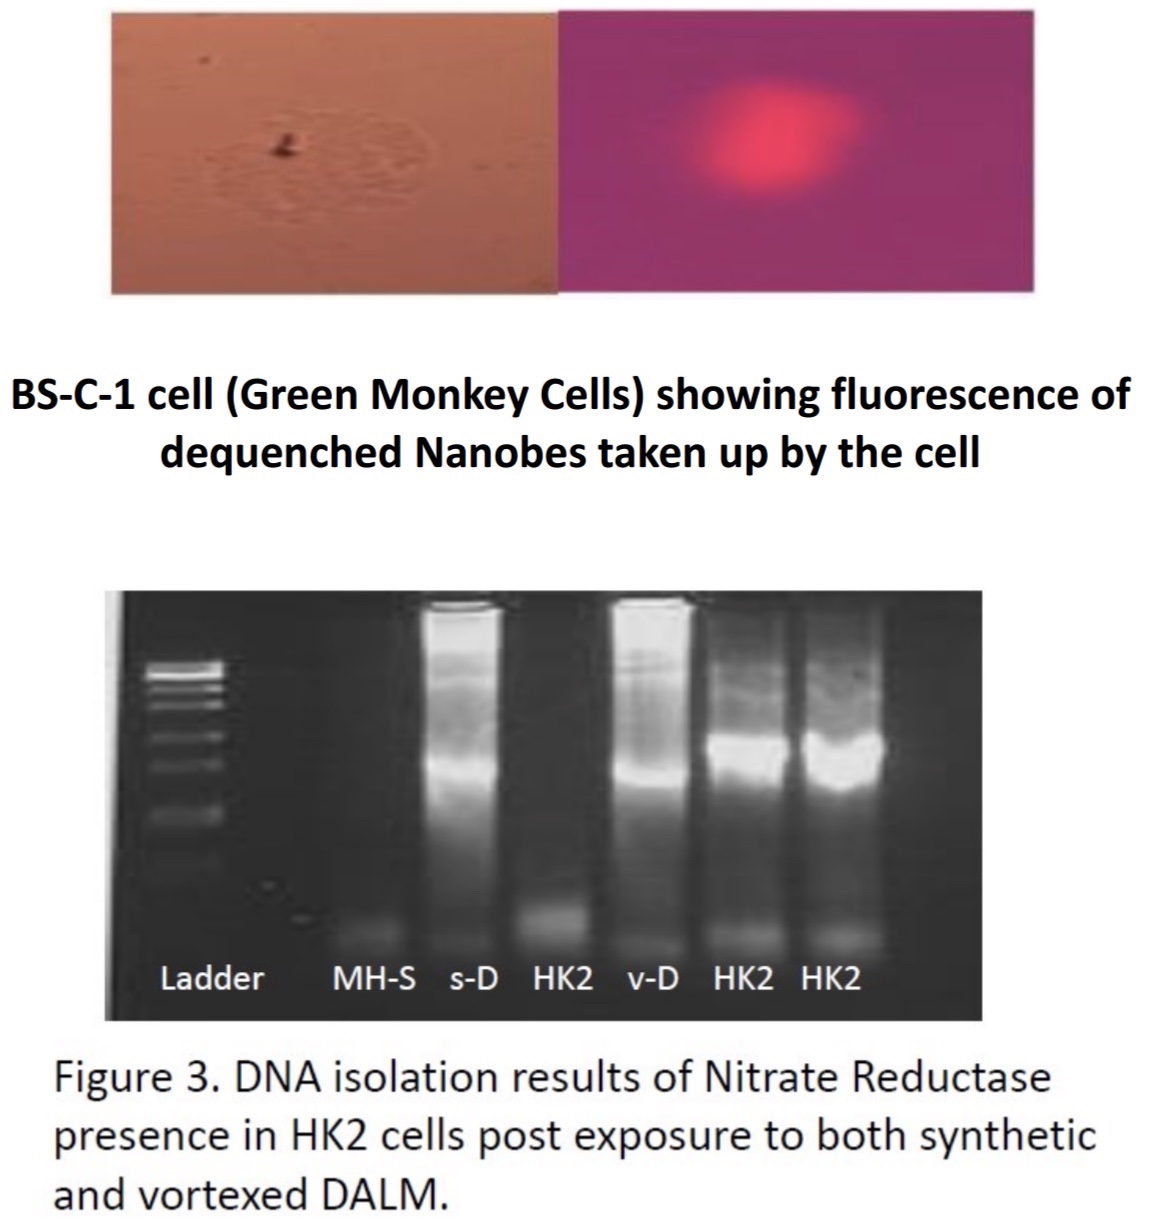
The third example of a problematic attenuated live vaccine still causing trouble is Sabin modified live polio vaccine. The first, vaccine-associated paralytic poliomyelitis (VAPP) was recognized in the early 1960s. VAPP is a very rare and occurs sporadically when a dose of oral live polio vaccine reverts to neurovirulence and causes paralysis in the vaccine recipient or a nonimmune contact. VAPP can be in immunologically normal vaccine recipients and their contacts as well as among persons with immunodeficiencies, defects in antibody production. There were live vaccine-associated outbreaks in Madagascar and South Sudan in 2014. Eight newly identified persons in six countries were found to excrete vaccine virus, and a patient in the United Kingdom was still excreting the virus in 2014 after more than 28 years. Reported by ProMed on 15 Dec 2020 were three new polio cases in Sierra Leone for the first time in 10 years. The cases were recorded in Kambia, Tonkolili, and Western Area Rural District. The cases were not from the wild poliovirus strain, but were vaccine derived. Only 2 countries worldwide continue to have wild poliovirus transmission: Pakistan and Afghanistan; thanks to worldwide polio vaccination. Because of violent resistance to polio vaccination in these two countries, polio persists and cannot be eradicated. Killed Salk polio vaccination is now once again being used with no chance of reversion because it is a killed vaccine, as the risk of live Sabin vaccine now out weighs its benefits.

The severe reactions to vaccines (anaphylaxis) are extremely rare for humans and animals and are expected to be no worse for COVID vaccines. They are often, when they do occur associated with adjuvants and additives, rather than the primary immunogen, except for perhaps some vaccines in animals, like that for leptospirosis (actually a bacterin).

Autoimmunity is related to allergic reaction but distinct, especially in regards to SARS-CoV-2 pathology. I have discussed the immune response to the virus in detail in previous posts. As a reminder, the virus has the unusual association of autoantibody against interferons as a marker of severe disease. Also, unlike other animal coronaviruses, SARS-CoV-2 is more severe in adults than children, in general. The animal ones are more severe in the young than old. What is a plausible explanation, or hypothesis? Children have a more robust innate immune response, including interferon, than an adaptive immune (antibody) response than adults, but they have higher amounts of circulating soluble interleukin 17 receptors which help reduce the cellular innate pro-inflammatory response mediated in immune cells through membrane-bound IL-17 receptors. I have pointed out, in an earlier post, that the uncontrollable innate immune response yields reactive oxygen species that cause considerable local collateral host cell damage and death. Therefore, taking out interferon, and the subsequent wide distribution of infectious virus, then leads to antibody against virally infected cells which directs antibody-dependent cell cytotoxicity, causing a whole host inflammatory response, and collateral cellular, tissue to whole organ damage and failure. The pro-inflammatory activity of whole virus leads to a by-stander adjuvant effect which can activate forbidden B cells to produce the self antibody, i.e. anti-interferon. In adult immune systems, having seen more related viruses than the naive immune systems of children, this is more likely to happen. A good humoral and cellular immune response, triggered by a vaccine directed against specific antigens that direct neutralizing antibody response avoids this outcome because it takes out virus before it can spread widely in the body.

This line of thinking leads to a more recent disconcerting response to the virus that involves a minor antibody directed to a critical part of the binding portion of the viral spike protein (S1) https://www.biorxiv.org/content/10.1101/2020.12.18.423358v1?fbclid=IwAR3D1MJ-SyW9wLeqrRV6pdSP6ToUwpaLjbB5LK2oA4B0b9iYjJ4RTvYs_PQ. The paper provides evidence that minor antibodies from COVID patients’ serum bind to part of the S1 spike protein that enhances the binding to ACE2 viral receptors and uptake of infectious virus in cell culture in established cell lines. They further raise issue that a vaccine could enhance viral uptake and disease by extension of this observation to the whole human. Unfortunately, such a stretch will provide support to those who oppose vaccination. This leap may be moot from the get go because patients have circulating soluble ACE2, derived from proteolytically cleaved membrane bound ACE2. First, there is no evidence that any vaccine enhances viral infectivity in vivo. Second, these soluble receptors would first see and soak up systemic virus, especially if its binding were enhanced by the antibody. Then, immune cells would take up these immune complexes and dispose of the virus. In addition, the antigens selected for the vaccines are specifically selected to optimize induction of neutralizing antibody.

The vaccines released for use so far have had exceptional efficacy in generating neutralizing antibody. The fear of a mutation in SARS-CoV-2 has come to fruition but those so far such as in mink, have increased efficacy of transmission and infection but not pathogenicity. Coronaviruses have a large RNA genome and can therefore undergo more mutations without significant functional change than smaller genome RNA viruses. They also have a proof reading polymerase to reduce replication mistakes (mutations) unlike other error prone RNA viruses like HIV. However, they can undergo selection pressure for advantageous mutants, when necessary, generated by mutations mediated by Nsp14 exonuclease in independent coronaviruses, resulting in a 15–21-fold decrease in replication fidelity. Therefore, the presence of this exonuclease can clearly influence viral RNA mutation rates and the generation of quasi species when needed. Therefore, there is a continuous tension balance between the polymerase and the exonuclease to only produce mutations that are favored by environmental selection pressure. The latest of greatest concern, VOC 202012/01 variant, occurred in the UK. This variant has a mutation in the receptor binding domain (RBD) of the spike protein at position 501, where the amino acid asparagine (N) has been replaced with tyrosine (Y). The shorthand of the mutation is N501Y, also designated as S:N501Y, because it is in the spike protein. This variant carries many other mutations, 14 amino acid (AA) mutations, 6 non-AA altering mutations, and 3 deletions, notably including 69/70 deletion: this double deletion has occurred spontaneously many times, and likely leads to a change in the shape of the spike protein; P681H: near the S1/S2 furin cleavage site, a site with high variability in coronaviruses, which has also emerged spontaneously multiple times; ORF8 stop codon (Q27stop), a mutation not in the spike protein but in a different gene (in open reading frame 8), the function of which is unknown. Similar mutations have occurred in the past such as in Singapore, in which one strain with this type of mutation emerged and disappeared. Preliminary analysis in the UK indicates this variant is significantly more transmissible than previously circulating variants, with an estimated potential to increase the reproductive number (R) by 0.4 or greater with an estimated increased transmissibility of up to 70%. There is no indication, at this point, of increased disease severity associated with the new variant. A few cases of this new variant have to date been reported in Denmark and the Netherlands. Another similar mutant has arisen in South Africa, with structural changes in the spike protein, which is still being evaluated for impact. However, in a recently released study, pending peer review, the Pfizer vaccine has been shown to still induce neutralizing protection to the mutants https://www.biorxiv.org/content/10.1101/2021.01.07.425740v1.full.pdf. One must remember that mutations in the spike protein are not limitless. They must conserve essential structure that allows binding and entry of the virus https://science.sciencemag.org/content/sci/371/6526/284.full.pdf. The ACE2 viral receptors do not mutate as fast as the virus so they limit what variations in the virus are still tolerable for infection. If coronavirus behavior is to hold true, the most efficiently transmitted virus with the lowest mortality necessary to eliminate less than ideal virus replicating hosts, and that which does not preferentially infect much more than 10% of the susceptible population, especially when simple non-pharmaceutical methods as distancing, good ventilation and wearing of masks, are so effective, will prevail to maintain itself in the general population indefinitely. This persistence at a low percentage of the susceptible population is the nature of coronaviruses in animals.

One last note, the Brooks USAF AFRL CPT groups’ seeking of aptamer-based anti-pathogens to bind toxic components, inhibit target cell binding and uptake, and re-direct existing immunity, natural or vaccine induced, rapidly toward new, emerging and re-emerging pathogens, including viruses, was designed to address outbreaks like COVID without always having to resort to the Herculean efforts that have been necessary to develop COVID vaccines. The failure or inability to apply the same efforts, as we have had to to rapidly develop COVID vaccines, to the insidious smoldering problem of antimicrobial (antibiotic) resistance was also the motivation for developing this new technology, as well as to relieve the costs and socioeconomic impacts of addressing these problems by conventional, albeit modern technological, versions of biomedical approaches.

Going into a Hiatus: Maybe See You on the Other Side: But First Before I Go….

We are experiencing a rough start to a new Executive Federal Administration. They are left with a legacy mess to cleanup. The roll out of the vaccines for COVID is much less and slower than expected—-unless things change, for many if not most US residents, it will be too little and too late. Even small countries are rolling out new vaccines. If the ruinous beginning of COVID that the previous WH Administration brought us is any measure and is not corrected, the US will follow the same disastrous path for a while at least, and be behind even countries like Vietnam in vaccination, as it was in non-medical, physical controls, with inequitable progress. My attempts to provide current, correct, and relevant information on SARS-CoV-2 and COVID, and previously possible innovative solutions, and lessons about preventing such zoonotic disease incursions, spillovers, in the future, have been largely ignored or marginalized. Therefore, I am taking a break and allowing it to take the “natural” course people in charge have chosen. Goodbye for now.

A Brilliant Idea by a Nobel Laureate for Rapidly Responding to Infectious Disease and Especially COVID-19

My colleagues and I answered a call for innovative ideas to fund rapidly responding to emerging infectious disease in a timely and effective way, before COVID-19 was a thought, from The Coalition for Epidemic Preparedness Innovations (CEPI), a global partnership launched in 2017 to develop vaccines to stop future epidemics. We were flatly turned down. CARB-X was launched July 28, 2016, by two divisions of the US Department of Health and Human Services (HHS): the Biomedical Advanced Research and Development Authority (BARDA), which is part of the Office of the Assistant Secretary for Preparedness and Response (ASPR) and the National Institute of Allergy and Infectious Diseases. We had sent in a proposal with a well-known institute to CARB-X in 2017, which was not funded. On 7 January 2020, CARB-X released a press release that CARB-X backs Centauri (a UK biotech company) to advance a new platform that combines antibiotic power with the ability to boost the immune system to fight infections caused by drug-resistant bacteria (this was invented by Dr Kary Mullis, Nobel Laureate and further improved by support from the USAF AFRL Brooks Counterproliferation Team) Centauri therapeutics.https://carb-x.org/carb-x-news/carb-x-backs-centauri-to-advance-a-new-platform-that-combines-antibiotic-power-with-the-ability-to-boost-the-immune-system-to-fight-infections-caused-by-drug-resistant-bacteria/ Combating Antibiotic-Resistant Bacteria Biopharmaceutical Accelerator (CARB-X) is a global non-profit partnership for accelerating antibacterial research to address global rising threat of drug-resistant bacteria. It controls up to US$480 million to invest, 2016-22; CARB-X funds the best science from around the world. The CARB-X portfolio is the world’s largest early development pipeline of new antibiotics, vaccines, rapid diagnostics and other products to prevent, diagnose and treat life-threatening bacterial infections. CARB-X is led by Boston University and funded by US Department of Health and Human Services Biomedical Advanced Research and Development Authority (BARDA), part of the Office of the Assistant Secretary for Preparedness and Response (ASPR), the Wellcome Trust, a global charity based in the UK working to improve health globally, Germany’s Federal Ministry of Education and Research (BMBF), the UK Government’s Global Antimicrobial Resistance Innovation Fund (UK GAMRIF), the Bill & Melinda Gates Foundation, the world’s largest foundation dedicated to improving the quality of life for individuals around the world, and receives in-kind support from National Institute of Allergy and Infectious Diseases (NIAID), part of the US National Institutes of Health (NIH). CARB-X headquarters are at Boston University School of Law. BARDA and the Gates Foundation were appealed to in 2013 and 2012, respectively, for support of the US (our proposal, submitted again to CEPI in October 2019, with Dr Mullis’s collaboration just prior to his passing on August 7, 2019) improvements in chemically programmable immunity using the Nanobe platform, but we were totally ignored by these two. How many times can a good idea be turned down? Until it becomes someone else’s.

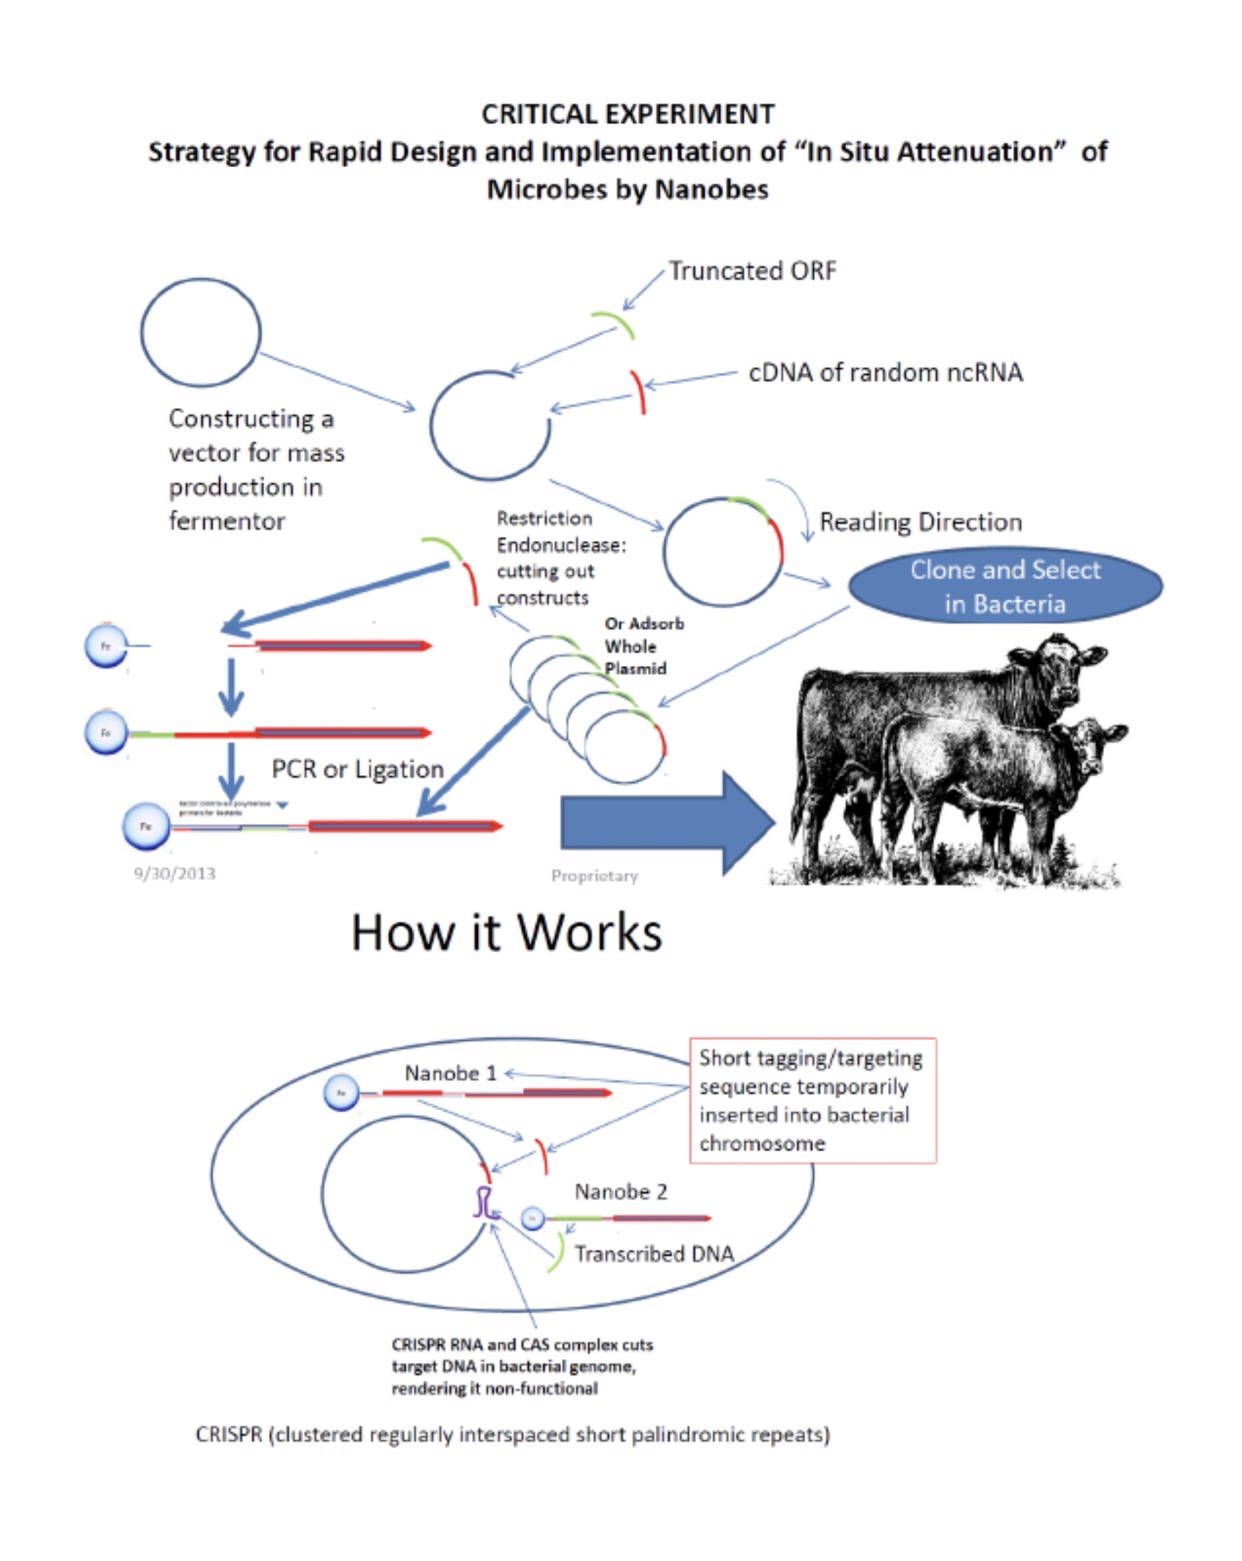
One application: Nanobe technology integrated with CRISPR to genetically neutralize bacterial or viral pathogenic genetic elements, latter if bacterial cell replaced with viral host cell
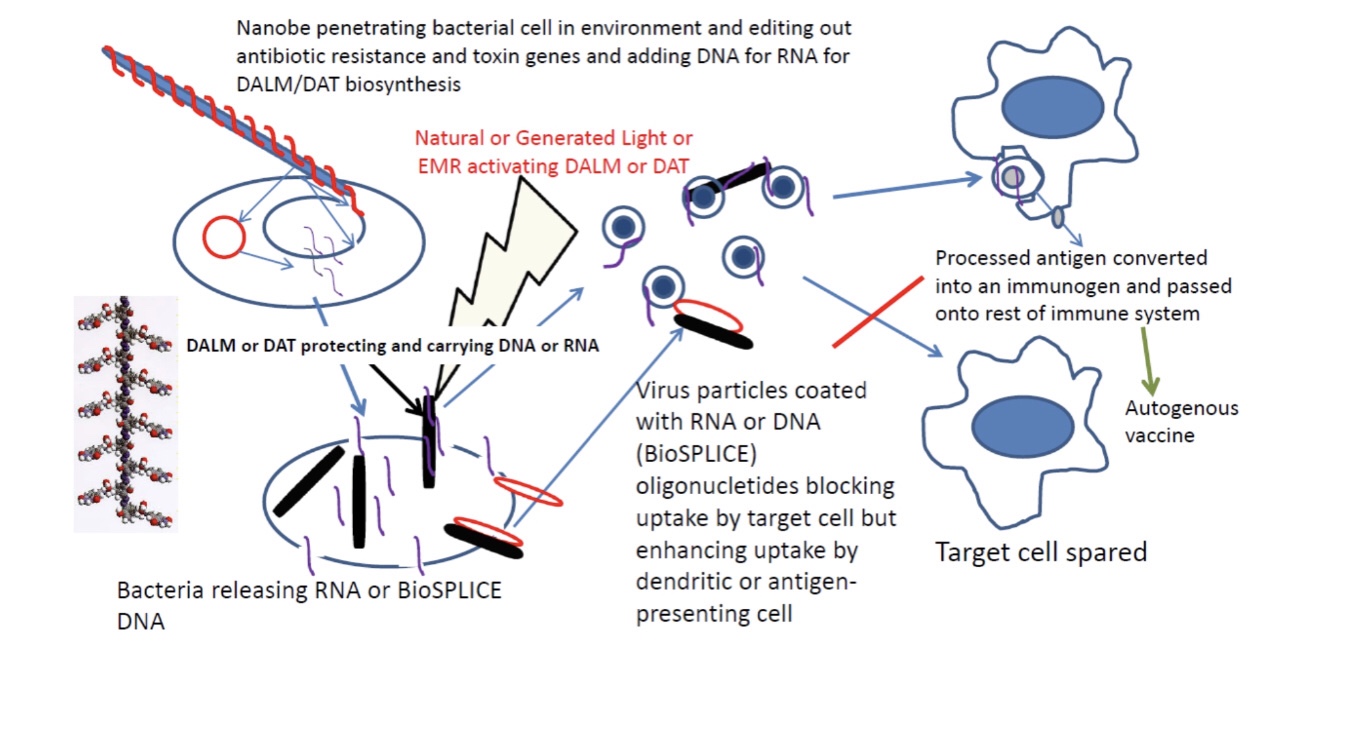
A composite diagram of antibacterial, antiviral, and vaccine-enhancing activity of the biotechnology

Why Antimicrobial Resistance, Vaccination, and COVID-19 are Linked: Motivation for Not Abandoning Brooks Counterproliferation Team Technologies

Ok I keep tying COVID-19 to the research and development done by the USAF AFRL Counterproliferation Team (CPT), described in my books, not for self aggrandizement, but to show how the problems we face now are not much different than those faced then. The solutions approached and then abandoned after the end of the CPT, still have applicability to the current and future like problems. Science does not address “why”, only “how”. The “why” determines motivation, political, monetary, national defense, security, ethical, moral, altruistic or even religious for pursuing the development of a technology. Limited resources leading to shifting priorities led to the demise of the Brooks CPT in 2011. But this blog is here to not only share relevant, timely scientific information on COVID-19 and counter misinformation, but also to revive the potential solutions that evolved over 30 years at Brooks, especially in the last 22 years, and thereafter, which should not be abandoned because they can potentially provide relief for COVID-19 and other infectious diseases to follow.

This post will discuss these relationships without going into great detail, but will allude to previous posts and use excerpts from my books, on relevant material, to lead you to those detailed sources. The prime question is how does an organism resist any injurious, and especially lethal, insult that it has never seen before, whether physical, chemical or biological. This resistance is essential if the organism is to survive long enough in sufficient numbers to genetically select for more permanent and specific resistance. This trait is essential to all organisms, whether hosts, parasites, or pathogens, for survival and to avoid extinction. In my first book Type B Cytochromes: Sensors and Switches, I proffered the idea that this resistance first arose along with the origin of metabolism in prebiotic and primitive life forms. It was linked to surviving the early environment of adverse heat, light and more energetic radiation, and the competition of life forms for energy sources or of mutual predation. The latter probably used chemical mechanisms which mimicked the reducing, oxidizing, and energetic radiation insults of the early environment. Therefore, the prey and predators (at the one cell level) were already prepared for these non-specific insults. The oxidative, reductive, and digestive enzymes (hydrolases) had already developed to support metabolism of environmental energy sources. They could easily do double duty in fighting off competitors and appropriating nutrients from prey. The next step would be to resist or kill parasites and pathogens. First, this was done non-specifically eventually forming the innate immune system; then, adding receptors for recognizing general molecular patterns of prey, parasites and/or pathogens to give these insults direction; next, forming specific immunity to bind and direct some of these destructive metabolic functions specifically to parasites and pathogens, and finally, developing cellular mediated suppression balanced with specific adaptive humoral and cellular immunity to reduce collateral damage and resolve the attack. The susceptibility to these redox enzymes and their use for cellular defense reflects the different niches and locations of the pathogens and parasites in respect to the level of the corresponding environmental radiation and inorganic chemicals that they were historically exposed to. Also, the reactions used in defense were confined to protected compartments in the defending host cells. This notional scenario has a modern example in HIV.

OXIDATIVE STRESS AND THE HUMAN IMMUNODEFICIENCY VIRUS: Another direct effect of activation of an extranuclear receptor or sensor in the plasma membranes of cells is seen in the growth of mammalian cells and expression of retrovirus. The upregulation of human immunodeficiency virus has been reported to be effected by UVC (200 to 280 nm wavelength radiation). The level of upregulation was 50-to 150-fold baseline. Direct sunlight activated this expression 12-fold. UVB (280–315 nm) also upregulated HIV. Transgenic mice carrying HIV with a beta-galactosidase or firefly luciferase reporter gene showed upregulation of HIV after exposure to either UVB or UVA (315–400 nm) light combined with the photosensitizer psoralen. Sunlight, which contains both UVA and UVB, worked without photosensitization but required 7 hours as opposed to 2 hours with psoralen added. The Langerhans cells of the skin, which mature into antigen-presenting dendritic cells, which can efficiently infect CD4 + T lymphocytes with HIV, could potentially harbor virus that would be activated by UV light. Again, the conditions for HIV activation by UV radiation strongly resemble those necessary for the induction of heme oxygenase. Either this is a happenstance of multiple irrelevant gene activation or a link to a particular sensor (redox or heme related). Evidence for the existence of a plasma membrane extranuclear sensor has been provided by data on the UV activation of the broadly acting transcription factor, NF-kappaB. The UV activation of binding of this factor to DNA has been shown without nuclear material being present. Furthermore, the same factor is upregulated by exposure of cells to nitric oxide and other oxidants. Its activation is inhibited in part by antioxidants at the level of the GTP-binding protein Ha-Ras. NF-kappaB is the endogenous transcription factor responsible for activating HIV expression. Therefore, oxidants like NO or UV radiation, which activate NF-kappaB, could activate HIV expression in vivo. Ionizing radiation (60Co gamma irradiation for 10 min) activates NO synthase. Therefore, oxidations initiated by ionizing irradiation are expected to upregulate HIV expression. Gamma-interferon, which activates oxidative activity of macrophages, should also upregulate HIV expression. Oxidative processes and UV radiation can also act indirectly on the upregulation of cell growth and latent retrovirus expression. Exposure to 60 min of 20 J/ m2 of 254-nm UV enhanced NF-kappaB binding activity fivefold by 60 min, with the activity continuing to rise to tenfold by 8 hours. Phorbol ester-treated cells had the same NF-kappaB activity response. Conditioned medium from irradiated cells also transferred this stimulatory activity. These effects were not associated with cell proliferation. CD + 4 T cells also responded to these conditions by upregulating HIV-1. The UV-induced or activated factor has been detected in several other cell types, including normal human primary skin fibroblasts, skin fibroblasts from xeroderma pigmentosum patients, and the human hepatoma cell line HepG2. Interleukin-2 (IL-2) production by CD + 4 T lymphocytes is also controlled by NF-kappaB. Therefore, agents that stimulate NF-kappaB activation can act as adjuvants to immune stimulants.—-Type-B Cytochromes: Sensors and Switches by J.L. Kiel
https://a.co/bKOgtos.

The latter is a link between these non-specific redox effects and the adaptive immune system. HIV has adapted to replicate after the oxidative innate response triggers the adaptive response and feedback down regulation of the oxidative activities. This leads to death of CD4 lymphocytes with each round of immune response to a wide variety of infectious agents. The collateral damage to other normal cells causes even more pathology, including carcinogenesis. This relentless destructive process also prevents the development of a vaccine by standard approaches.

The mutations that result from the oxidative sublethal damage to DNA might be assumed to lead to evolving more repair processes or programmed cell death to self-eliminate irreparable pathologically damaged cells. However, higher immune systems developed to mimic such expected hypervariability in certain genes which produce proteins that bind to the target biological material which triggered the oxidative response in the first place. This binding increases the effective directed killing of oxidatively active cells or those that kill by other means and disposal of the inciting agents leading to the quelling of the non-specific oxidative killing. Therefore, these responding cells are selected to produce more of the specific binding molecules—-immunoglobulins. These are diversified into classes or isotypes – IgA, IgD, IgE, IgG and IgM. These are further diversified by recombining hypervariably mutated regions with more constant regions both for antibody and receptors on T and B cells. The latter produce antibody. The germline theory holds that there is a separate gene for each different immunoglobulin chain and that the antibody repertoire is largely inherited. The alternate theory is the somatic diversification theory that purports that the observed repertoire is generated from a limited number of inherited V-region sequences that undergo mutation within B cells during the host’s development. Cloning of the immunoglobulin genes has yielded data that indicate the antibody diversity is generated by DNA rearrangements during B-cell development. DNA sequences encoding a variable (V) region in each immunoglobulin gene locus are selected from a relatively small group of inherited gene sequences. Diversity is further enhanced by somatic hypermutation in mature activated B cells. Both germline inheritance and individual host somatic mutation lead to the diversity of immunoglobulin and T and B cell receptors. Therefore, the diversity is generated in anticipation of encountering various targets but not after the encounter; except that those clones that are selected by binding are expanded, replicated, after the encounter with the pathogen or parasite. Again, the highly developed mammalian and human immune systems re-create the highly energetic, oxidative primitive environment of that early environment and then quench it with the adaptive immune system. Is this process restricted to higher organisms and manipulated in defense by viruses and certain other highly pathogenic microbes ? Is there evidence, that resistance to antibiotics already existed prior to their use in animals and humans and were only selected for and amplified by the pressure of antibiotic use? Much has been said and many accusations made about the source of the antibiotic resistance in microbes in the environment, in addition to those which develop because viral infections and non-microbial conditions are treated in the clinic with antibiotics which have no effect except on resident bacteria which are encouraged to develop resistance and pass it on. Growth stimulating use of antibiotics in agriculture, and herd treatment of infectious disease in livestock have been cited as the principal source of antibiotic resistant bacteria. However, there is strong data which support that such resistance in bacteria infected humans and animals develops independently in most cases and is not transferred between them (Mather et al., Science 341, 1514; 2013). In addition to these sources of resistance, the fact that most of the antibiotics we have today come from fungi or fungi-like bacteria which reside in soil and natural water sources should make us expect the development of resistant microbes in those environments too, even before antibiotics were introduced in the 1940’ s by human intervention (Allen et al. , Nature Reviews Microbiology, published online 1 March 2010; doi: 10.1038/ nrmicro2312) . We shouldn’t be surprised that some of these types of organisms are the most resistant, such as Pseudomonas aeruginosa, Aeromonas hydrophila, Salmonella typhimurium and other Salmonella species, Klebsiella pneumoniae, Bacillus species other than Bacillus anthracis, Enterococci and E. coli, released into the environment and maintained in water sources from all sorts of wild and domestic animals through their feces and re-entering them by being in such environments, and Mycobacterium avium and other mycobacteria which are primarily soil organisms. Many of these, including Staph aureus and other Staph species, are opportunistic pathogens, not totally dependent on a diseased host to propagate, but quite capable of reproducing in the environment without any host at all.

How do other pathogens combat these immune responses in the arms race with host cells and tissues? How do bacteria also anticipate antibiotics and secure the time to mutate to become permanently resistant? Processes in these lower organisms, like more complex higher organisms, had to anticipate injurious insults and prepare broad countermeasures to allow time to select more specific, effective countermeasures by mutation and natural selection. As discussed in an earlier post, this was first seen with large populations of bacteria exposed to physical insults like ionizing radiation at levels known to kill the microbes. If the numbers were high enough, a tail of survival even as the dose was increased still survived and approached zero survival asymptotically. When the survivors in the surviving tail of the population were re-cultured and exposed to the same range of insult, resistant microbes in the population were not increased, selected for except after many passages. How was this possible ? How did this phenomenon allow for eventual selection of resistant mutants ? Likewise for bacteria, viruses or other microbes, how do the microbes gain the opportunity and enough time for the transfer of antibiotic resistance or mutation for antiviral or other chemotherapy to occur in the midst of antimicrobial treatment, when, perhaps, only a small percentage of the population being treated is, in fact, resistant and contains the transferable elements? Does the mechanism for development of resistance to an antimicrobial already exist before the microbe sees the antimicrobials? There must be enough time and contact opportunity for this to occur before the susceptible microbes are killed. The answer resides in persisters. Persisters are environmentally induced phenocopies of phenotypes determined by genetic changes. In this case, specifically, I am referring to one which mimics an antibiotic or antimicrobial resistant mutant. They are particularly effective against antibiotics or antimicrobials which require replication or a metabolic activity like the formation of cell wall material (such as penicillin and cephalosporins do) to be effective. They are generally slow growing microbes which maintain a minimal metabolic rate to survive, or in the case of viruses latent non -replicating, hidden forms in sequestered, privileged immune sites. When these are present, they survive in the antibiotic environment, especially if a low dose or one which is insufficiently toxic for the microbe is maintained. With the mutant or one bearing an extrachromosomal element such as a plasmid which conveys antibiotic resistance is in the same environment and has the machinery to share this genetic material, the antibiotic resistance will spread quickly. The exponential decay curve plot shows how this persistence time can be very long and most effective for providing opportunities for genetic transfer. If the microbial population is very large, then the tail on the graph toward the right, where the decay rate, or in this case the rate of kill of the microbes with the antibiotic approaches zero, large enough numbers are maintained “under the curve” for such a transfer to be inevitable. In antibiotic treatments in an infected host, the numbers are dropped to zero because the immune system kicks in and finishes off the remaining microbes. Some bacteria like anthrax bacteria can remain dormant as spores in macrophages and emerge later after antibiotic levels have declined and even produce inflammatory mediators like nitric oxide which feedback on the immune system to shutdown oxidative inflammation and encourage adaptive immunosuppression.

An anthrax bacteria persister
Persister genotype (mutant) phenotype

SARS-CoV-2, as discussed in earlier posts, suppresses interferon production and early innate immunity, resulting in widespread tissue and organ infection then triggering massive adaptive immunity directed inflammation resulting in septic shock, multiple organ failure. Therefore, severe COVID-19 and possibly death, results from a widely distributed “local” non-specific oxidative response to a silent wide distribution of a great deal of virus in many cells, in many tissues and organs at once. Antiviral treatment must be applied early to prevent this widespread silent distribution of virus, and any vaccine must not enhance this type of innate immune response, but encourage the development of adaptive cellular and humoral immunity which prevents it.

How did Brooks CPT technology evolve to address these problems? Actually I have already told you in my books and previous posts. The above meandering was to explain how when all the responses to a pathogen are brought together in a balanced way, damage, both direct and collateral, is avoided, but when one dominates the other, morbidity and mortality predominate. Now, in brief, I will tell you why and how we proceeded to address the inadequacy of each apparent solution, step, toward this balance. For 7 years, we searched for a synthetic biomolecular polymer which could specifically absorb a wide range of microwave to radio frequencies and report the results as visible light. This was achieved, and we found out that the activated states formed could form free radicals which caused material damage and even could kill very resistant anthrax spores rapidly. We then found that the anthrax bacteria could biosynthesize the polymer and, if not activated with electromagnetic radiation, it could accelerate bacterial growth before damaging the bacteria. This proved most useful for rapidly identifying anthrax in the field then killing it. Whether the polymer was made endogenously or applied externally, when primed with sublethal concentrations of hydrogen peroxide and sodium carbonate and activated with otherwise sublethal microwaves, the anthrax, vegetative and spores, were effectively killed. This was mimicked by the application of very high temperatures or by cold plasma gas with very high electron temperatures. This mechanism cannot be overcome by bacterial resistance because the localized temperatures exceed the covalent binding energies of all biological molecules by orders of magnitude; they are literally burned up by the ionization. However, because the effect is so localized and so brief, it yields very little collateral damage. That was both a curse and a blessing because it decreased unwanted material damage and biological injury but limited the environmental decontamination potential. This problem was overcome by coating metallic nanoparticles with the polymer. The transition metallic nanoparticles provided spontaneous surface redox reactions that primed the polymer for microwave interactions without the need for hydrogen peroxide and sodium carbonate, but only a nano coating of water. These particles at a very small total mass could be spread over large environmental volumes or surface areas. This property not only greatly enhanced decontamination of surfaces but also provided the potential of air decontamination. The formation of nano plasma confined to the surface of the particles continued to reduce collateral damage. Although previous experiments had shown the fibrous form of the polymer was unable to penetrate cell membranes (unless microwave-activated to burn through), this all changed when it was placed on spherical metallic nanoparticles or biosynthesized into a similar, but non-metallic, physical form. Because it had been known that the polymer co-purified with DNA when biosynthesized in bacteria, it was expected to carry cellular DNA with it. When we started selecting nucleic acid aptamers against potential biological warfare agents for collection and identification, we decided to incorporate them into plasmids for mass biosynthesis. When the plasmids also carried the nitrate reductase gene, the bacteria could make the aptamers and the polymer simultaneously. Because we selected for double-stranded DNA aptamers to incorporate into the plasmids, we reasoned that the polymer nanoparticles, containing aptamers that directed specific pathogen binding, could achieve detection, identification, and killing, all this capability made in a one pot batch. This was demonstrably true for targeting anthrax spores. But much to our surprise, this led to the next step discovery. These particles could transfer the complete particle synthesizing capability to naive bacteria, even to different species, including anthrax. It could even transfer traceable DNA to animal and human cells. The eukaryotic cells did not make DNA polymer nanoparticles but they could make ones containing RNA (even perhaps mRNA). Attempts to make therapeutic particles went as far as making anti-anthrax aptamers modified to protect them from nucleases in vivo that could neutralize the pathogenicity of the anthrax toxin in vitro and in vivo (in mice), the latter by inhalation to treat anthrax generated by spore inhalation. The system was also tested against virus in vitro, vaccinia virus, with DNA in plasmids that transcribed into iRNA (interference) to block its replication. When the nitrate reductase gene was incorporated in the plasmids in addition to the iRNA generating DNA, it inhibited the virus more than the iRNA. At this point, our work ended and we never completed the in vivo antimicrobial polymer nucleic acid nanoparticles, unfinished business, so frustrating.

Another Option for a Nucleic Acid COVID-19 Vaccine: DNA Vaccines: Hidden and Forgotten Methods for Delivery: Lost in the Mix

Nov 16, 2020, 07:00 ET, it was announced that INOVIO received approval from the U.S. Food & Drug Administration (FDA) to proceed with Phase 2 of its Phase 2/3 clinical trial for INO-4800, its COVID-19 vaccine candidate. INO-4800 is the only nucleic-acid based vaccine that is stable at room temperature for more than a year and does not need to be frozen in transport, an important factor for implementing mass immunizations. INOVIO’s DNA vaccine plasmid is delivered directly into cells intramuscularly or intradermally using INOVIO’s proprietary hand-held device called CELLECTRA®. The CELLECTRA device uses a brief electrical pulse to reversibly open small pores in cells to allow the plasmids to enter, overcoming a key limitation of other DNA vaccines and mRNA vaccines. Once inside cells, the DNA plasmids enable the cell to produce the targeted antigen. The antigen triggers the normal T cell and antibody-mediated immune responses. The CELLECTRA device ensures that the DNA plasmids are efficiently delivered directly into the body’s cells to drive the immune response. INOVIO’s DNA vaccine does not interfere with or change in any way an individual’s own DNA. The advantages of INOVIO’s DNA vaccine platform are how fast it was designed and manufactured; its stability, not requiring freezing for storage and transport; and the robust immune response, safety profile, and tolerability evident in clinical trials. The CELLECTRA® electroporation device developed by Inovio Pharmaceuticals, Inc., is currently being assessed in clinical studies for both prophylactic and therapeutic applications.

This device delivers square-wave electric pulses by applying an adaptive electric field based on constant current, rather than constant voltage. This system measures electrical parameters and adjusts appropriately for changes in tissue resistance in realtime to avoid tissue damage and diminished DNA cell entry. The device has been evaluated in animal models, including mice, pigs, and rhesus macaques, and demonstrated acceptable immune responses.

DNA vaccines have been criticized in the past because of the possible off-target effects in expression of protein, integration of foreign DNA into the host genome and difficulties in delivery to the right target cells. As noted above INOVIO has provided evidence that they have overcome these limitations by plasmid design and a proprietary electroporation device. The concern about plasmid in comparison to mRNA vaccines is that they must enter the nucleus to be converted into mRNA before being translated into protein in the ribosomes of the cytoplasm. mRNA vaccines do not require entry into the nucleus before this last step. I have spent a lot of time providing accounts and data of the Brooks Counterproliferation Team’s work on these problems for different military applications in previous posts. It is ironic that INOVIO has received a significant level of funding from the Department of Defense independent of our work: On June 23, 2020, INOVIO received a $71 million contract from the U.S. Department of Defense to scale up its manufacture of its CELLECTRA® 3PSP Smart Device and procurement of CELLECTRA® 2000 for COVID-19 DNA Vaccine delivery https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3906411/pdf/hvi-9-2246.pdf.

Alex Careaga @alexcareaga
The starting material, 3-amino-L-tyrosine (3AT) is an amino acid analogue of L-DOPA, the latter which can be converted into melanin. The 3AT, through substitution and elimination, yields the following
polymer (trivial name: diazoluminomelanin: DALM).

Our work began with efforts to synthesize a microwave and radio frequency electromagnetic radiation interacting polymer starting in 1981. We succeeded (1 March 1988) in making one from the amino acid 3-amino-L-tyrosine which through diazotization ended up with the following structure:

This polymer demonstrates a number of interesting and very applicable physical and chemical properties. It is thermochemiluminescent while oxidizing, binds to DNA without damaging it functionally, and further interacts instantly with pulsed direct current electric fields, and those of pulsed radio frequency and microwave radiation. The classical explanation of its behavior is as an inductor, that it is a passive two-terminal electrical component that stores energy in a magnetic field when electric current flows through it. An inductor consists of an insulated wire wound into a coil around a core. When the current flowing through an inductor changes, the time-varying magnetic field induces an electromotive force (e.m.f.) (voltage) in the conductor, described by Faraday’s law of induction. According to Lenz’s law, the induced voltage has a polarity (direction) which opposes the change in current that created it. As a result, inductors oppose any changes in current through them. The coiled ground state structure of DALM may be responsible for its behaving as a molecular inductor. The discharge of luminescence and/or thermalization are related to the release and conversion of this stored energy.

The build up of energy into dark states leading to high E fields may facilitate electroporation. During electroporation, the lipid molecules simply shift position, opening up a pore which acts as a water- filled conduction pathway through the bilayer. Electroporation is a dynamic phenomenon which depends on the local transmembrane voltage at each point on the cell membrane. For a given pulse duration and shape, a specific transmembrane voltage threshold exists for the electroporation phenomenon (from 0.5 V to 1 V) to occur, an electric field magnitude threshold for electroporation.
Ribbon-like structure of DALM with sharp edges and angular high aspect ratio ends unlike amorphous globular natural melanin
The conversion to sound allows for the possibility of transporting DNA into cells by sonoporation. Sonoporation has already demonstrated potential utility in gene transfer https://www.nature.com/articles/s41598-018-22056-8.pdf.

The next step was to try to make DALM from feedstock chemicals fed to bacteria that have inducible nitrate reductase. When this process was not totally satisfactory, genetic modification with plasmids delivered by electroporation or calcium phosphate was tried and succeeded in enhancing the production of DALM. This even worked with mammalian and human cells harboring nitric oxide producing enzymes (nitric oxide synthase, NOS) which could integrate with a component of the barley plant nitrate reductase to enhance both their activities simultaneously.

Nitrite production by electroporatically transfected cells measured by Griess Reagent absorption of 546 nm visible light.
Human HeLa (top) cells (HeLa NR1 ATCC ® CRL-13011™ Homo sapiens cervix adenocarcino: https://www.atcc.org/Products/All/CRL-13011.aspx) and E. coli bacteria producing nanoparticles (white particles) after transfection and transformation, respectively, with the appropriate plasmid vectors of barley nitrate reductase components and fed feedstock for DALM biosynthesis.
Plasmid used in HeLa cells (HeLaNR1) to make them biosynthsize DALM and DALM nanoparticles. The presence of SV40 genes allows for integration into the host genome and what has made ATCC concerned about licensing the cell line’s use and that it be handled in a BSL-2—because of the potential of transfer of “infectious” viral oncogenic material.

Thermochemiluminescence of oxidizing biosynthetic DALM made by transfected HeLaNR1 cells compared to controls.
The plasmid used in E. Coli to produce DALM nanoparticle DNA transformation vectors.
Schematics of nucleic acid (plasmids and mRNA) coating and transfer by biosynthetic DALM.
Overall design of scheme of making and delivering DALM nanoparticle vectors of expressible DNA as for vaccines.
HeLa P6 cells showing fluorescence tracking of transfecting nanoparticles to nucleus
Showing tracing fluorescent Nanobes (DALM nanoparticles) carrying transfecting DNA and resulting PCR demonstrating presence of vectored DNA in human kidney cells (HK2). These results show that DALM vectors do not require an electric field to be taken up into human cells.
Freeze-dried DALM nanoparticle vectors which were still functional after 4+ years storage at room temperature and ambient light in the lab.
These commercially available nanosprayers could facilitate the transdermal transfer of DALM nanoparticle vectors for clinical use as for DNA plasmid vaccination; similar devices could be used for inoculation by inhalation.

Plasmids transferred to target cells with DALM nanoparticle vectors have demonstrated desired functional transfer such as antibiotic resistance for clonal selection, antimicrobial activity, and DALM nanoparticle biosynthetic capability, but also the less desirable transfer and off target effects of genome integration in mammalian and human cells (expected based on plasmid constructs used), and in bacteria, not only the clonal selection antibiotic resistance, but also the off target effects of bacteriophage resistance and hemolytic activity in a pathogen (Bacillus anthracis, anthrax). The DALM nanoparticle vector has demonstrated its broad utility as a potential plasmid DNA vaccine vector and also its ability to be manufactured by microbes’ making biosynthetic complete DALM, nanoparticle, plasmid DNA vectors for genetic transfer.

Realizing COVID Testing is Almost Valueless After Three Days: The Damage Already Done: Lesson Already Learned in Biodefense by the Military

It has become abundantly clear that testing for SARS-CoV-2, especially in the United States, is inadequate in amount and in timing. The military struggled with this problem years ago in the dilemma of “test to treat” versus “test to warn” in designing its detectors and diagnostics for biological warfare agents. The first was attainable but many times was too late: the phenomenon of “dead man walking”, the casualty alive but nearly 100% likely to die. The second was nearly impossible to achieve, with its instant diagnostics full of false negatives, and with no adequate immediate life-saving treatments to make it of value. This was the landscape we entered in 1989. We spent the next 22 years approaching the solutions asymptotically but our efforts were ended before completion because of change in priorities. Now we face the same problem under the COVID-19 crisis. To illustrate the severity of the challenge, we need to look no further than the number one biologic warfare/bioterrorism agent, anthrax. The following data illustrating this point and many of my previous posts, references and books have continuously emphasized these often ignored and postponed problems.

These graphs illustrate that antibiotics and other antimicrobial treatments must be applied early, at the appropriate doses, and for extended periods in the face of a highly lethal infection if they are going to have a significant effect or do more than delay morbidity and mortality.
Another set of graphs that show inhalation or a lethal dose of anthrax spores has a critical period (2-4 days) in which treatment must be applied or it will lose all effectiveness; even with much less lethal COVID, the same principle of critical time window for treatment must be accomplished in order to avoid severe morbidity and mortality in individuals destined for those outcomes.
These plots show how extreme the outcomes can be for a highly lethal infection like anthrax even for essentially the same treatments based on different protocols of dose and timing as well as combinations of treatment; even in a much less lethal infection as COVID, these types of responses become evident in the history of more severe infections, making prognosis very difficult for the apparently same treatments in different patients.
The above circular chamber was the experimental test device to demonstrate the magnetic capture of biological agents on paramagnetic nanoparticles. The illustration below the chamber is of the fluorescent detector for the microfluidic chamber.
This prototype proof-of-concept device was replaced by the following commercial device with modifications.
The portable field device, built by Charles River Labs, flown and tested by NASA aboard the International Space Station, that was modified for biodefense. The graphs show the fluorescence detection by the device using a protein, thrombin, and a small molecule (nucleic acid base, nucleoside, adenosine) as targets representing pathogens and toxins.
The multichannel microfluidics chamber and electronics of the CRL device. It was totally self-contained so that once the sample was injected into the channels, the biological agent(s) could be captured on the paramagnetic nanoparticles, detected by turned-on fluorescence, and kept isolated, alive and safe in the chambers to bring back to the lab for further analysis and even culture. The released artificial DNA or the agent’s released DNA or RNA (destructive analysis) could be amplified in a downstream chamber by isothermal amplification or PCR for more specific orthogonal identification. This process could even be used with random double-stranded DNA aptamers with primers to select and amplify selected aptamers to unknown agents to take back to the lab for further characterization and scale-up manufacture.
These pictures show the near instantaneous fluorescent detection of anthrax spores by nanoparticle-aptamer-fluorescent dequenching compared to a field immunochromatographic lateral flow “home test”.
As illustrated above, the detecting and identifying nanoparticles can be translated into biological agent killing particles for the environment: in the air or on surfaces, or if bound to biocompatible, non-toxic particles such as biosynthetic DALM or polymer made from the amino acid aminotyrosine, can be used inside the infected host, even self-administered by inhalation. They could even be used to genetically transform the biological pathogens into agents more vulnerable to other antibiotics and antimicrobials.

In conclusion, we now face a global pandemic and an assault on the USA, which if it were a strategic intentional biological warfare attack would have achieved its military objectives of mass casualties, overwhelming the medical and public health systems, economic damage (industrial capacity to wage war), causing panic, chaos, and internal strife, and compromised military readiness. For the sake of other priorities, we neglected our preparedness and abandoned our technological edge and advantage. The result 13,383,370 cases and 276,235 deaths in US of COVID as of this posting.

Why a Viral Protein is Critical to Human Fetal Development: Syncytin I is Not a Cause of Concern for Autoimmunity or Sterility from a SARS-CoV-2 Vaccine: Twisting the Truth: Still Raising its Ugly Head

I have found it necessary to re-post this post. The only way vaccines have affected reproduction is when live attenuated vaccines are given to pregnant hosts, infect the fetus and cause defects or abortion—the mRNA vaccines in particular are not of this class and even the aforementioned effects do not result in sterility and should not be confused with it.

A recent popular article has suggested, that because the SARS-CoV-2 spike (fusion) protein has a homologous polypeptide to Syncytin 1, a protein that forms the syncytium of cells by fusion binding the fetus to the uterus through the placenta, the vaccines against the spike protein would develop antibodies against the placenta and cause sterility, but the data does not support this https://edwardnirenberg.medium.com/are-covid-19-vaccines-going-to-cause-infertility-939bbdb62b64. The fusogen proteins that allow enveloped viruses to fuse with their target host cells are related but not necessarily identical to the placenta protein. In fact, Syncytin 1 and 2 were originally viral proteins and are necessary to the development of placentas in mammals. This was accomplished by infection with a Type D retrovirus which became integrated into the mammalian and human genomes. HERV–W genome integrated into its host’s germ-line around 63 million years ago, spread into Old and New World monkeys and then evolved independently. The viral genes were incorporated into the germ cells and, therefore, for all subsequent generations. This endogenous retrovirus, HERV-W, is the source of Syncytin I. The env gene from HERV-W produced a functional class I fusion protein capable of merging cells into a syncytium. Such syncytia are at the placental interface between the embryo and mother; preferential expression of HERV-W occurs in embryo cells that become part of the placental interface. This virally derived fusion protein is syncytin, later called syncytin-1; a second such protein from HERV-FRD, is called syncytin-2.

“These ubiquitous endogenous retroviruses are permanently transmitted in germ cell genomes and almost all have lost their ability to replicate outside of their genome-integrated DNA and to infect other cells horizontally as complete infectious virions. They are associated with resistance to other exogenous retroviruses, the process of xenotropism, and with placental development in mammals. Endogenous beta retroviruses (enJSRVs) are present in the genomes of sheep and goats. The enJSRVs are highly related to Jaagsiekte Sheep Retrovirus (JSRV) and the Enzootic Nasal Tumor Virus (ENTV), which cause naturally occurring carcinomas of the respiratory tract of sheep. The enJSRV blocks exogenous JSRV replication by a novel two-step interference mechanism acting both early and late during the virus replication cycle. The only retrovirus sequences that have been added to the human genome since humans became a separate species from their common primate ancestor are members of the Human Mouse Mammary Tumor Virus-like 2 (HML-2) group of the beta retrovirus-like viruses. This human endogenous retrovirus is HERV-K whose elements are integrated in all extant human genomes”— The Black Dragon Trilogy by JOHNATHAN KIEL
https://a.co/8OGjRRc

Mammals and humans have become immunotolerant to these viral placental proteins. Although it is possible for there to be cross reactivity between microbial antigens and self, the evolutionary adaptation to this essential viral appropriated protein has minimized the likelihood of this type of autoimmunity. Fusogenic proteins are so pervasive in enveloped viruses, that if this kind of autoimmunity were likely, we would see sterility with many types of viral infection and their developed vaccines. Normal births have occurred and been reported from SARS-CoV-2 infected mothers. Example viruses producing fusogens, including viral class I fusogens, are major human pathogens, including influenza A, Lassa virus, SARS-CoV, Ebola, human parainfluenza virus-3, HIV-1, and human T-lymphotropic virus-1. Class II fusogens come from Dengue fever virus, West Nile virus, Zika virus, and tick-borne encephalitis virus https://www.cell.com/current-biology/pdf/S0960-9822(20)30668-0.pdf. When viruses such as rubella and Zika cause birth defects it is because of the wild viral infection not autoimmunity to a host antigen https://www.ncbi.nlm.nih.gov/books/NBK507879/ and https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6140214/. Therefore, this extrapolation and extension of a evolutionary relationship between host and ancient viruses have not led to sterility but rather advanced fetal development.

The electron micrographs that show stunted viral development of the Viper Plague Virus, a Type D retrovirus from West Africa, which is blocked by endogenous retroviruses (HERV-K and human mouse mammary tumor virus-like 2 (HML-2) group) in mice and humans—some good viruses

Perhaps the most remarkable interaction of endogenous retrovirus is with HIV (Human Immunodeficiency Virus):

“Recently, it has been shown that the expression of HERV-K proteins suppresses HIV replication, perhaps through tuftsin, an inflammatory macrophage cytokine. Decline in tuftsin and increased expression of HERV-K is associated with advancing AIDS. Activation of HERV-K expression has correlated with the level of HIV-1 production. Studies of autoimmune neurological demyelinating disease (experimental autoimmune encephalomyelitis (EAE)) in rodents indicates that tuftsin administration upregulates immunosuppressive Helper-2 T cell (Th2) cytokine transcription factor and that tuftsin-mediated microglial cell activation results in shifting microglia to an anti-inflammatory phenotype. In return, the T cell phenotype is shifted towards immunoprotection after exposure to tuftsin-treated activated microglia, that is, downregulation of pro-inflammatory Th1 responses triggered in conjunction with upregulation of Th2-specific responses and expansion of immunosuppressive regulatory T cell clones. Macrophages with activated HERV-K expression were more resistant to HIV infection, perhaps in part by its Gag protein being expressed and interfering with the assembly of the HIV virions, and cells expressing HERV-K and infected with HIV were more susceptible to destruction by cellular immunity. Infection of CD4 + T cells with HIV-1 was shown to result in transcription of the HML-2 lineage of HERV-K [HERV-K( HML-2)] and to express the Gag and Env proteins of this virus. HERV-K( HML-2)–specific CD8 + T cells obtained from HIV-1–infected human subjects responded to HIV-1–infected cells in a Viral infectivity factor (Vif)-dependent manner in vitro. HERV-K( HML-2)–specific CD8 + T cells (cytotoxic T cells) eliminated cells infected with globally diverse HIV-1, HIV-2, and SIV isolates in vitro. A second T cell response that exhibited cross-reactivity between homologous HIV-1-Pol and HERV-K( HML-2)-Pol has raised the possibility that similarities between HIV-1 and HERV-K play a role in forming, triggering, and perhaps enhancing, the T cell response to HIV-1. There is even some suspicion, because of the association with HERV-K expression with certain tumor cell lines, that its expression can lead to cancer triggered by HIV infection as was perhaps my brother’s brain lymphosarcoma. HERV-K is both protective, initially through triggering the innate immune system and later specific T cell cytotoxicity, and detrimental by perhaps triggering the formation of cancer. The dilemma with HERV-K and the human immune system is that the initial innate response producing reactive oxygen species could protect against both HERV-K and HIV, simultaneously, but the switch to the inadequate nitric oxide response in human macrophages encourages the replication and release of HIV to infect other recruited and susceptibly activated macrophages to carry the HIV to lymphoid tissue. Evolutionarily, HERV-K’s advantages have outweighed its disadvantages and has led to resistance to such coming plagues as that could result from Viper Plague Virus, at least for now.”— The Black Dragon Trilogy by JOHNATHAN KIEL
https://a.co/57tGvuL

Last Two Most Important Achievements of the Brooks Counterproliferation Team and BioAnalysis Consulting LLC

Chemically Programmable Immunity using prior vaccine immunization against new pathogens
Using synthetic nanostructure vectors to replace viruses for delivering plasmids, genes and nucleic acid vaccines
Last patent of last method to facilitate selection of synthetic nucleic acids for the vector system described in the previous patent