Although One Health has come a long way since Rudolf Virchow, MD, in the 1800’s stated “Between animal and human medicine there are no dividing lines—nor should there be. The object is different but the experience obtained constitutes the basis of all medicine,” and coined the term “zoonosis” to indicate an infectious disease that is passed between humans and animals, it is still having difficulty in connecting in the transition between animal and human infectious disease, the “No Man’s Land”, until the crossover occurs. In 1947, James H. Steele, DVM, MPH, founded the Veterinary Public Health Division at CDC. He became the Veterinary Father of One Health. His lead produced nearly 70 years of Annual James Steele Conferences on Diseases in Nature Transmissible to Man (DIN) which have pursued the One Health concept in infectious disease. The COVID-19 experience and the apparent surprises it has given to the medical community and the isolation of the veterinary profession or at least its sideline position (my opinion) indicates we have a long way to go. I worked for 22 years in the USAF AFRL in the no man’s land between outbreaks of zoonotic diseases in the little supported, some consider impossible, field of attribution of both natural and nefarious sources of infectious disease. However CDC and other organizations are making active efforts spurred by COVID-19 to re-invigorate the One Health Effort. https://www.cdc.gov/onehealth/basics/history/index.html
“In 1885, Louis Pasteur administered the first rabies vaccine in a person, marking an important turning point in public health. Today, zoonotic diseases continue to be one of the biggest threats at the human-animal-environment interface. A One Health approach, with involvement from experts across sectors, is key to preventing and controlling zoonotic diseases that can have global consequences.
60% of existing infectious diseases are zoonotic
At least 70% of emerging infectious diseases come from animals (Ebola, HIV, influenza, and COVID-19)
80% of agents with potential bioterror use are zoonotic.”
@CDC_NCEZID and #WorldZoonosesDay on social media.
From: John Kiel Sent: Tuesday, February 06, 2007 8:41 PM
Cc: Kiel, Johnathan L Civ AFRL/HEPC Subject: Re: Pulse Article – Texas Tech University Health Sciences Center
Dr. Kiel,
I hope you enjoyed the previous issue of Pulse I mailed last week. I am looking forward to working with you!
Below you will find several questions regarding you, your job and how you arrived where you are in your life today. Please feel free to add any additional information you feel would be helpful. Once I have your answers if I don’t need further information I will draft the article and send it to you for your review. Our first draft deadline is February 19th.
Thank you again for your help!
Where are you from? I was born in Houston, TX and grew up there, although my Mother is British and I spent some summers as a child with my Grandparents in St Helens outside of Liverpool UK (UK is kind of my second home).
What other degrees do you hold? BS (Texas A&M, veterinary science, 1973); DVM (Texas A&M School of Veterinary Medicine, veterinary medicine, 1974); PhD (TTUHSC, interdisciplinary in biochemistry and microbiology, 1981)
Why did you choose TTUHSC? Originally, because of a wound healing research program at TTUHSC that I saw in an advertisement on a bulletin board at Indiana University, Kokomo, Indiana, when I was taking classes there in calculus, during my duty as a USAF Base Veterinarian on Grissom AFB, Indiana, Peru, Indiana; when I got to TTUHSC, the program was no longer in effect, so I shifted to the anti-tumor effects of granulocyte and macrophage oxidase/peroxidase systems.
Who did you study under? Johannes Everse (Dept of Biochemistry) and Stanley S. Lefkowitz ( Dept of Microbiology; I believe he is now at University of South Florida, Tampa, FL, on the faculty of the Dept of Microbiology and Immunology).
Describe your experience here. It was very intense and stimulating. I was among the first of the PhD students at TTUHSC and maybe the very first inter-departmental interdisciplinary student. The USAF demanded that under the Civilian Institutions Air Force Institute of Technology Program that I complete my PhD in 3 years; I did so with a six month extension (in 3 ½ years); I believe this might be some kind of record of a single subject PhD, much less a double major PhD.
What did you like or not like about the university and or your experience? I didn’t like the hail, dust storms and the tornadoes; I did like the small town atmosphere for my wife and children and the flexibility of the university in accommodating my educational needs as a USAF military officer assigned to a civilian university; I especially liked the Chemistry Department courses on the main campus and the highly intellectually stimulating environment of the Dept of Biochemistry at TTUHSC; I also enjoyed working with the Dept of Surgery in the Medical School; we gave lectures together to local AMA branches on venomous snakebite treatment (another one of my avocations—venomous snake herpetology).
How did you come to choose medical biochemistry and what drove you to get your PhD? Although I had been on faculty, after my graduation from the Vet School at A&M, as an instructor of pathogenic bacteriology, before going into the military, I thought that pathogenic microbiology was on its way out in the late 70s early 80s; boy was I wrong, with the advent of AIDS (HIV), and other emerging infectious disease, this attitude completely changed (after I graduated from TTUHSC); so I decided to look at biochemistry as a way to unravel the mystery of why white blood cells would make free radicals to kill cancer cells (or infectious agents, but I focused on cancer because that was where the grant support was coming from for my graduate advisor in biochem), when such free radicals probably originally caused the genetic damage that led to the cancer in the first place (and aging as well). In the long run, my interdisciplinary education and approach has led to many opportunities within my military and scientific career to see interactions among many militarily and medically relevant “stressor” interactions—radiation, chemical and biological.
What is your rank and/or title? I am the Senior Scientist for Counterproliferation (a Brigadier General Civilian Equivalent in USAF) for the Human Effectiveness Directorate of the Air Force Research Laboratory
What do you do for the Air Force and why do you enjoy it? I mentor and lead a research team and serve as the USAF’s senior advisor on preventing and countering biological warfare and bioterrorism attacks through non-medical means (not vaccines or therapeutics, although we have spin-off research in this area). I like working with a team, like the conductor of an orchestra with very skilled, mature researchers being the concert masters or first violins. I prefer the group approach as opposed to the individual investigator approach, although I also enjoy having young people enter our group. They come as summer students, post docs, or in collaborative graduate study programs with various universities. I also enjoy “making a difference” in the defense of my country and its civilian population (especially in the case of preventing bioterrorist attacks).
I noticed that your research varies considerably in topic. Is that a result of your job role or are you interested in a myriad of topics? One of my patent attorneys once said that I was a “consummate scientist” ; I am really just a person with insatiable curiosity and interested in learning anything new in science—whether it is biochemistry, microbiology, physics, astronomy or engineering—I guess I am just a generalist or at worst a megalomaniac.
Are there any unique experiences that you’ve had in life you’d like to share? In 2005, I traveled around the world from West (from San Antonio) to East through Dublin, Ireland; the Netherlands; Hong Kong; Hanoi, Vietnam; Korea; San Francisco; and back to San Antonio in 2 weeks. In my last 10 years, I have traveled almost every month. My wife says I have learned to like every place I visit (and especially the one I visited last). These experiences have made me greatly appreciate, and respect other peoples, cultures, and countries, and has led to many gratifying professional international collaborations and interesting experiences abroad. Someday I will write a book about it.
Dr. Kiel,
Thank you for getting this back to me so quickly. I wanted to run something by you. It seems to me based on your answers that I have come across a diamond in the rough.
In this issue of Pulse I am also writing a four page feature story on alumni of the Health Sciences Center who are working in uncommon avenues of health care. I have already started contacting graduates who I knew fit in that category and I believe after what I just read you would be perfect to include in this feature as well.
If you are open to this, I would like to look for another Graduate School of Biomedical Sciences alum to feature in our alumni feature section (the one page features toward the back of the magazine) and move you to my uncommon occupations article instead.
I know you are busy and travel frequently but I will be happy to work with you in any way I can. Because the feature is much more in depth I may have some additional questions.
Ok, I am sympathetic with those suffering from COVID fatigue, and understand how many people just want to forget this tragedy and return to “normal”. However, their previous insulation from such infectious disease and the lull in history it created, are not the historical “normal”, but an illusion of circumstances. This fact is the reason we must not relegate the COVID event to a dusty shelf and forget it as if it were an aberrant case, but use it as a knowledge base and motivation to prepare for future such potentially inevitable events, to mitigate their effects, and learn the circumstances that prevent such events from materializing into full calamities again. I will give several old examples and a new potential one which may emerge. First, the appropriate approach is not solely based on a single discipline such as epidemiology, microbiology, immunology, vaccinology, ecology, sociology, etc. but rather a team, cross disciplinary one. Next, let’s summarize what we have learned about COVID that might guide future responses and which might be exceptional to the disease. COVID is in many ways a typical animal coronavirus https://wwwnc.cdc.gov/eid/article/27/4/pdfs/20-3945.pdf: (1) it is both a respiratory and gastrointestinal virus; (2) it can be very localized to the upper respiratory tract or the GI tract and be resolved there by innate immunity (primarily Interferon) with little consequences (except for generating carrier states or subsequent re-infection); (3) the amount of viral inoculum predicts the degree of the severity of the subsequent infectious disease; (4) it can trigger an immune pathway more familiar in parasitic and fungal respiratory diseases as well as tumor immunology than viral and bacterial diseases; (5) if the first line of defense (innate immune response) fails and adaptive immunity must resolve the infection then the virus becomes distributed in many tissues including the central nervous system (brain) leading to severe or even lethal effects before the adaptive response kicks in and resolves the disease; (6) the severe responses originate with the anti-parasitic response being activated all at once in many tissues, making an effective local response into a severe to lethal generalized response; (7) not suppressing or resolving this generalized response post-infection leads to “memory” which cross reacts with other stimuli non-specifically leading to lingering long term illness; (8) SARS-CoV-2 more profoundly affects the old than young on average unlike animal coronaviruses which are more severe in the young, although the multi system inflammatory response in some children says this generalized collateral damage can occur in children from time to time; (9) the high transmissibility by airborne and physical contact from host to host (and the natural evolutionary drive of mutants toward optimizing this) in close groups of infected (particularly asymptomatic) carriers and susceptible individuals, but failure of long term and distance environmental and aerosol transmission, respectively, maintains the disease in a population indefinitely, and ultimately, endemically. This latter social problem, followed too late by isolation of infected individuals after symptoms and early transmission, leads to the coronaviruses’ continuous maintenance in populations at 10-15% on average but not more at a given time, preventing natural herd immunity and providing plenty of viruses to mutate and select for new dominant variants.
Several new and old measures have proven valuable in prevention and in treatment of early infection, but difficult to uniformly apply, that is, to convince the general population to sustain. Vaccination is very effective, but a sustained large susceptible portion of the population leads to abundance of virus and opportunities for mutations and selection for vaccine-resistant variants. Masking, limiting close contact and vaccination must be simultaneously widely applied or they will become ineffectual in ending the pandemic. It must be realized by the public that viruses do not replicate or mutate in the environment. They are static and decline in infectivity like a biological toxin until they have a host in which to replicate and select for mutations that further their replication. If this cycle is broken, they perish. Antivirals, like Remdesivir (https://jamanetwork.com/journals/jamanetworkopen/articlepdf/2777863/garibaldi_2021_oi_210112_1616042465.1957.pdf) and Molnupiravir (MK-4482, EIDD-2801) (https://www.merck.com/news/ridgeback-biotherapeutics-and-merck-announce-preliminary-findings-from-a-phase-2a-trial-of-investigational-covid-19-therapeutic-molnupiravir/) or monoclonal antibodies (https://www.nature.com/articles/d41586-021-00650-7) truncate the disease only if it is stopped early before the virus is widespread in the tissues, when and where immune-mediated inflammation causes severe disease and possibly death. There is also early evidence that vaccination can reverse chronic lingering effects of COVID, perhaps by shifting the immune pathway away from Th17 toward the Th2 pathway, but not toward Th2 cell produced Interleukin 4 (IL-4), IL-5, and IL-13, which up-regulate antibody production, not toward neutralizing IgG, but toward antibodies targeting parasitic organisms. IL-4 and IL-13 induce B cell switching to IgE (anti-parasitic but allergy yielding antibody) production. IL-5 is the principal eosinophil-activating cytokine, mediating allergic reactions. Immunization may prove to act like “desensitization” to an allergen with allergy shots or by clearing low-level sequestered viral infection (appropriate Th1 as well Th2 pathways).
Three new approaches have grown out of COVID research and development: (1) Gene-based, mRNA and DNA vaccines, which produce precise and effective immune responses, stimulating not only antibodies that block an infection, but also a strong T cell response which can clear infections even if they occur with vaccination before they can become apparent or severe, responding better to mutations, and probably eliminating chronic infections too; (2) a new way to discover drugs by investigating protein-protein interactions; and (3) wearable, wireless, cell phone and app connected diagnostics moving from non-specific illness diagnosis toward the goal of immediate disease-specific diagnostics https://www.laboratoryequipment.com/574395-3-Innovations-Fueled-by-COVID-19-That-Will-Outlast-the-Pandemic/.
A new drug from Pfizer appears to have great promise in truncating COVID. An investigational novel COVID-19 oral antiviral candidate,PAXLOVID™, significantly reduced hospitalization and death, based on an interim analysis of the Phase 2/3 EPIC-HR (Evaluation of Protease Inhibition for COVID-19 in High-Risk Patients) randomized, double-blind study of non-hospitalized adult patients with COVID-19 at high risk of progressing to severe illness. On 16 Nov 2021, Pfizer asked regulators in US to grant ithe drug emergency use authorization. Generic companies can start preparations for the product once they get a license, but have to wait for the regulatory approval before they can supply it. Pfizer claims late-stage trials showed the pill cut the chance of hospitalization or death for adults at risk of severe disease by 89 %. The trials evaluated data from 1219 positive cases across North and South America, Europe, Africa, and Asia. https://www.npr.org/sections/coronavirus-live-updates/2021/11/05/1052679112/pfizer-covid-pill-treatment
All the above are focused on the specifics of COVID but what can we learn from this experience, in general, that combines with older ones to stop new emerging zoonotic disease events leading to pandemics? In my previous writings, I have emphasized how infectious agents fill pre-existing niches rather than merely force entrance into a new host species or environment. It is true that the virus or other microbe must have the means to do this, have the right ligand to bind to the new host receptor or characteristics to survive and be available for infection in the new environment of the new host, but these are based on natural variation (mutations and altered gene expression) coupling with the new host and environment or a deviation in that environment, providing opportunity for first successful entry no matter how imperfect, a foothold, pathogenic ecology. I will give several past and present examples of infectious disease which will illustrate my point; first, my favorite, anthrax.
This disease arises sporadically around the world in every continent except Antarctica, with hiatuses of 30, 40, or more years and even in areas with no recorded outbreaks amongst grazing animals. Outbreaks are associated with wet springs followed by hot, dry often drought ridden summers and rapid disappearance with the onset of winter and cooler temperatures. It is usually very geographically confined and may jump in occurrence among non-contiguous sites. After reports that anthrax bacteria could be grown in the roots of plants in the laboratory, we attempted to see if this occurred under natural conditions in the field. In cooperation with Texas ranchers, we located carcasses of animals that had died of anthrax (confirmed by culture and isolation from samples collected from them) and let them remain in place for three years. No viable spores could be found in the soil around or under or in the carcass remains after three years. However, viable anthrax bacteria were cultured and isolated from roots of plants growing on the sites where the carcasses had deteriorated. Other investigators had found that the anthrax bacteria grew in the guts of soil nematodes. This experiment showed the non-infectious vegetative anthrax bacteria grew in plants (especially during the wet spring growing season) and converted to infectious spores when the plants were stressed or died during the heat and drought, releasing infectious spores into the surrounding soil ready to infect animals, especially if they fed close to the soil or dug it up looking for remaining vegetation to feed on. Therefore, environmental conditions, not just the presence of the pathogen, are required to infect an available, vulnerable host.
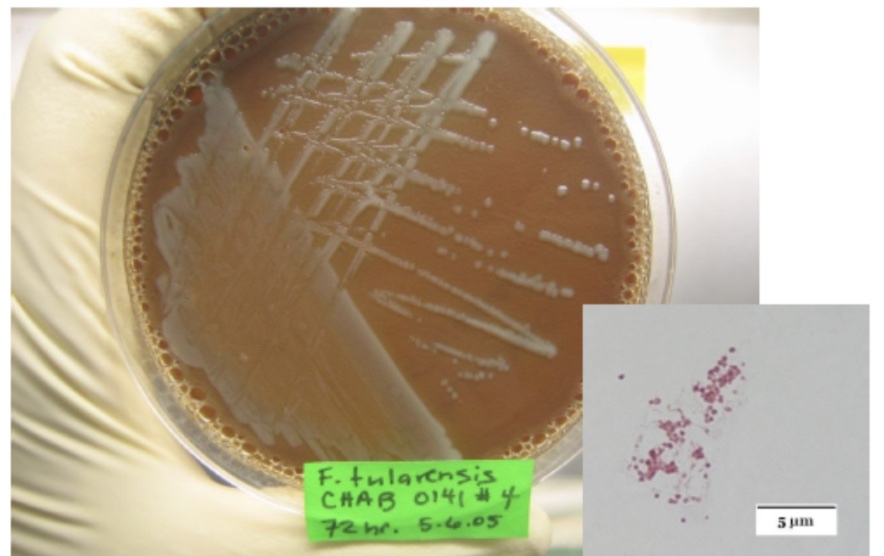
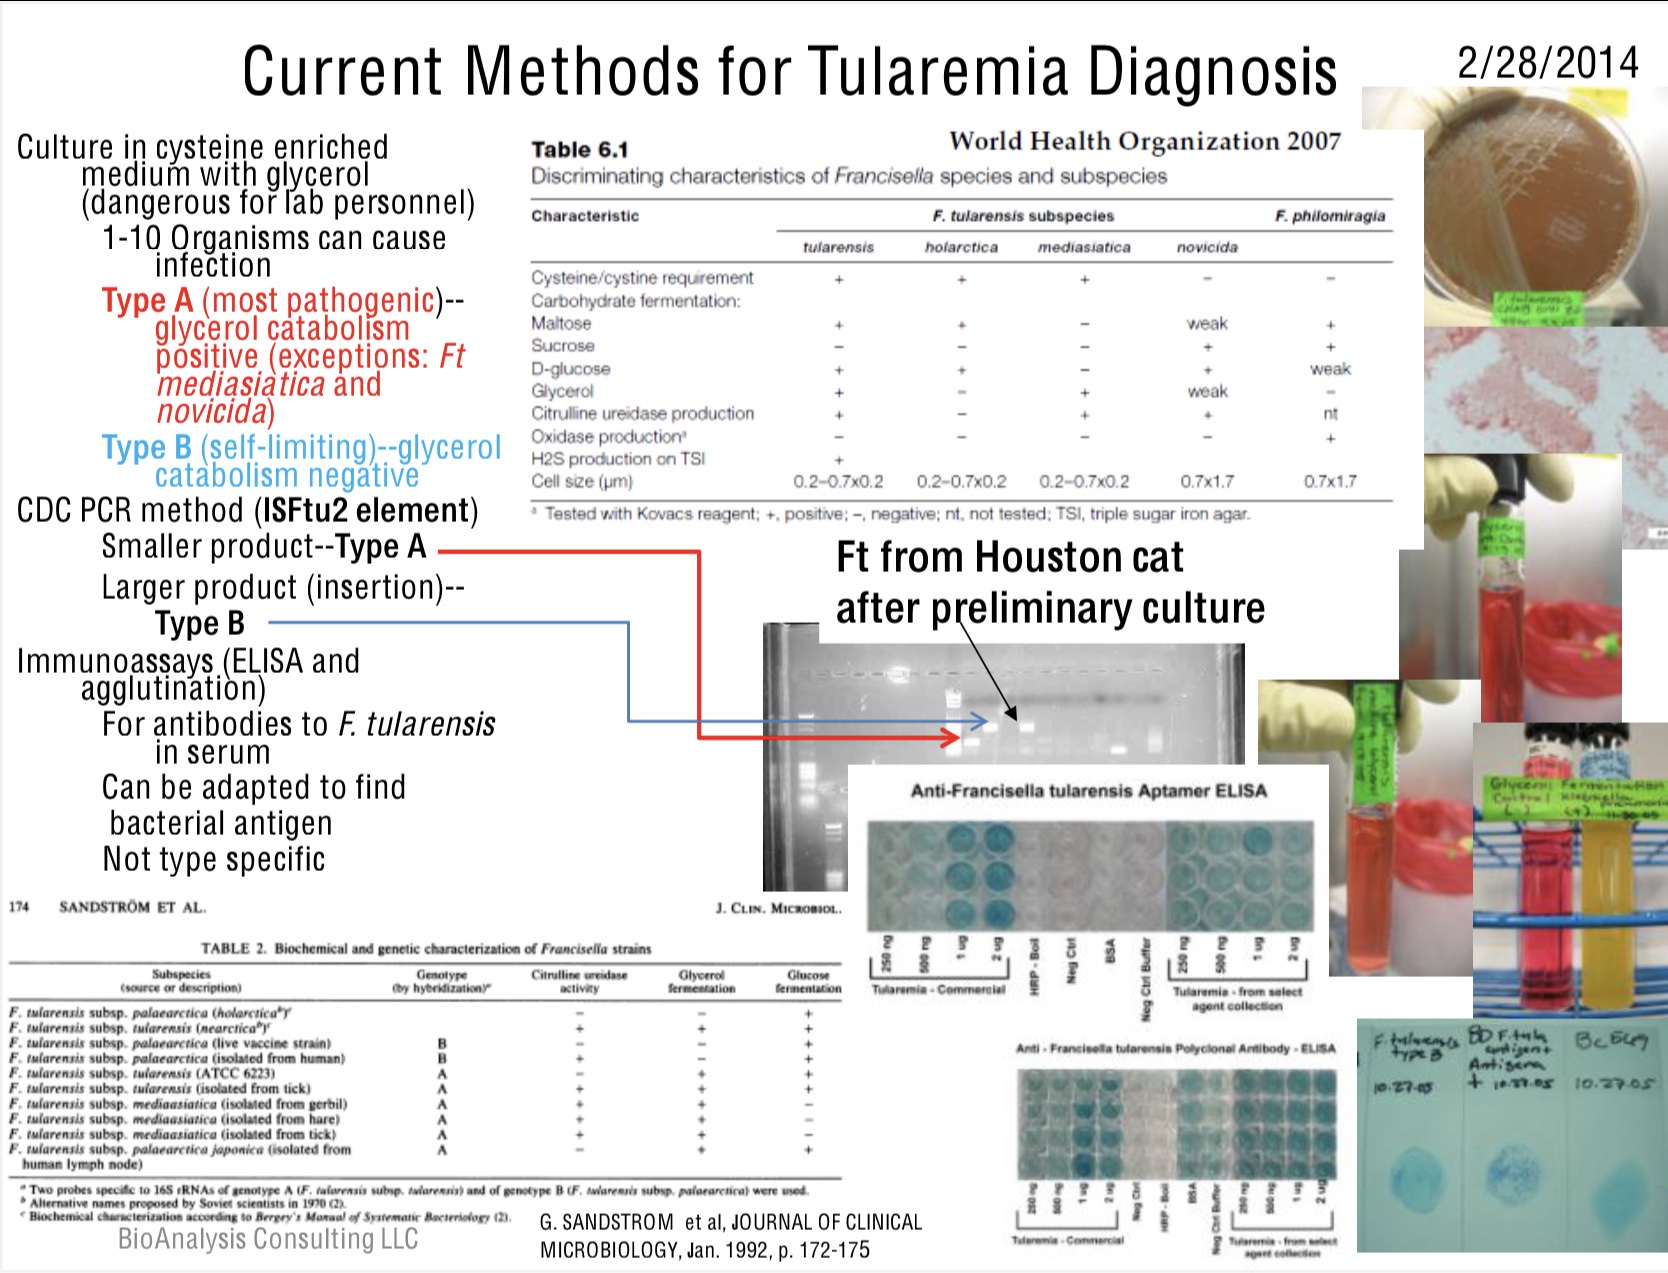
Another example is a changing microbe in an existing environment, altering the course of the infectious disease manifested. Tularemia is usually considered to be of two clinical types, Type A and Type B, associated with certain species and geographical locations. The first case of human tularemia confirmed by bacterial isolation and identification was reported in Cincinnati in 1914. Dr. Edward Francis, also from the US Public Health Service, established Bacterium tularense (fulfilled Koch’s Postulates) as the cause of deer-fly fever in 1928 and the bacterium was eventually named Francisella tularensis in his honor for his contributions. Most of the outbreaks reported in the United States are sporadic. Most cases are in the Ozarks in the Mid-West (between 2001 and 2010, Missouri (19%), Arkansas (13%), Oklahoma (9%), South Dakota (5%), and Kansas (5%)), and in the Northeast in Dukes County (Martha’s Vineyard, Nantucket Island, and Elizabeth Islands off the coast of Cape Cod), Massachusetts, the latter among gardeners and grounds maintenance people. Between 2001 and 2003, the prevalence of the bacterium in a large sample of dog ticks (Dermacentor variabilis) from Martha’s Vineyard was 0.7 per cent. Prior to 1937, there was only one case of tularemia on the island, related to contaminated rabbit meat from the Mid-West. However, after more than 20,000 cottontail rabbits were introduced from Missouri and Kansas into the Massachusetts’ mainland and Martha’s Vineyard and Nantucket Islands for the purpose of sport hunting, cases of tularemia (Type A) began to occur after a hiatus of several years. Every state except for Hawaii has reported cases at one time or another. There has also been a small concentration of cases in the Northwest and others localized in Northern California near San Francisco recently (between 2001 and 2010). Although the main source of tularemia is direct contact with infected rabbits or rodents, it can occur, in humans. through the bite of a mosquito or a gnat, from contaminated food or airborne dust which then contaminates water and/or food. Even though the microbe is rather fragile, the low infectious dose and maintenance in free living amoebas, Acanthamoeba spp., particularly in airborne resistant cysts, makes there environmental contamination widespread. In Europe, its source has been somewhat different (Type B). Tularemia was first recognized as a distinct important human disease in Europe following large water-borne outbreaks which occurred in the 1930s and 1940s in parts of Europe and the Soviet Union. In 1959, Russian researchers designated two subspecies, F. tularensis biovar tularensis (Type A), which is highly virulent in humans and animals, with its principal reservoir being the cottontail rabbit, and F. tularensis biovar palaearctica (Type B), the principal cause of human tularemia in Europe and Asia. It is mildly virulent in humans, but causes large scale, lethal epizootics in the principal reservoirs, the water rat and vole rat. The disease is manifested as ulceroglandular tularemia when entering the skin (which may be without breaking the skin), characterized by a cutaneous and tender regional lymphadenopathy. Percutaneous penetration may also manifest as glandular tularemia, regional lymphadenopathy without ulceration. Inhalation of Francisella tularensis bacteria can result in primary pneumonia, ingestion results in oropharyngeal symptoms of tonsillitis and/or pharyngitis with cervical lymphadenopathy. Other clinical types of tularemia include oculoglandular (infection of the eye) and typhoidal (fever with generalized but no local signs). Tularemia may vary widely as to severity based on the subspecies of F. tularensis subsp. tularensis, Type A being the most severe with a greater risk of death and Type B (Francisella tularensis subsp. holarctica also called palaearctica) being mild and self-limiting. At one time, Type A was considered confined to North America (the United States) and Type B in Europe (especially Russia and the former Soviet Union, where this Type B became the Live Vaccine Strain). Asia was known to have Type A (Francisella tularensis v. palaearctica japonica, Type B subspecies which has traits of Type A) and as such the antigen provided for human serological testing for diagnosing tularemia regardless of type. Only F. tularensis ssp. holarctica has been found in Japan. Tularemia bacterium is probably the least host specific bacterial agent known, infecting greater than 250 species of wild and domestic mammals, birds, reptiles, fish, in addition to humans and transmitted by a wide variety of arthropod vectors. The most common vectors are ticks, in the USA, Dermacentor andersoni (the wood tick), Amblyomma americanum (the lone star tick), and Dermacentor variabilis (the dog tick), which can maintain infection transstadially and transovarially. The most common insect vector is Chrysops discalis (the deer fly). The most common wildlife hosts include cottontail and jackrabbits, beaver, muskrat, meadow voles, and sheep in North America, and other voles, field mice, and lemmings in Europe and Asia. In contrast, tularemia is sometimes considered transmitted directly from an environmental, particularly, natural water source. This confusion has arisen because the more one looks at Francisella in the environment the more varieties, related species and strains one finds. Francisella is the only genus within the family Francisellaceae and is a gamma proteobacteria most closely related to Wolbachia persica, a tick endosymbiont, which begins to explain a lot. Based on DNA sequence and fatty acid composition, there are two species tularensis and philomiragia, with five subspecies of F. tularensis, tularensis, novicida, mediasiatica, and holarctica with a variant of holarctica from Japan which has the characteristics of a Type A rather than Type B Francisella. Philomiragia and novicida are considered the more likely waterborne environmental source forms, but this is in no way absolute in regard to the whole genus. Of these, only F. tularensis subsp. tularensis and subsp. holarctica consistently cause disease in humans, the others have caused disease on occasion under special circumstances. The source of the different levels of pathogenicity is not related to any toxin or clear-cut differences among the low pathogenicity and high pathogenicity species and strains. This ideal categorization has gone out the window. By surveying wild animals, feral cats and ticks in Houston, Texas, in 2005, we found Type B was endemic there and even in the air (found by Biowatch aerosol collectors). It was barely noticed in the human population because of its mild, self-limiting symptoms, but had been diagnosed there as far back as the 1950’s, but forgotten. Recently, Type B tularemia has appeared in Canada but now with symptoms more like Type A, muddling the separation. July 2018, a girl 4 years of age was admitted to the Health Sciences Centre at University of Manitoba for fever, right inguinal swelling, and dysuria. The patient’s symptoms had worsened in spite of completing a 5-day course of trimethoprim/sulfamethoxazole prescribed for presumed urinary tract infection but ineffective against tularemia (trouble with misdiagnosing this disease). The patient lived in a rural area bordering a forest in southern Manitoba, Canada. She had frequent contact with dogs and cats and often became infested with ticks. This and other cases caused by F. tularensis subspecies holarctica suggests that this subspecies might be more common in the Canada than the more virulent F. tularensis subspecies tularensis identified elsewhere in North America https://wwwnc.cdc.gov/eid/article/27/4/pdfs/20-3262.pdf. How can we predict such a change in the presence of a pathogen in a new previously unreported environment? Where to look? We found the answer in using an ecological tool called Geographic Information System (GIS). GIS is an “automated system for the capture, storage, retrieval, analysis, and display of spatial data” https://wwwnc.cdc.gov/eid/article/2/2/pdfs/96-0202.pdf. Common to all GIS is that spatial data are unique because they can be linked to a geographic map. The components of GIS include a database, spatial and map information and some mechanism to link them together. It has been applied to epidemiology since the 1990’s. We extended it to apply beyond a current outbreak to finding the microbe, the tularemia bacterium, in the environment between outbreaks. We used it to find a single infected feral cat in Houston.
Cultured and stained tularemia bacteria (Type B) from Houston, Texas, 2005.The complexity of tularemia diagnostics
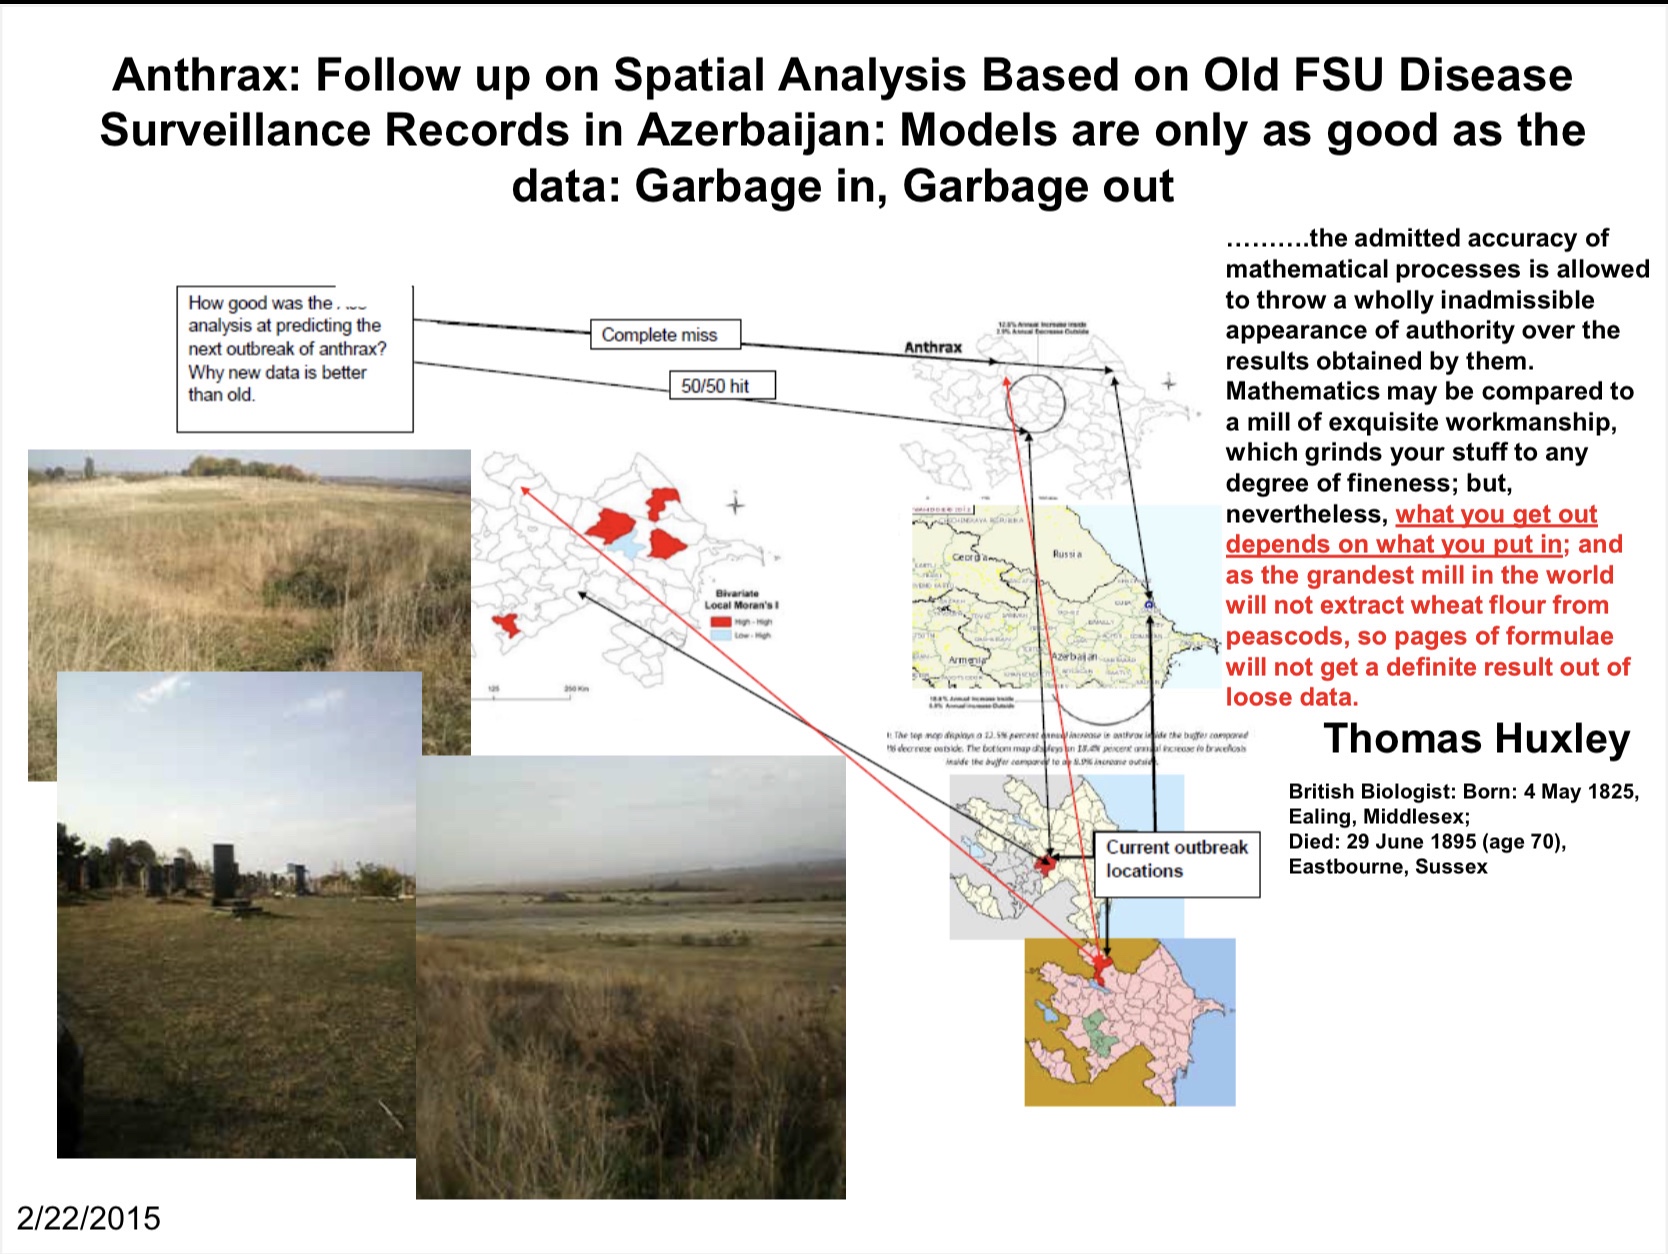
GIS should be applicable to other zoonotic diseases before they emerge. The problem is finding the right data to input into the system.
Good data leads to good results with GIS
My last example is a virus that has the potential to bring back a scourge thought to be eradicated. This final example illustrates how an ecological niche can drive a microbe to fill it. Although it is difficult to test a simple model in an uncontrolled population like humans or animals in the wild, it can and has been demonstrated and predictive in at least one case that supports the validity of the model: the elimination of smallpox in 1977. This global experiment was based on a model assuming that if the proportion of the population that is immune exceeds the “herd immunity” for the infectious disease, then the disease can no longer be sustained in that population. In the case of smallpox, this level was exceeded by vaccination and the disease was consequently eradicated (helped by there being no animal reservoir). But was the ecological space it occupied also eliminated or did it become a vacuum to be filled? The problem is a related orthopox virus called monkeypox in Africa. Actually it is a rodent pox (from African giant pouched rats) that infects monkeys and subsequently humans, producing pox lesions very similar to smallpox. The pox viruses are closely related and widely distributed amongst mammals and birds. They can cross protect in immunity. A shipment of rodents from Ghana, imported to Texas on April 9, 2003, introduced monkeypox virus from West Africa into the United States. The same exotic animal importer introduced another emerging infectious disease previously, Viper Plague, from Ghana into the USA. It appeared to be a rickettsial disease, but later was found to be a co-infection with a rickettsia and a Type D retrovirus, associated with tick infestation, observed in vipers imported from Ghana. The disease had gross lesions very similar to Cowdriosis (Heartwater) a very important exotic animal disease not present in the United States but of great concern because of the potential damage it could cause in the US if it became established in native tick populations, and because it causes great loss (up to 70% lethality) in livestock (cattle, goats and sheep) in Africa. Viper Plague, which proved to be a mimic of Heartwater, and its tick vectors entered the USA in 2002. Tick control and tetracycline treatment of the snakes in prodromal or asymptomatic phases of the disease ended the initial outbreak. However, once signs appeared, it killed 100% of the snakes observed.
The rodent shipment that brought in monkeypox included rope squirrels (Funiscuirus sp.), tree squirrels (Heliosciurus sp.), African giant pouched rats (Cricetomys sp.), brush-tailed porcupines (Atherurus sp.), dormice (Graphiurus sp.), and striped mice (Lemniscomys sp.). CDC laboratory PCR and virus isolation showed two African giant pouched rats, nine dormice, and three rope squirrels were infected with monkeypox virus. Some of the infected animals were housed in close proximity to prairie dogs at the facilities of an Illinois animal dealer. These prairie dogs were sold as pets and then developed signs of monkeypox. The CDC and public health departments in the affected states, together with the U.S. Department of Agriculture, the Food and Drug Administration, and other agencies, prevented further spread of the monkeypox outbreak https://www.cdc.gov/poxvirus/monkeypox/outbreak.html.
Beginning in September 2017, Nigeria has experienced the largest monkeypox outbreak in the country’s history. By November 2019, it reported 183 confirmed cases across 18 states, yielding the largest outbreak recorded caused by the West Africa clade of the monkeypox virus. Genetic analysis indicates multiple introductions from animals into the human population. A viral sample collected in 2018 from a patient in Cameroon was genetically similar to a sample from Nigeria even though there was no epidemiologic linkage. This suggested an epizootic event covering the Nigeria-Cameroon border. This observation was in contrast to the performance of the West Africa clade, which tends to cause temporally and geographically isolated outbreaks. In addition , the 2017–2020 Nigerian outbreak showed a higher prevalence for adults (78% were 21–40 years old), in contrast to historical data of most patients’ being less than 15 years old. The changing demographics of this outbreak offers insights into the changing ecology of monkeypox in West Africa. Investigators have proposed two mechanisms for the resurgence after 40 years of no reported cases https://wwwnc.cdc.gov/eid/article/27/4/pdfs/20-3569.pdf. First, the populace experienced increased exposure to and interactions with forest animals, driven by deforestation, armed conflicts, and population migration. Second, herd immunity has declined because of discontinuing universal smallpox vaccination programs in the 1970’s. The illness typically lasts for 2−4 weeks. In Africa, monkeypox can cause death in as many as 1 in 10 persons who contract the disease. With increasing human to human transmission, the stage is set for a “new smallpox”.
The immunosuppression in individuals with severe COVID may be primarily due to the widespread distribution in patient tissues and organs. SARS-CoV-2 infects human CD4+ T helper cells, but not CD8+ T cells, and is present in T helper cells of blood and bronchoalveolar lavage of severe COVID-19 patients. A recent paper showed SARS-CoV-2 spike glycoprotein (S) directly binds to the CD4 molecule of helper T cells, which, in turn, mediates entry of SARS-CoV-2 into T helper cells but also requires ACE2 and TMPRSS2, Transmembrane Serine Protease 2 (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7359420/pdf/fon-2020-0571.pdf). Once inside T helper cells, SARS-CoV-2 replicates, impairs cell function, and causes cell death. SARS-CoV-2 infected T helper cells produce higher quantities of IL-10, which is associated with viral persistence and disease severity (medRxiv preprint doi: https://doi.org/10.1101/2020.09.25.20200329; posted September 28, 2020, which was not certified by peer review and https://www.cell.com/action/showPdf?pii=S2666-3791%2821%2900015-X. )
Besides immunosuppression, what will maintain the SARS-CoV-2 in populations? Researchers at Tulane University, Harvard University, MIT and Massachusetts General Hospital identified three factors that correlate to increased spread of COVID-19—obesity, age and date of infection. SARS-CoV-2 transmits through the air via large droplets exhaled when someone coughs or sneezes and small droplets people generate when they breathe. Using data from 194 healthy people and non-human primates with COVID-19, researchers determined low spreaders exhale less than 156 particles per liter of air and high spreaders exhale greater than 150 particles/L. There was no correlation with sex, but BMI-years did correlate (generated by multiplying age x BMI). Individuals with less than 650 BMI-years exhaled “significantly less aerosol” than those of 650 BMI-years or more. The elderly, the obese and the obese elderly are more likely to be superspreaders. Those younger than 26 and under 22 BMI are more likely to be low spreaders https://www.pnas.org/content/pnas/118/8/e2021830118.full.pdf.
Although pseudoscience may be literally defined as “false” science, it is much more. It grows out of the need to promote and popularize a myth which is accepted based on some authoritarian view or bias, religious, political, or philosophical, and the need to justify that view with “facts” which are carefully selected to support the view and presented in a way to mimic the scientific method.”— The Black Dragon Trilogy by JOHNATHAN KIEL https://a.co/hnHWBsg. This kind of propaganda now depends on the internet and social media full of testimonials and posting unsubstantiated reports supporting the emotional assertions. Testimonials are not science and neither are uncontrolled observations leading to causal conclusions based on association, especially time related causality. This is not science. It is not based on the scientific method. People also confuse the unedited collection of adverse reactions data by the FDA on medicines and vaccines as causal proof, but it is only to consider all possible adverse reactions for future rigorous scientific investigation using the scientific method (https://www.fda.gov/files/vaccines,%20blood%20&%20biologics/published/Understanding-the-Vaccine-Adverse-Event-Reporting-System-(VAERS).pdf. and https://www.nature.com/articles/d41586-021-00290-x?utm_source=Nature+Briefing&utm_campaign=5eb3714930-briefing-dy-20210217&utm_medium=email&utm_term=0_c9dfd39373-5eb3714930-43804265).
The most notorious example of pseudoscience perpetrated by a scientist involved AIDS in South Africa. UC Berkeley professor Dr. Peter Duesberg, a University of California at Berkeley, tenured professor in the Department of Molecular and Cell Biology, believed that HIV does not cause AIDS. In 1987, he first questioned the link between HIV and AIDS in the journal Cancer Research (“Retroviruses as carcinogens and pathogens: Expectations and reality”. Cancer Research 47 (5): 1199–220, 1987).” In 2000, Duesberg was a prominent member of the panel which advised President Thabo Mbeki of South Africa on the cause of the AIDS epidemic which was exploding out of control in South Africa. This “scientific support” led President Mbeki to deny AIDS was caused by a virus and denied anti-viral treatments in his country. Between 2000 and 2005, more than 330,000 deaths and an estimated 35,000 infant HIV infections occurred. Nicoli Nattrass of the University of Cape Town estimated 343,000 additional AIDS-related deaths and 171,000 infections occurred because of President Mbeki’s administration’s policies. According to Peter Mandelson in 2002, a British Labour Party politician and President of the international think tank Policy Network, it was a “genocide by sloth”. Duesberg recently still asserted his views in a paper first published in 2009, then withdrawn and republished in a revised form, in the peer-reviewed journal The Italian Journal of Anatomy and Embryology (IJAE) in December 2011. This example shows that scientists can also be lured into supporting pseudoscience if they do not manage their biases and remain true to the scientific method even when it contradicts their most favorite hypotheses (I did not say “theories”, which are often confused with the term “theoretical”). Scientific hypotheses are just that, they remain to be tested with well-designed experimentation, while scientific theories, like evolution, or the theory of relativity, are supported by many generations of observations and experimentation and predictive science before being generally accepted as a scientific consensus.
In respect to vaccination hesitancy and resistance, the consequences can be swift and devastating, with diseases almost never seen anymore, erupting abruptly seemingly out of nowhere. From 2011 to date, measles has become a problem for public health officials in the US. There were 220 cases in 2011, just 55 in 2012 and 186 in 2013. The illnesses have appeared in clusters for the most part, although single cases have also appeared in many states. In 2014, there have been three large measles outbreaks. Southern California saw an outbreak from January through May 2014 at 59 cases. New York City had an outbreak that stopped at 26 cases. Ohio has had an outbreak through 16 May 2014, with 83 people infected In 2013 through 2014, in the US, three outbreaks accounted for most of the measles cases. These included clusters of measles cases: in Texas tied to the Kenneth Copeland televangelism ministry and his mega-church; in North Carolina linked to a Hindu religious community and shrine; and in New York City, in 2014, in the Hasidic Orthodox Jewish community in Brooklyn. The national measles report from the Centers for Disease Control 1 Jan through 9 May 2014, released 12 May 2014, showed 187 measles cases from 17 states. Since that report, Ohio reported an additional 23 cases, with new cases in Tennessee, Pennsylvania, Massachusetts, and other states. The measles cases in both Ohio and California, in 2014, were linked to an ongoing measles epidemic in the Philippines. Both outbreaks in the States were results of travelers returning from the Philippines who had not been vaccinated and who brought back incubating measles. Six cases in Washington State were in patients without immunizations with ties to the Dutch Reformed Church, in British Columbia, which was the center of a 400-case outbreak of measles. The church opposes the use of all vaccines, including the measles vaccine. These examples illustrate the effects of misinformation, particularly on the internet and social media, where its removal is problematic, and perhaps, where it remains eternal. A study of the correlation of the dissemination of such information, the decline of vaccination, and the occurrence of cases should be made. My hypothesis is that the correlation would be high, and the pattern would resemble the spread of an infectious disease itself, with the computer being the vector and the electronic misinformation being the infectious agent (at least a surrogate for measles). Now imagine the consequences of anti-vaccination campaigns against SARS-CoV-2 and the devastation which has already occurred at this writing to date, continuing indefinitely because herd immunity can never be reached through “natural means” and large populations of unfettered virus allows for probable continuous emergence and “ natural selection” of resistant variants. This is, as I have posted earlier, the common nature of coronaviruses. Finally, as noted in a previous post, development of immunity after widespread dissemination of the virus in organs and tissues sets them up for devastating immune mediated complement interactions and innate immune cell (neutrophil and other granulocyte) mediated collateral destruction of blood vessels and other tissues.
All this being said, potential detrimental effects as well as beneficial ones of treatments and vaccines must be reported and investigated by the scientific method with even handedness. This includes herbal and indigenous peoples’ remedies. Historically, pharmaceuticals and pharmacology are deeply rooted in botany of medicinal plants; many which originated in folk remedies but which stood scientific scrutiny. Examples include Belladona (resulted in atropine and scopolamine), digitalis (digoxin), quinine, and lastly, the very important antimalarial drug Artemisinin (Chinese remedy). Belladonna (Atropa belladonna) is a plant which has been used as a medicine since ancient times. “Belladonna” means “beautiful women” used by the ladies of Renaissance Italy to enlarge their pupils, which they found alluring. But because it can be a lethal poison, the plant of origin also goes by the more sinister name deadly nightshade. Digoxin and digitalis are cardiac glycosides derived from the plant, foxglove, used to treat mild to moderate congestive heart failure and abnormally rapid atrial rhythms (atrial fibrillation, atrial flutter, and atrial tachycardia). The quinine mentioned above, and its present day Chinese successor, Artemisinin (from Wormwood), are actually very old remedies. Quinine, from the bark of the cinchona tree, and which can now be made synthetically, was originally discovered by the Quechua, indigenous people of Peru and Bolivia. Jesuit Missionaries were the first to introduce cinchona to Europe in the 17th century. Chinese herbalist’s use of Artemisia annua (Wormwood), which predated quinine, was first described in a 4th-century Chinese text, the source of the modern day antimalarial drug arteminisin. Quinine was commonly used for treatment of malaria until the 1940s, when chloroquine and other drugs were developed because they had fewer side effects. Except for vitamin D3 (addressed in a previous post) and some ongoing studies on the microbiome, I know of no other natural remedies being scientifically examined for prevention or treatment of COVID at this time. However, recent studies don’t support the expectations for Vitamin D3. In a study of hospitalized COVID-19 patients, a single high dose of vitamin D3 did not significantly shorten hospital lengths of stay. These findings do not support the use of high dose vitamin D3 for treatment of moderate to severe COVID-19. Criticism of this study suggesting that it did not look at subpopulations of different severity independently or early treatment suggests that the treatment should not be rejected before it has been further studied and then found effective or not (https://jamanetwork.com/journals/jama/articlepdf/2776738/jama_murai_2021_oi_200145_1613509376.92008.pdf and https://jamanetwork.com/journals/jama/articlepdf/2776736/jama_leaf_2021_ed_200126_1613509372.9982.pdf). Vaccination, in spite of variants, (https://www.researchsquare.com/article/rs-226857/v1 and https://jamanetwork.com/journals/jama/articlepdf/2776739/jama_walensky_2021_vp_210031_1613509382.71695.pdf.) and sanitary precautions are still our best defense against COVID. What is certain, COVID can be lethal and can have persistent long term debilitating effects which are lacking with vaccination and can be prevented by it.
Out of my frustration with ignored proposals for support and failure of acceptance by institutions, I have decided to fully disclose my concepts and ideas of my last, and believe most important, contribution to medical science. This is the briefest and most complete description I can give in an effort to engage others more competent to take up the pursuit, with I hope, greater success than I. In discussing the limitations of CRISPR, two major points come to mind: 1) how to deliver it and 2) how to prevent off target effects. Francisco Mojica discovered CRISPR in 1993. He researched these sequences and their products throughout the 1990s, and into 2000. He recognized that the various repeat sequences shared a common set of features, the CRISPR sequences (a term he created in correspondence with Ruud Jansen, who first published the term in 2002). In 2005, he reported that these sequences matched subset sequences from the genomes of bacteriophages (Mojica et al., 2005). This led to the hypothesis, which was later proven, that CRISPR is an adaptive immune system to prevent further invasion and replication of bacteriophages in the host bacteria. The other group to independently discover this fact published similar findings in 2005 (Pourcel et al., 2005). The Nobel Prize in chemistry was awarded in 2020 to Jennifer Doudna and Emmanuelle Charpentier “for the development of a method for genome editing”, developing CRISPR. A recent Science Magazine article discusses the hope and difficulties of delivering CRISPR to correct a rare but devastating genetic disease. CRISPR research shows promise for correcting the faulty wolframin gene but it affects so many tissues, researchers will have to figure out how to deliver CRISPR components to most cells in large organs such as the brain and liver, a “pretty daunting task”. It might take 10 to 20 years to accomplish. The syndrome named for Donald Wolfram, a physician at the Mayo Clinic in Rochester, Minnesota, in the 1930’s, and an ophthalmologist colleague, ruled out malnutrition as the cause of the puzzling condition and discovered it was hereditary. Recessive mutations in the gene for a protein called wolframin are responsible for most cases, with involvement of a second gene causing the remainder. However, the pair was wrong to think the defect lies only in the brain. Instead, the symptoms stem from widespread cell death. The first sign of the illness, appearing in children, is usually diabetes mellitus, because of loss of insulin-secreting beta cells in the pancreas. Most patients also develop diabetes insipidus, in which the pituitary gland does not produce the hormone vasopressin (AVP), which is also known as antidiuretic hormone (ADH), that helps control the body’s fluid balance, causing the kidneys to produce huge amounts of urine. Blindness will also develop; patients usually go blind within 10 years of their first visual symptoms https://t.co/DCWpJuCJAI.
Using CRISPR has other problems associated with introducing foreign protein. Editas Medicine and Allergan announced human in vivo CRISPR-therapy trials for an inherited blindness, but have run into a potential hurdle to therapeutic CRISPR, the human immune responses to its bacterial components. For instance, a majority of tested blood samples showed existing immune responses to Cas9, which is commonly taken from Staphylococcus or Streptococcus bacteria. It is needed to do the double-stranded cutting of the DNA to remove the offending gene to be replaced. Correcting multiple genes is also a problem, but may have an answer in CRISPR. The solution is in multiplexing, changing more than one gene at a time, requiring only the introduction of a single Cas enzyme and of gRNAs (guide RNAs which direct the cutting of the DNA by hybridization of the specific RNAs to the DNA to be excised), and template DNAs for each targeted gene. CRISPR multiplexing to tag multiple genes in the same cell is achievable, but in practice, gets increasingly complicated with each added gene https://www.sciencemag.org/features/2019/09/beyond-crispr-what-s-current-and-upcoming-genome-editing and https://www.frontiersin.org/articles/10.3389/fbioe.2019.00459/full.
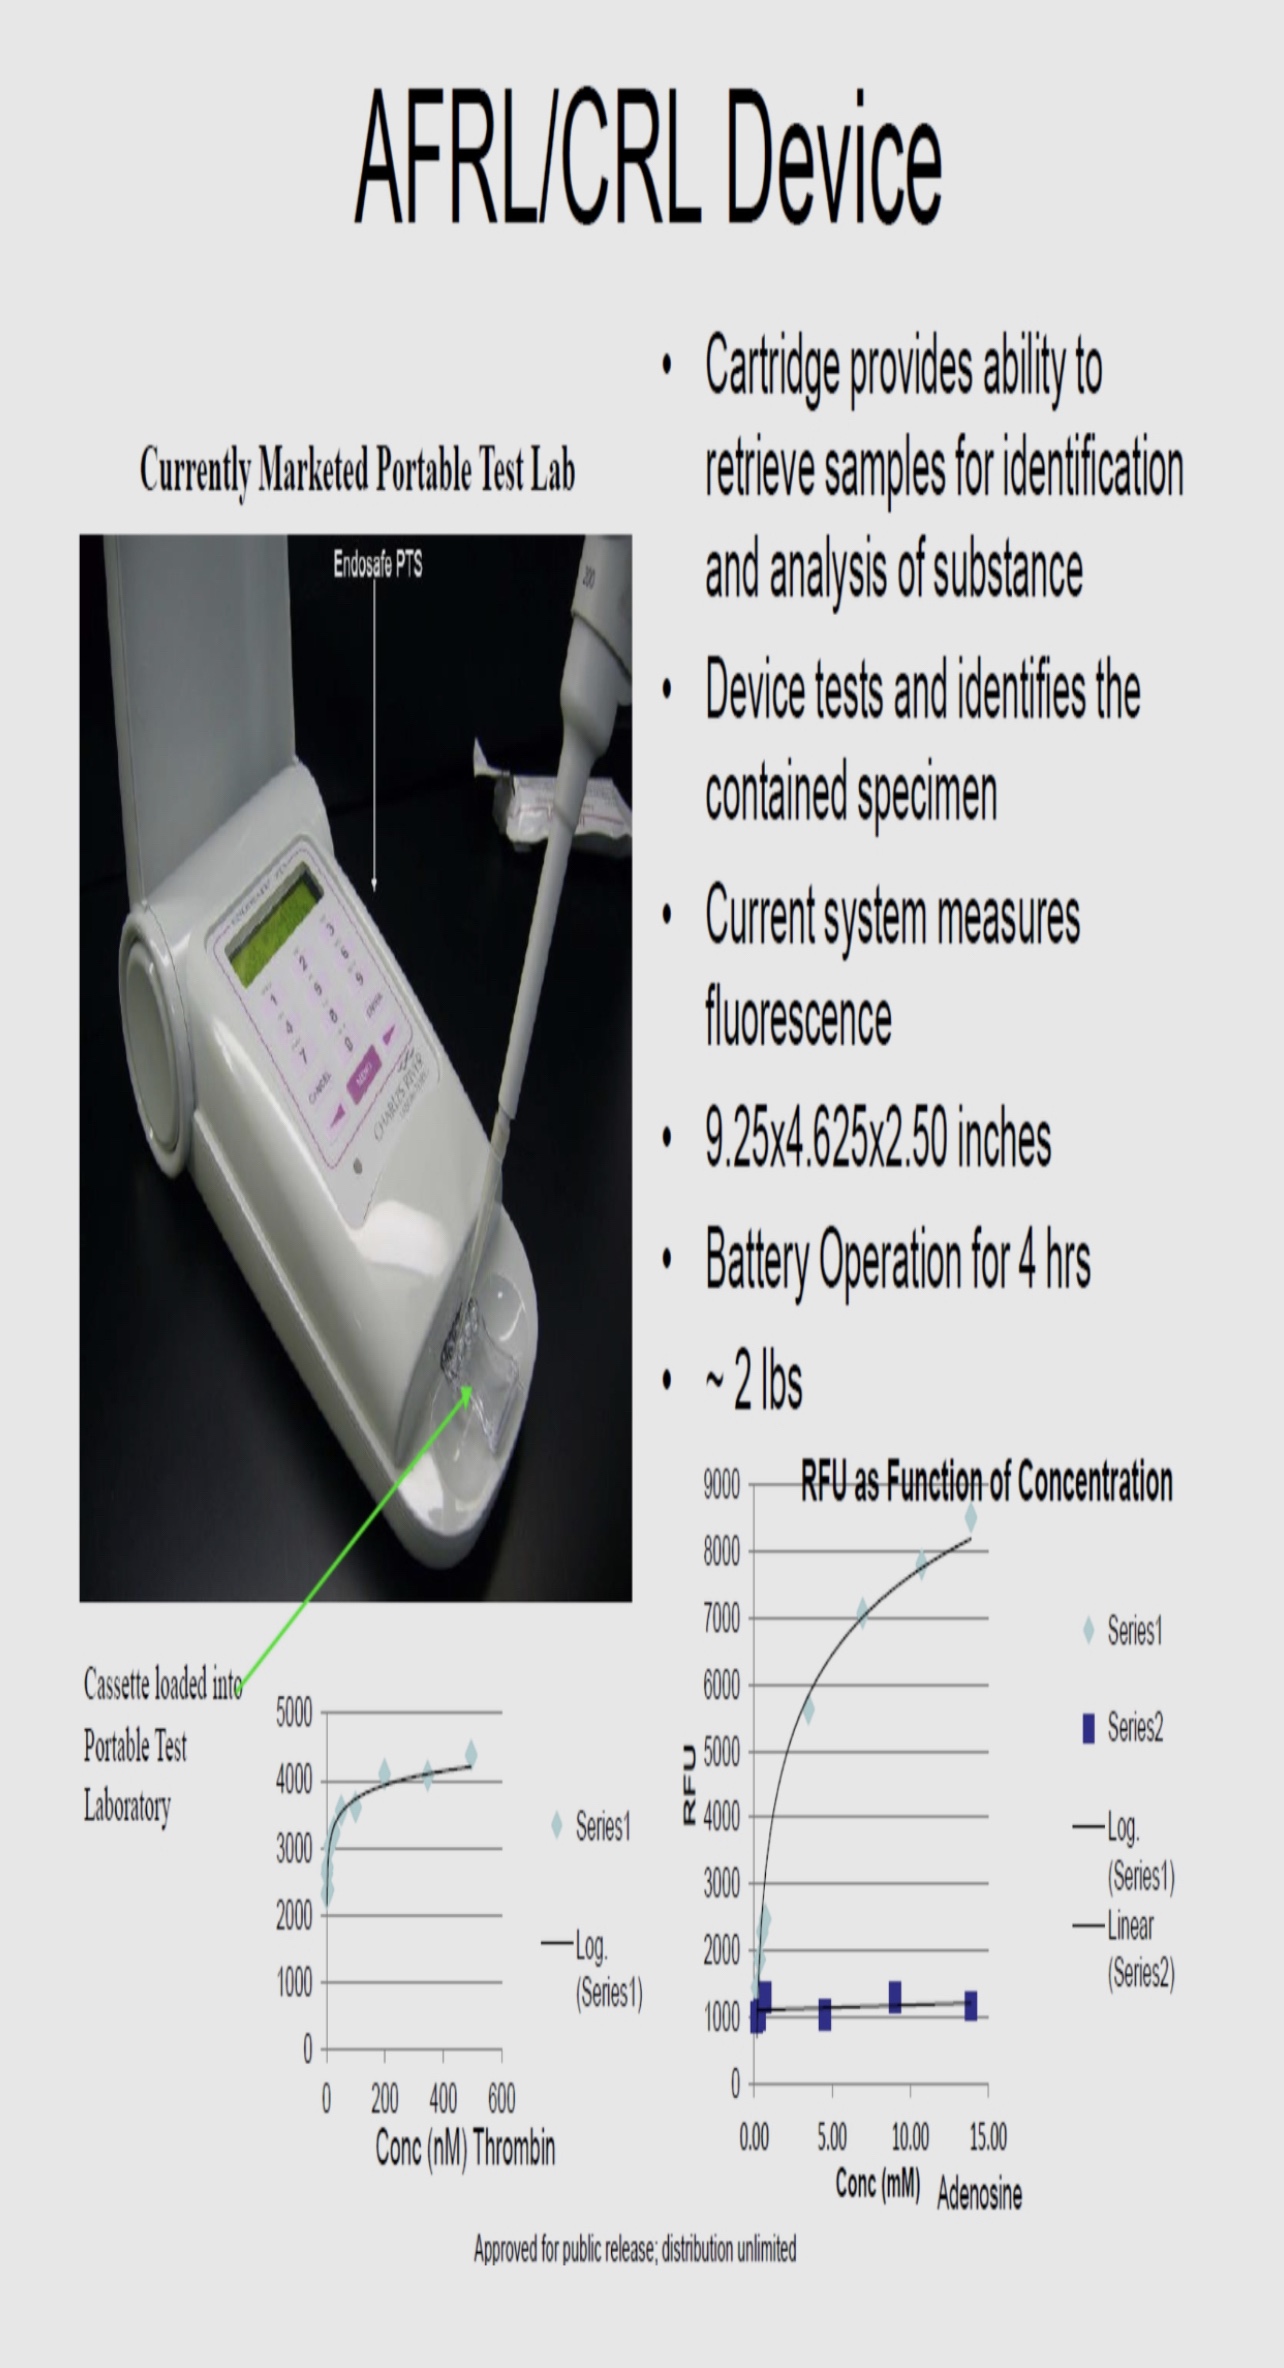
Our solutions, including a delivery system for CRISPR, grew out of USAF Air Force Research Laboratory Brooks Counterproliferation Team’s research to answer requirements of Special Forces for biodefense Counterproliferation. We needed methods and equipment to immediately detect, identify and safely collect and isolate highly pathogenic microbes rapidly in non-permissive territories for their safe return to the laboratory, with chain of custody, for further culture, analysis and attribution. As a fortuitous consequence, these methods and equipment could be used with little or no support and with simple to operate and maintain equipment which would be very useful in the most remote areas of developing countries. Even the reagent manufacturing could be accomplished in place with portable fermentation miniature plants by microbial biosynthesis. Additional mechanisms of electromagnetic radiation interaction, allowed for raising the impact of the detection system to the level of specific antimicrobial biocidal effects on the microbes in the environment. The process also had the potential of inhibiting, killing or genetically altering the microbes in vivo. The last step before closing the program demonstrated that the nanotechnology was operational in animal and human cells without being lethal, suggesting utility in genetic therapy in animals and humans. These experiments, preliminary applied science, and concepts were not developed and fully exploited for field and medical applications. What follows are step by step progression of the development and concepts of the technology I had hoped would be applied to Global Biosurveillance, Counterproliferation, and infectious disease control as close to the source of the outbreak as possible. The nanoparticle material would have to be carefully selected to avoid toxicity. For instance, carbon nanotubes can cause lung inflammation and fibrosis if inhaled but are broken down by myeloperoxidase and other oxidative enzymes (http://www.particleandfibretoxicology.com/content/3/1/15, Franco Cataldo and Tatiana Da Ros, Editors, Medicinal Chemistry and Pharmacological Potential of Fullerenes and Carbon Nanotubes, and Prabakaran Ravichandran et al, PULMONARY BIOCOMPATIBILITY ASSESSMENT OF INHALED SINGLE-WALL AND MULTI- WALL CARBON NANOTUBES IN BALB/C MICE, JBC Published on June 24, 2011) and may even be useful as immune adjuvants to stimulate immunity induced by vaccines. The synthetic Nanobes may simply be used to induce biosynthetic Nanobes in the manufacturing process and avoid all toxicity problems all together. Could these technologies along with CRISPR be brought to bear against SARS-CoV-2 and all its variants? New emerging or old re-emerging pathogens?
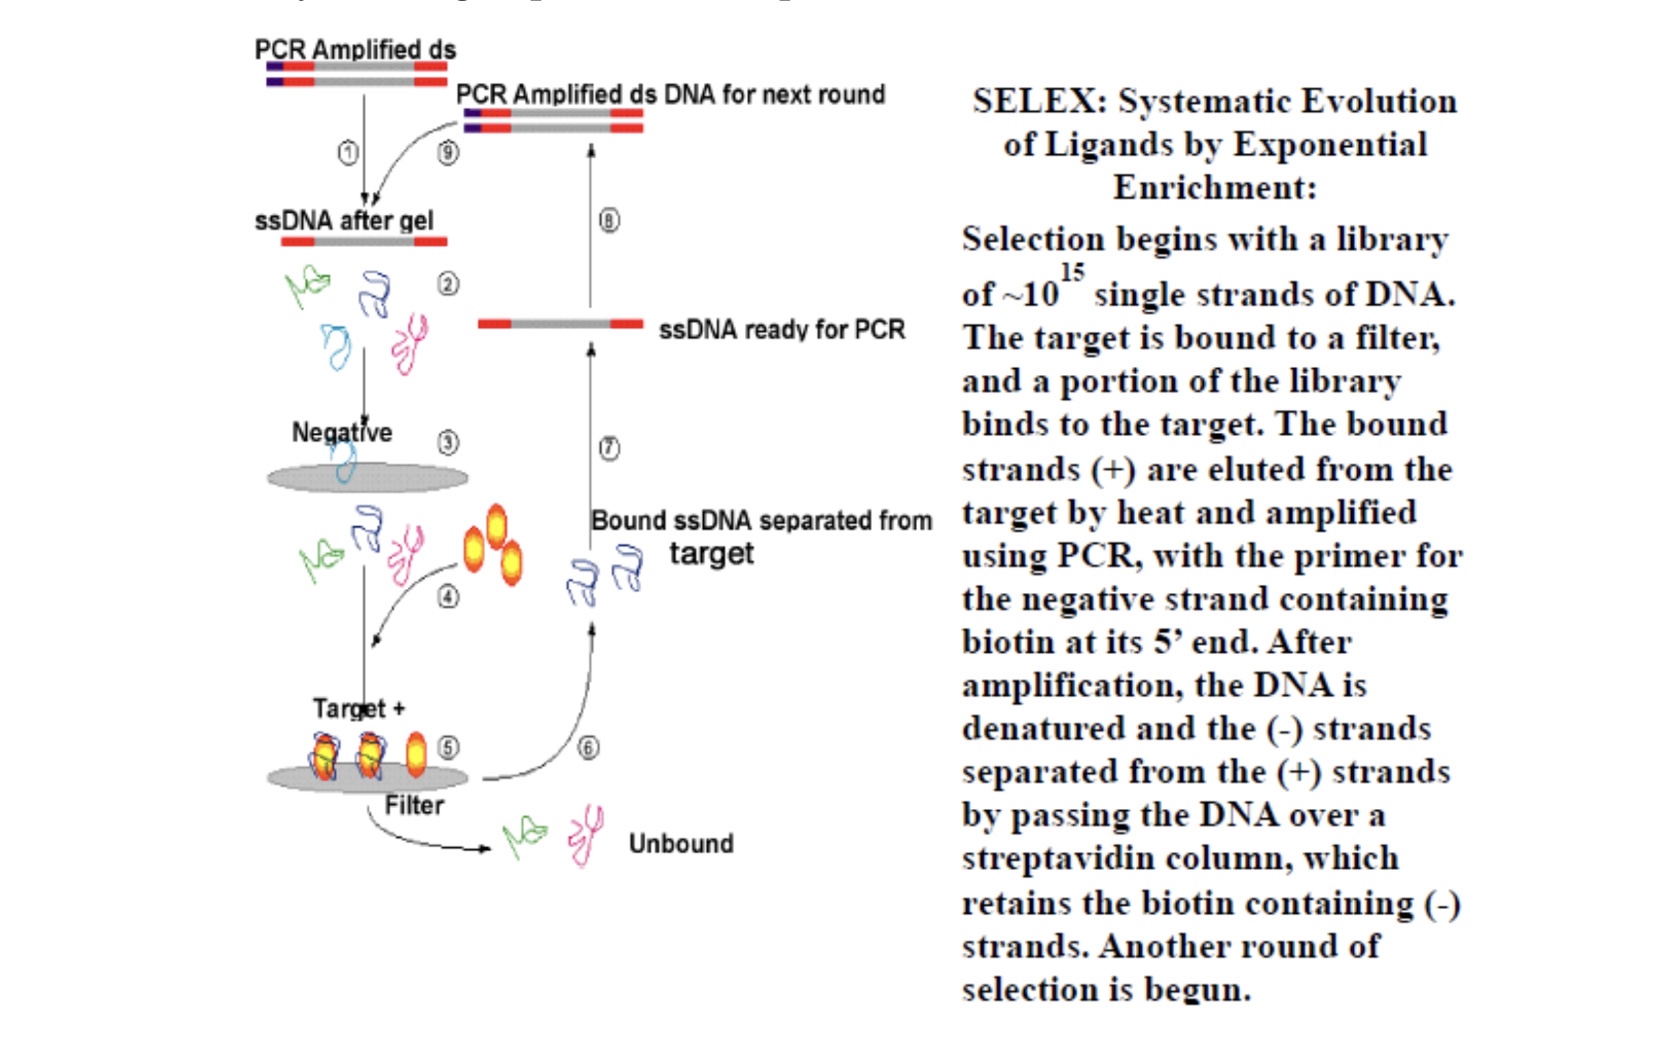
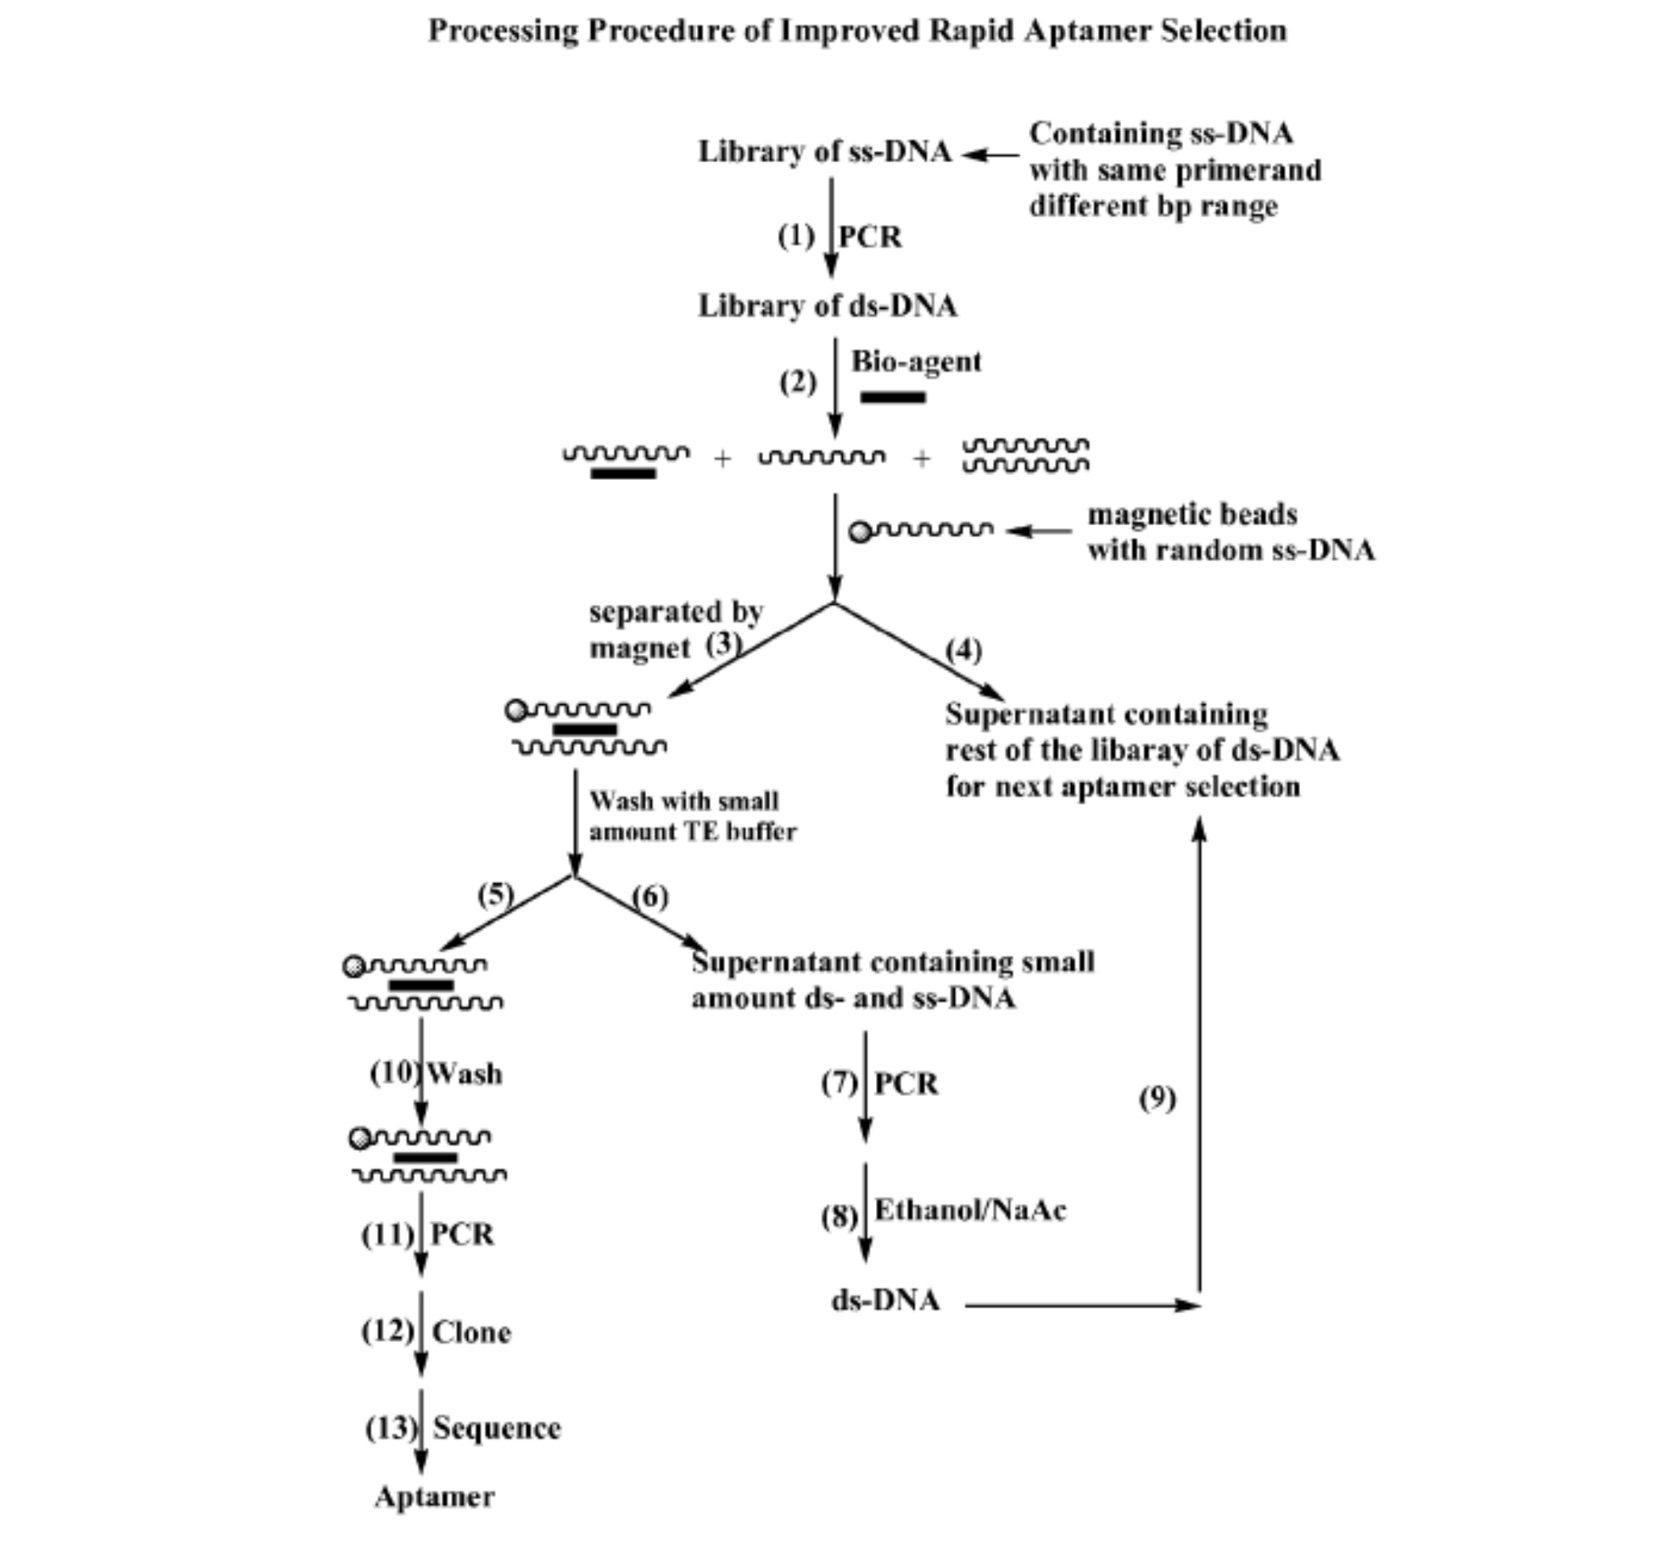
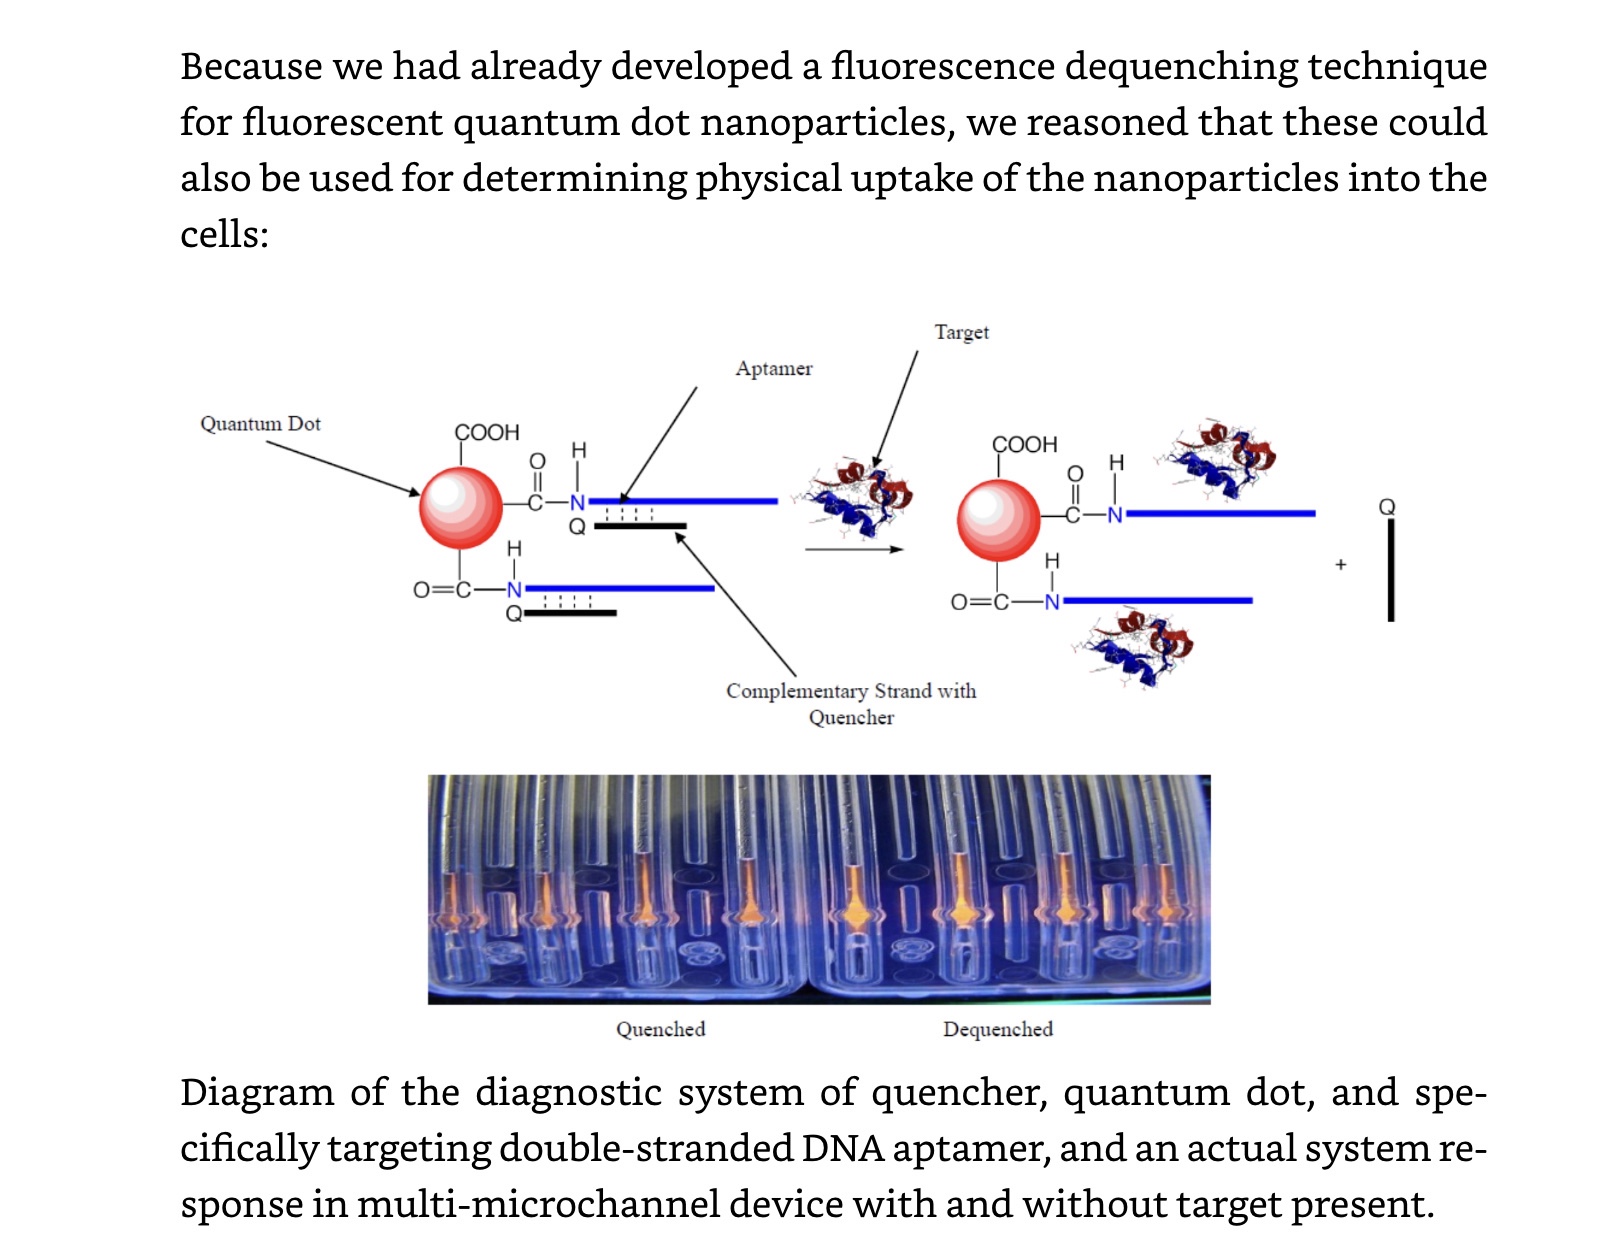
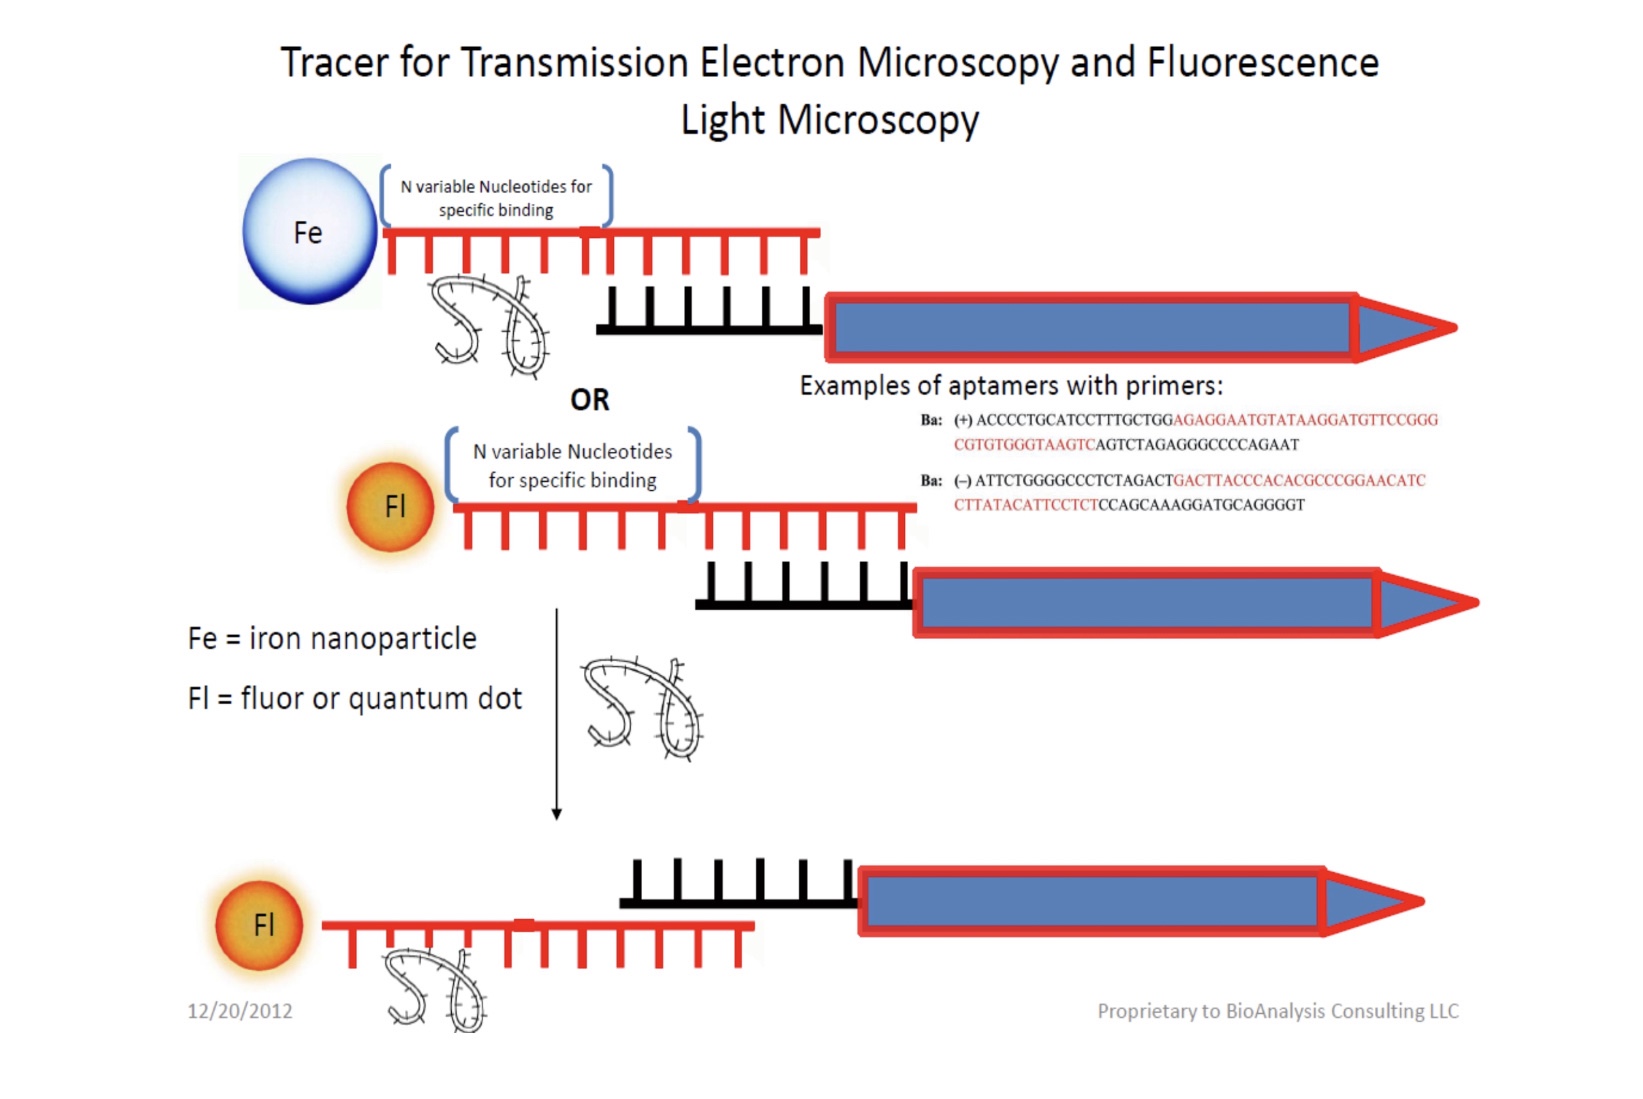
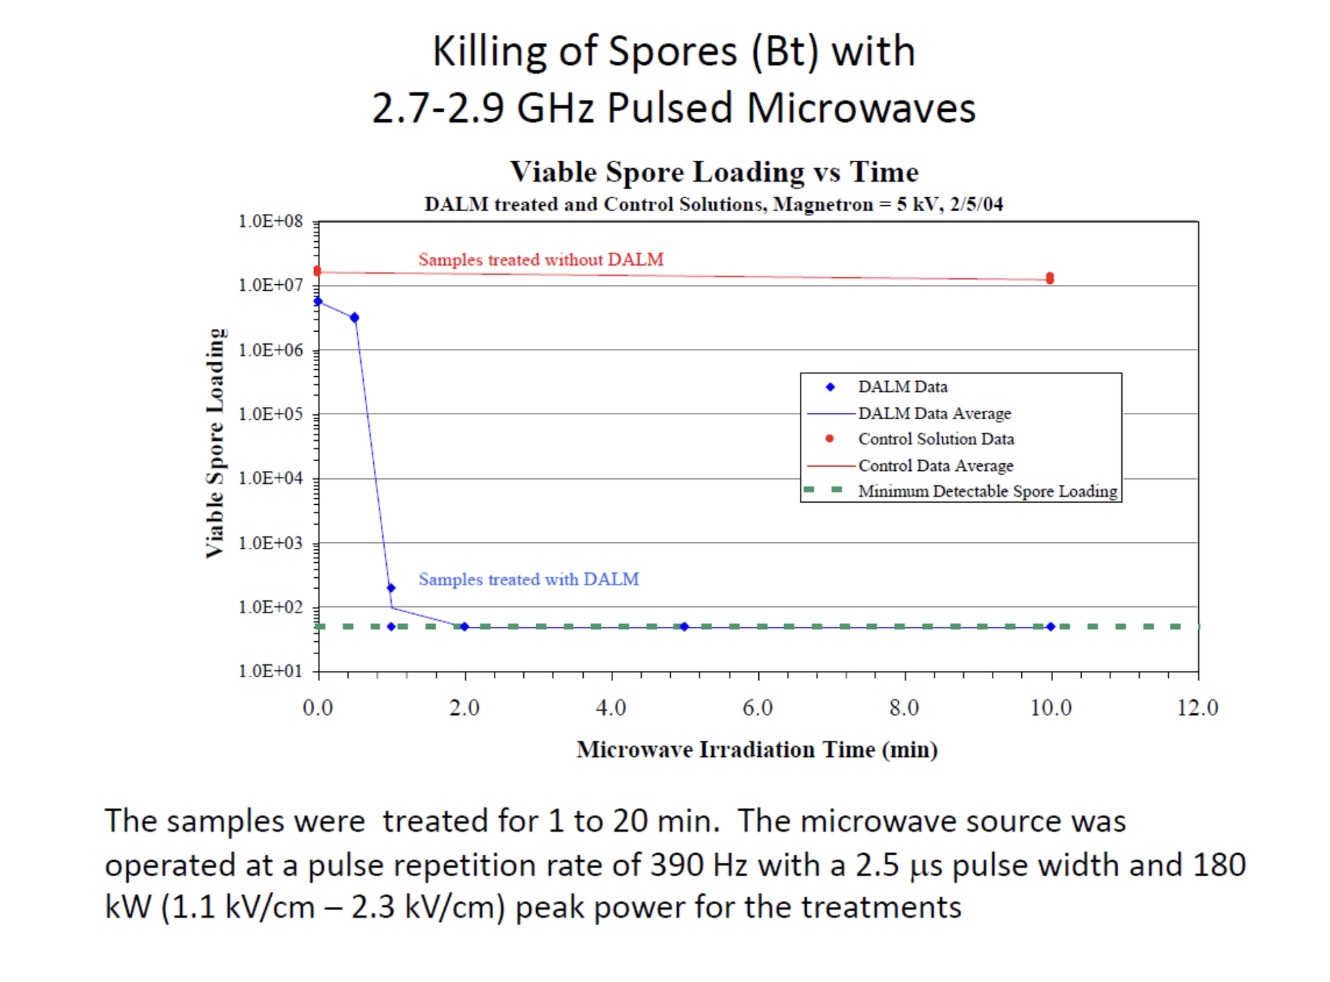
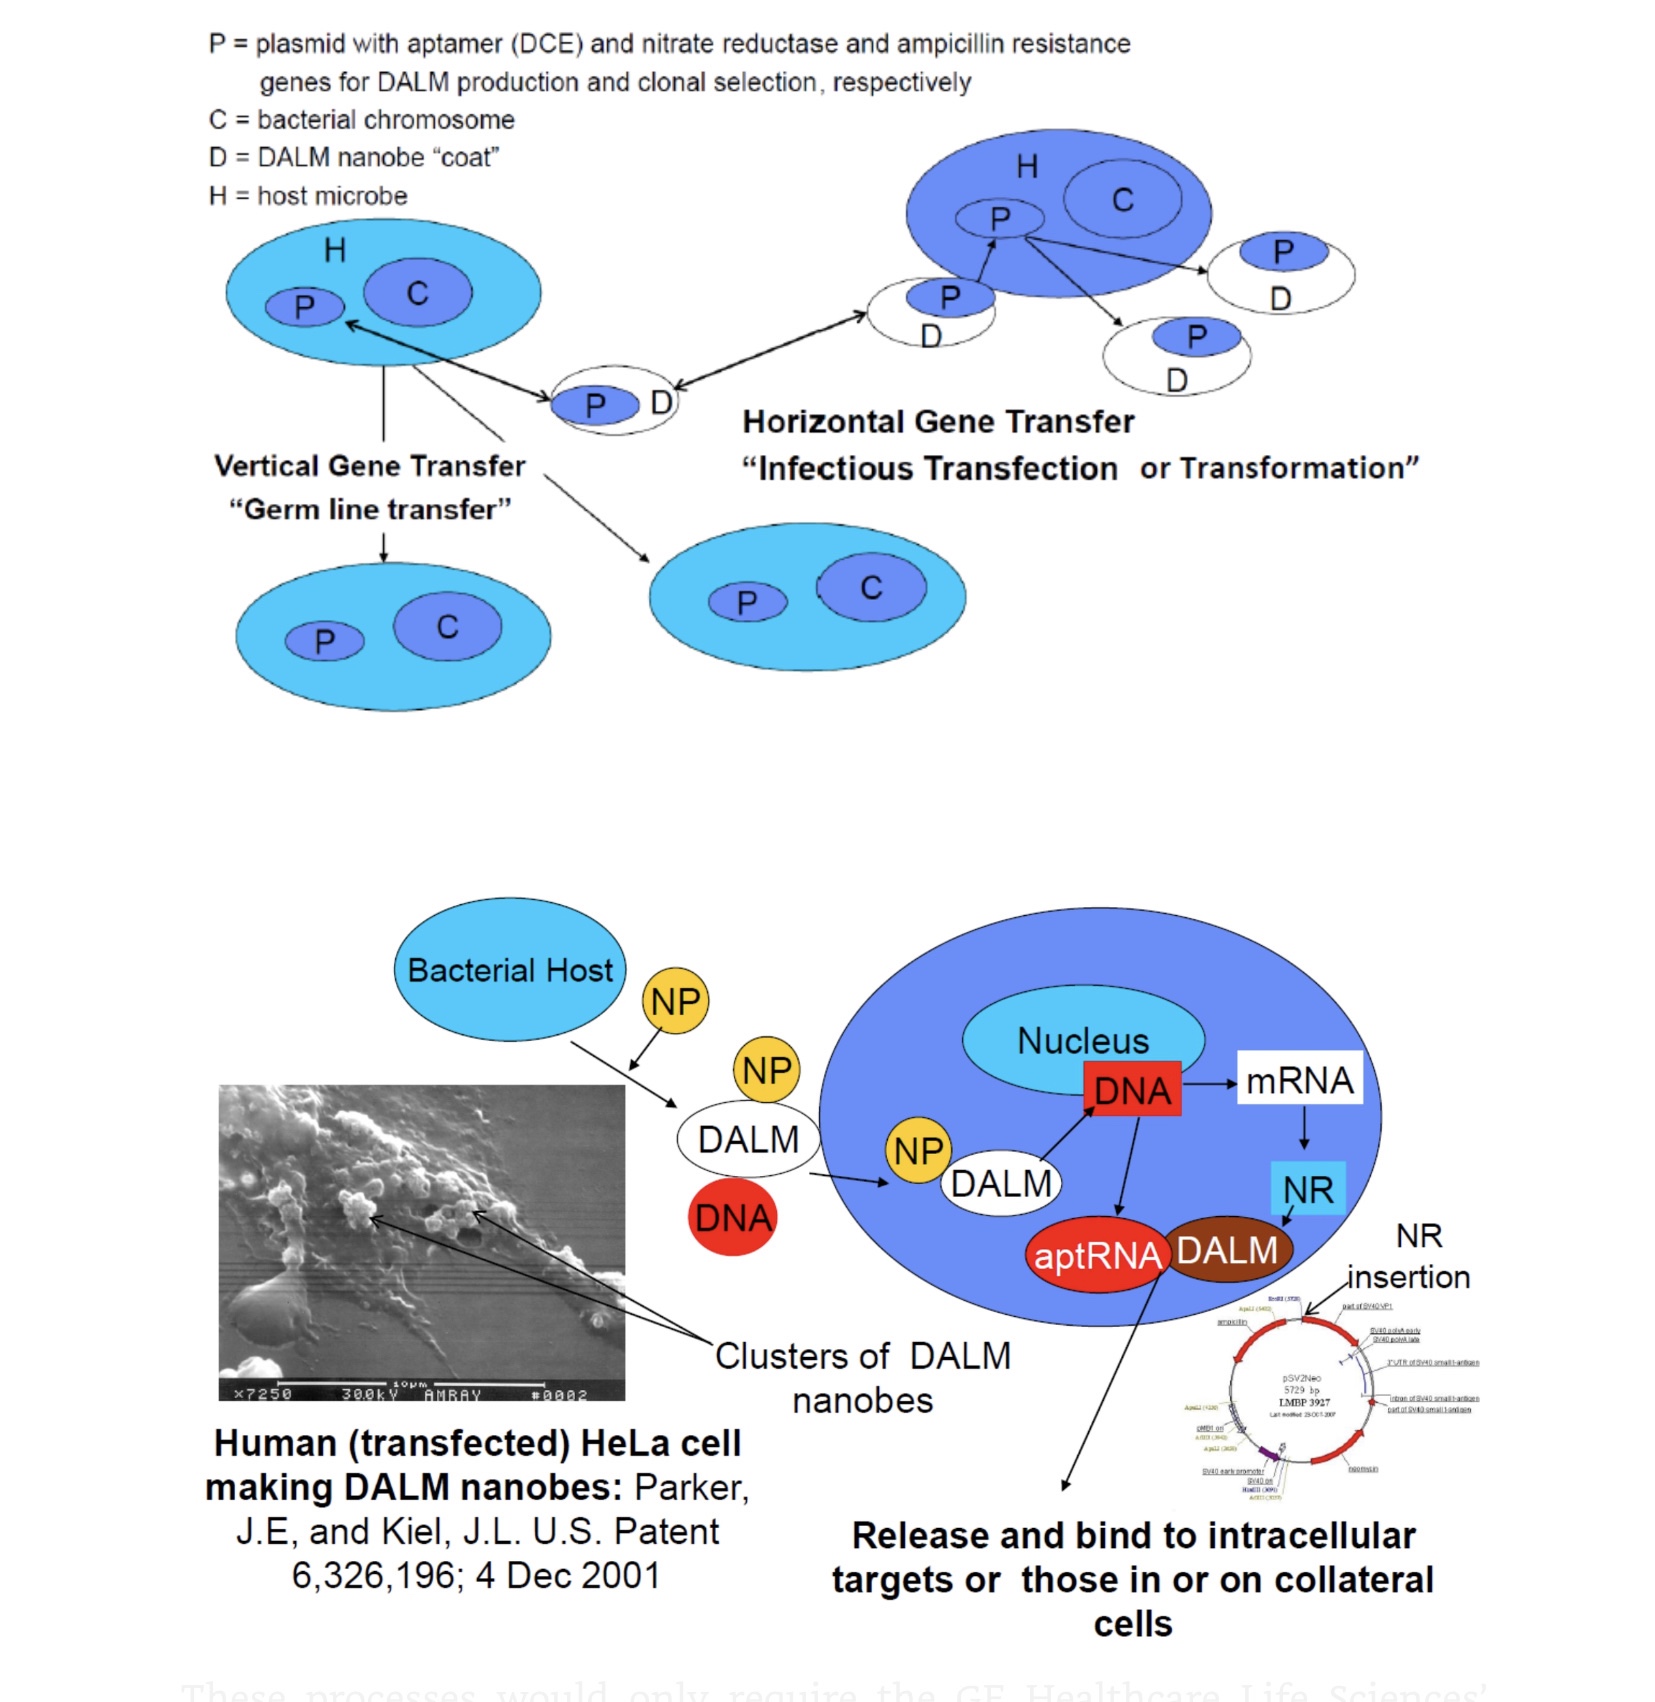
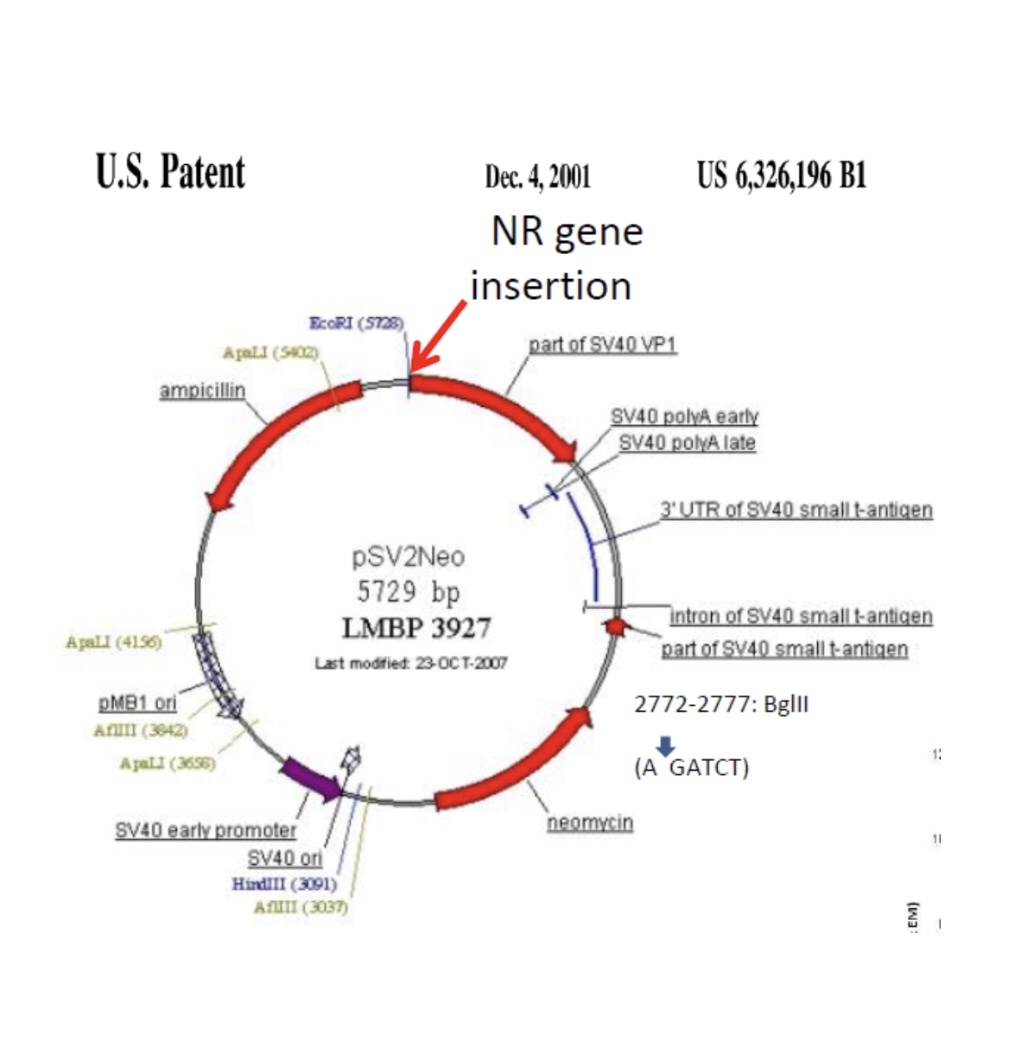
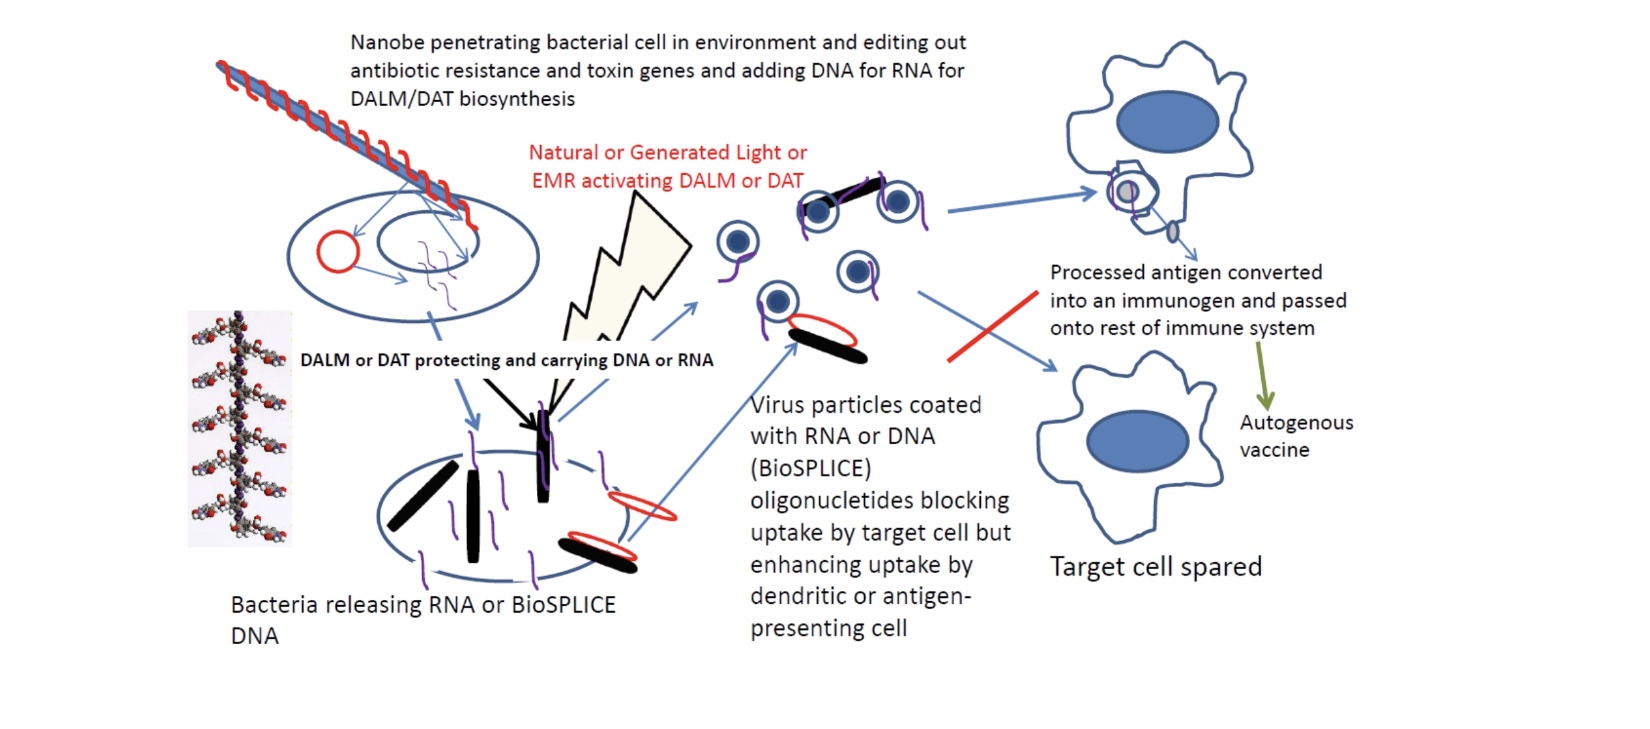
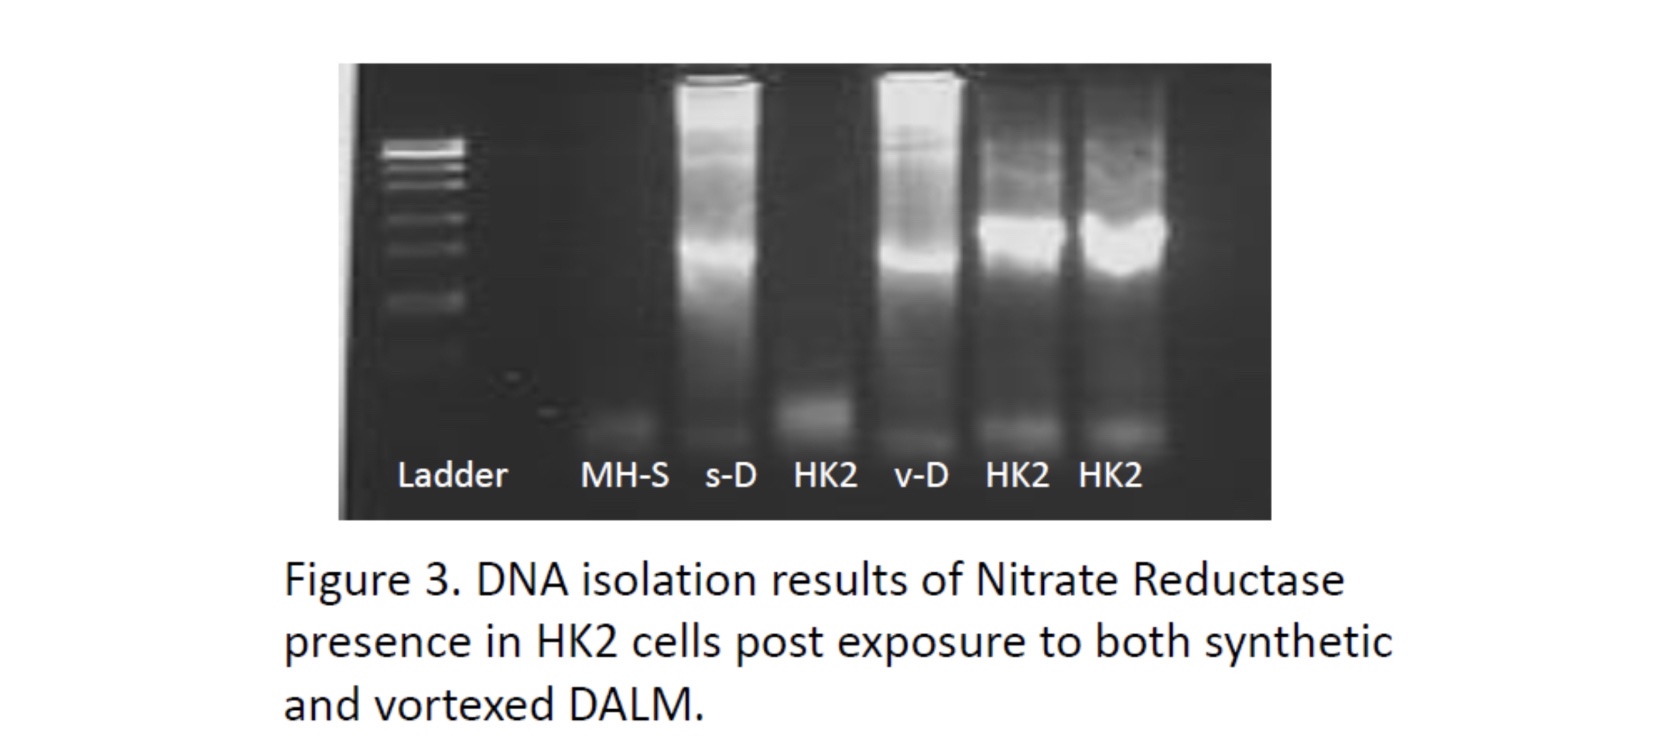
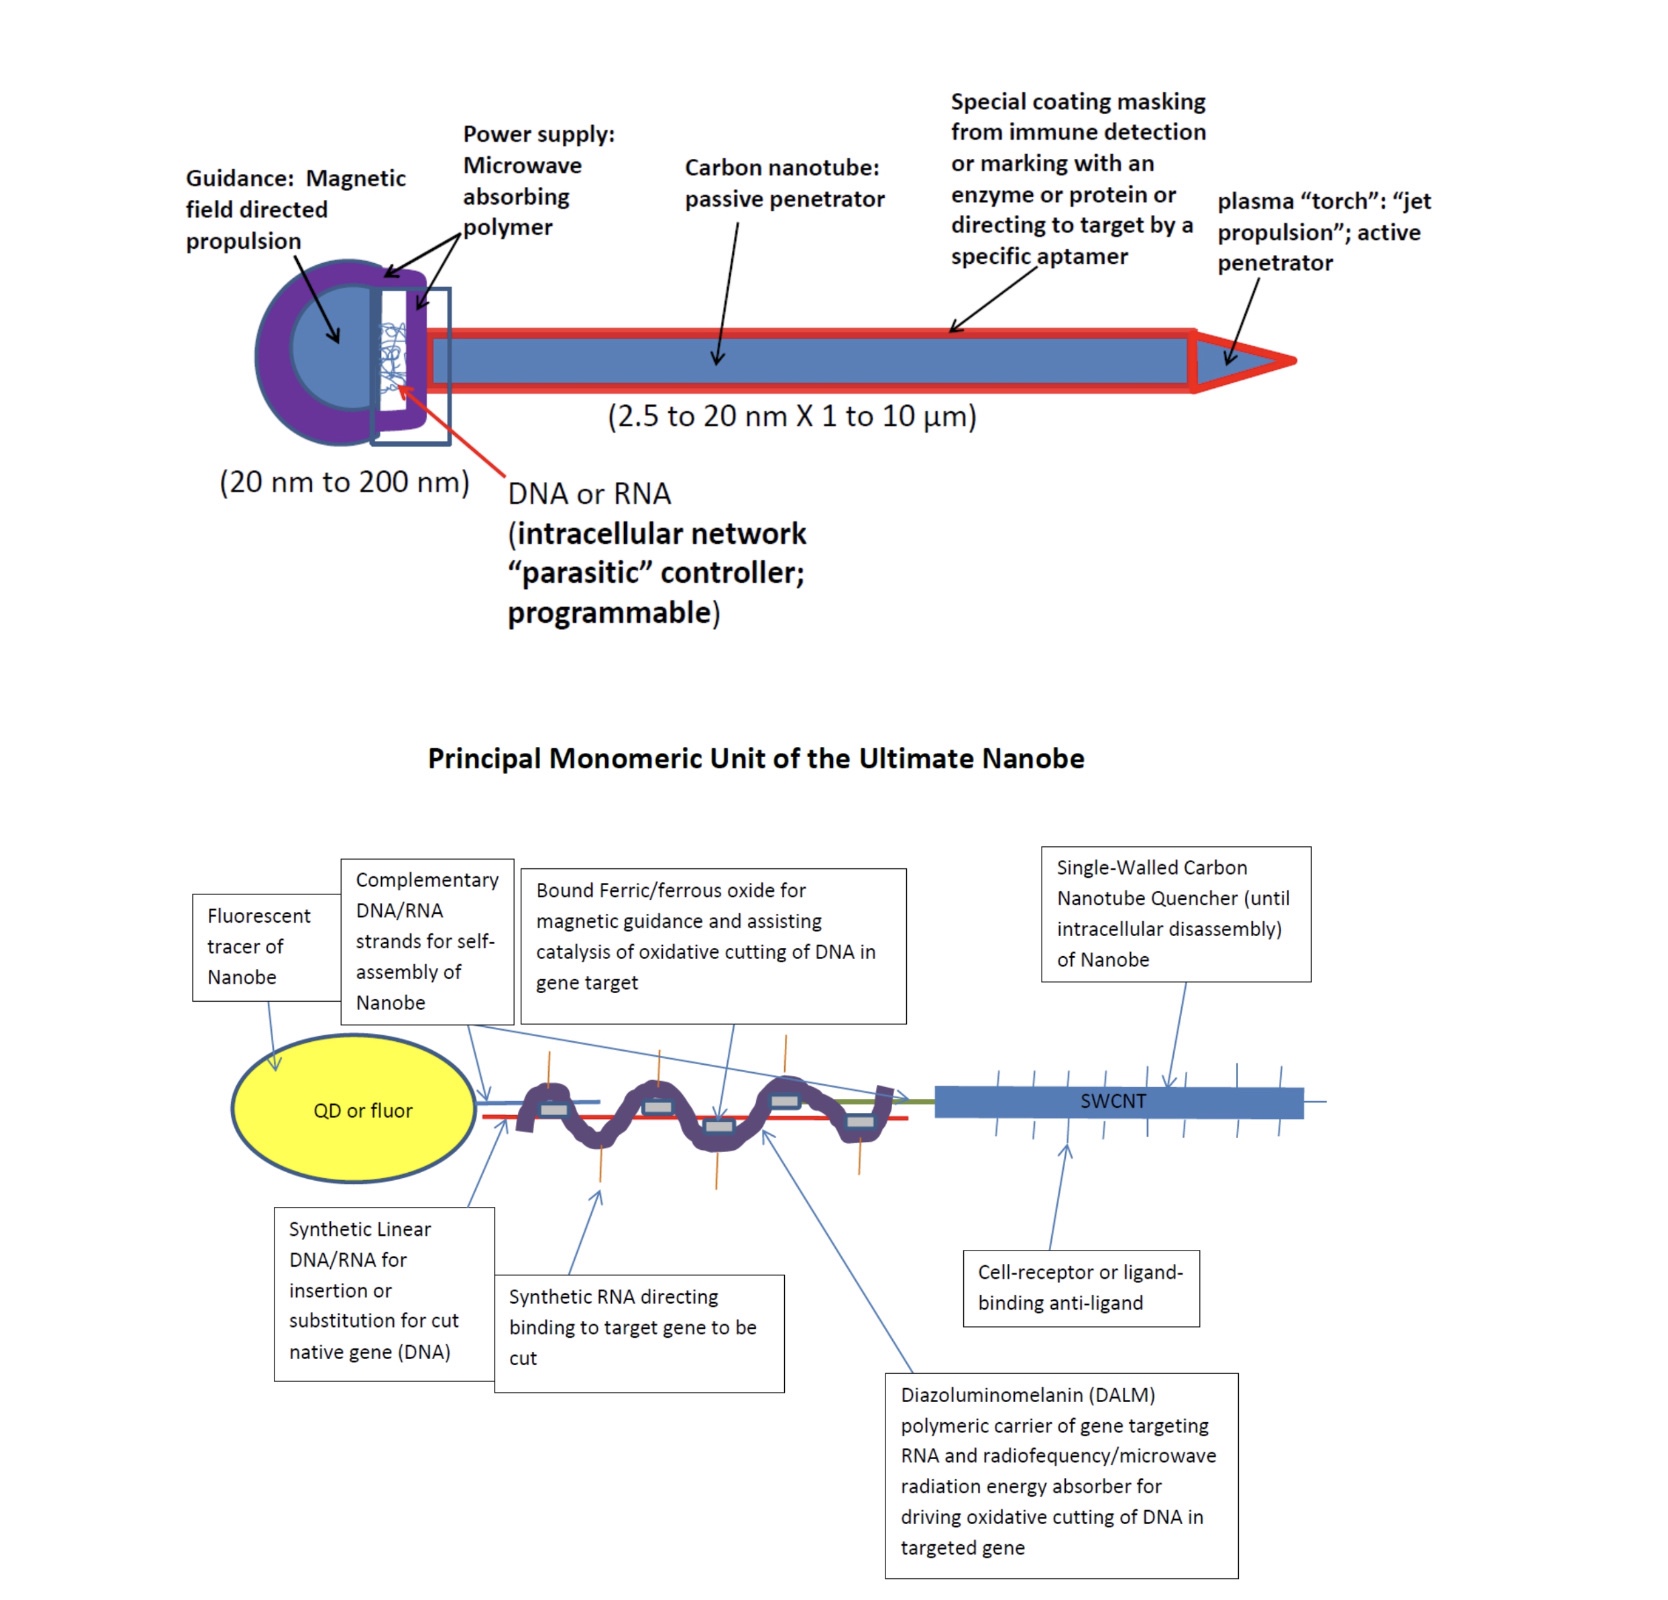
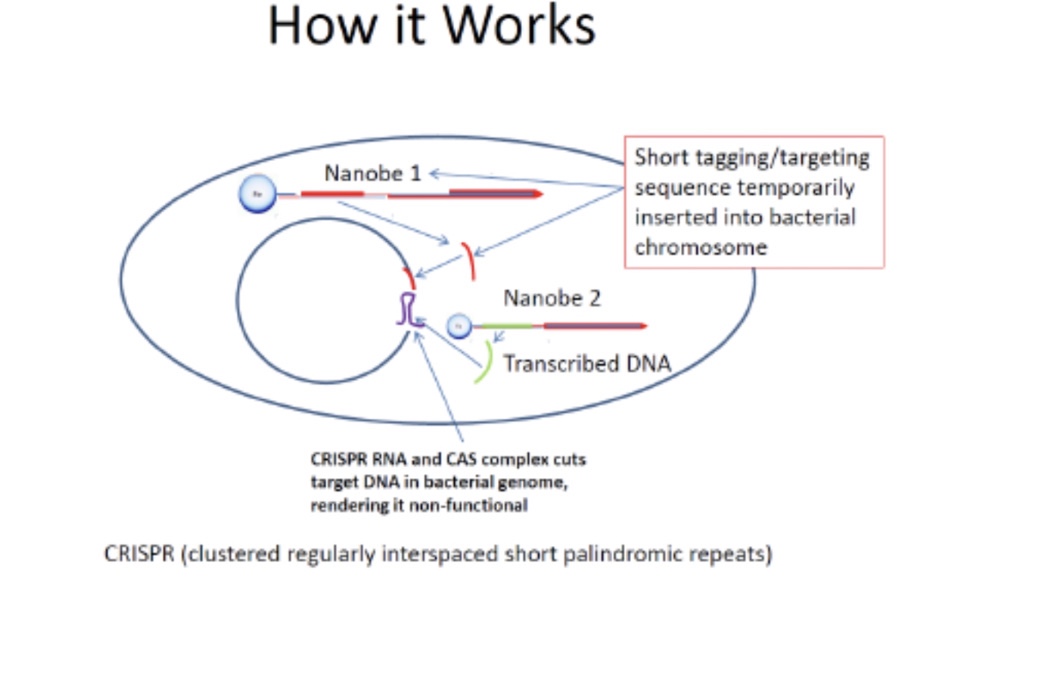
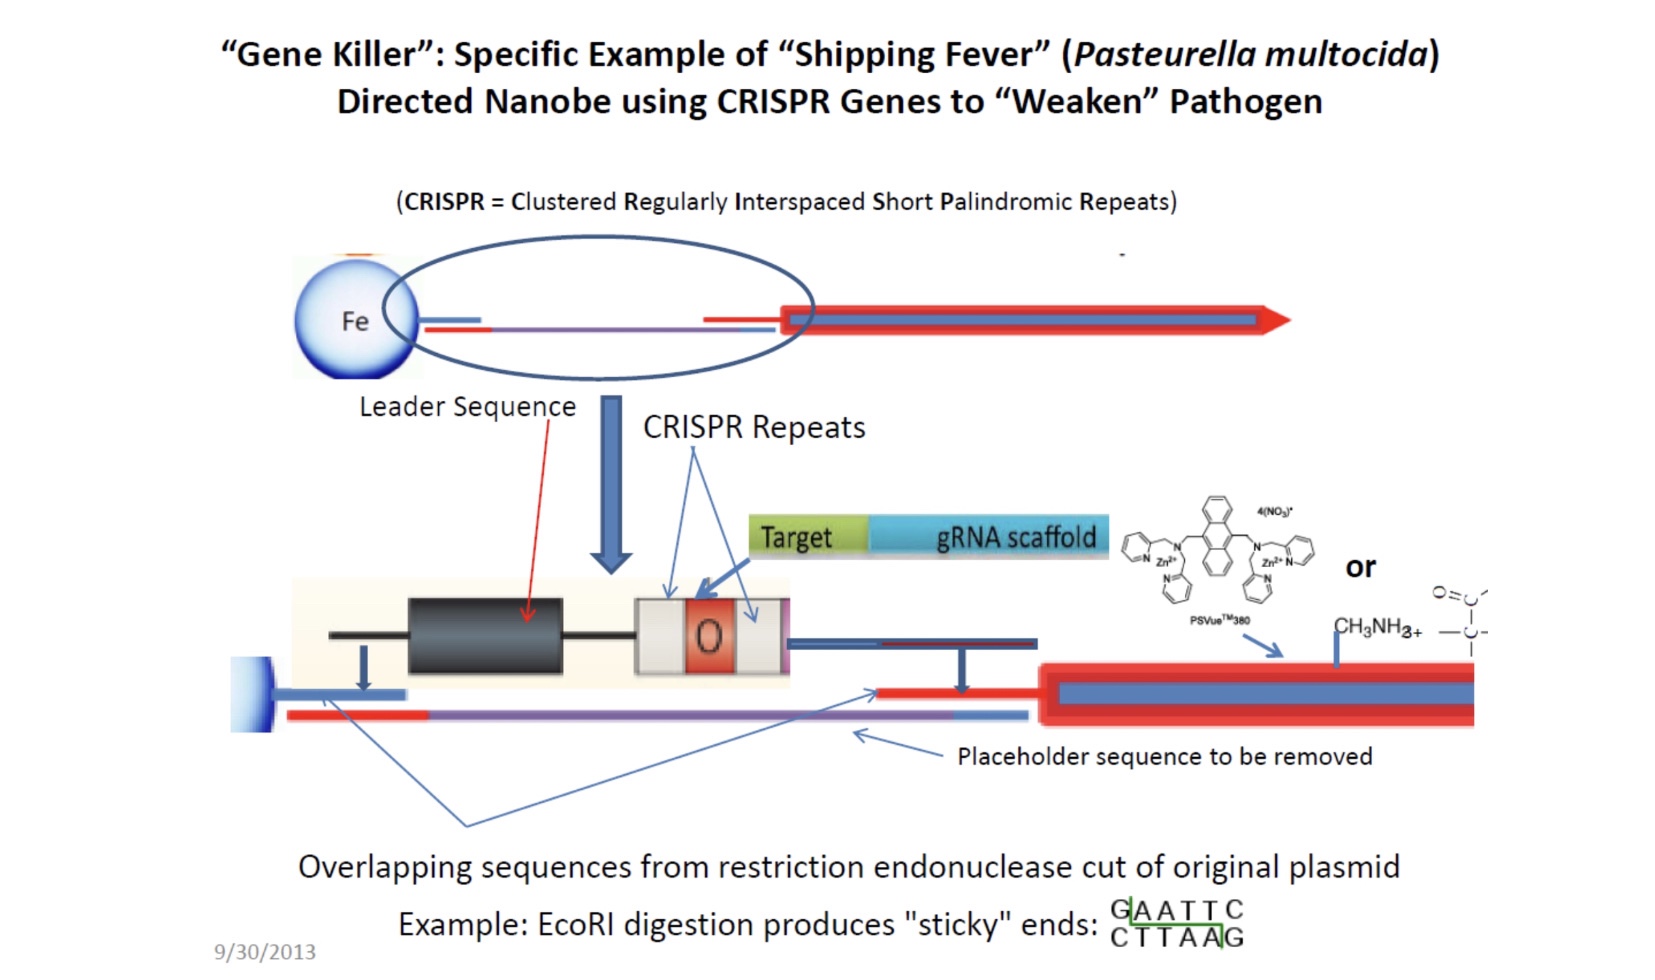
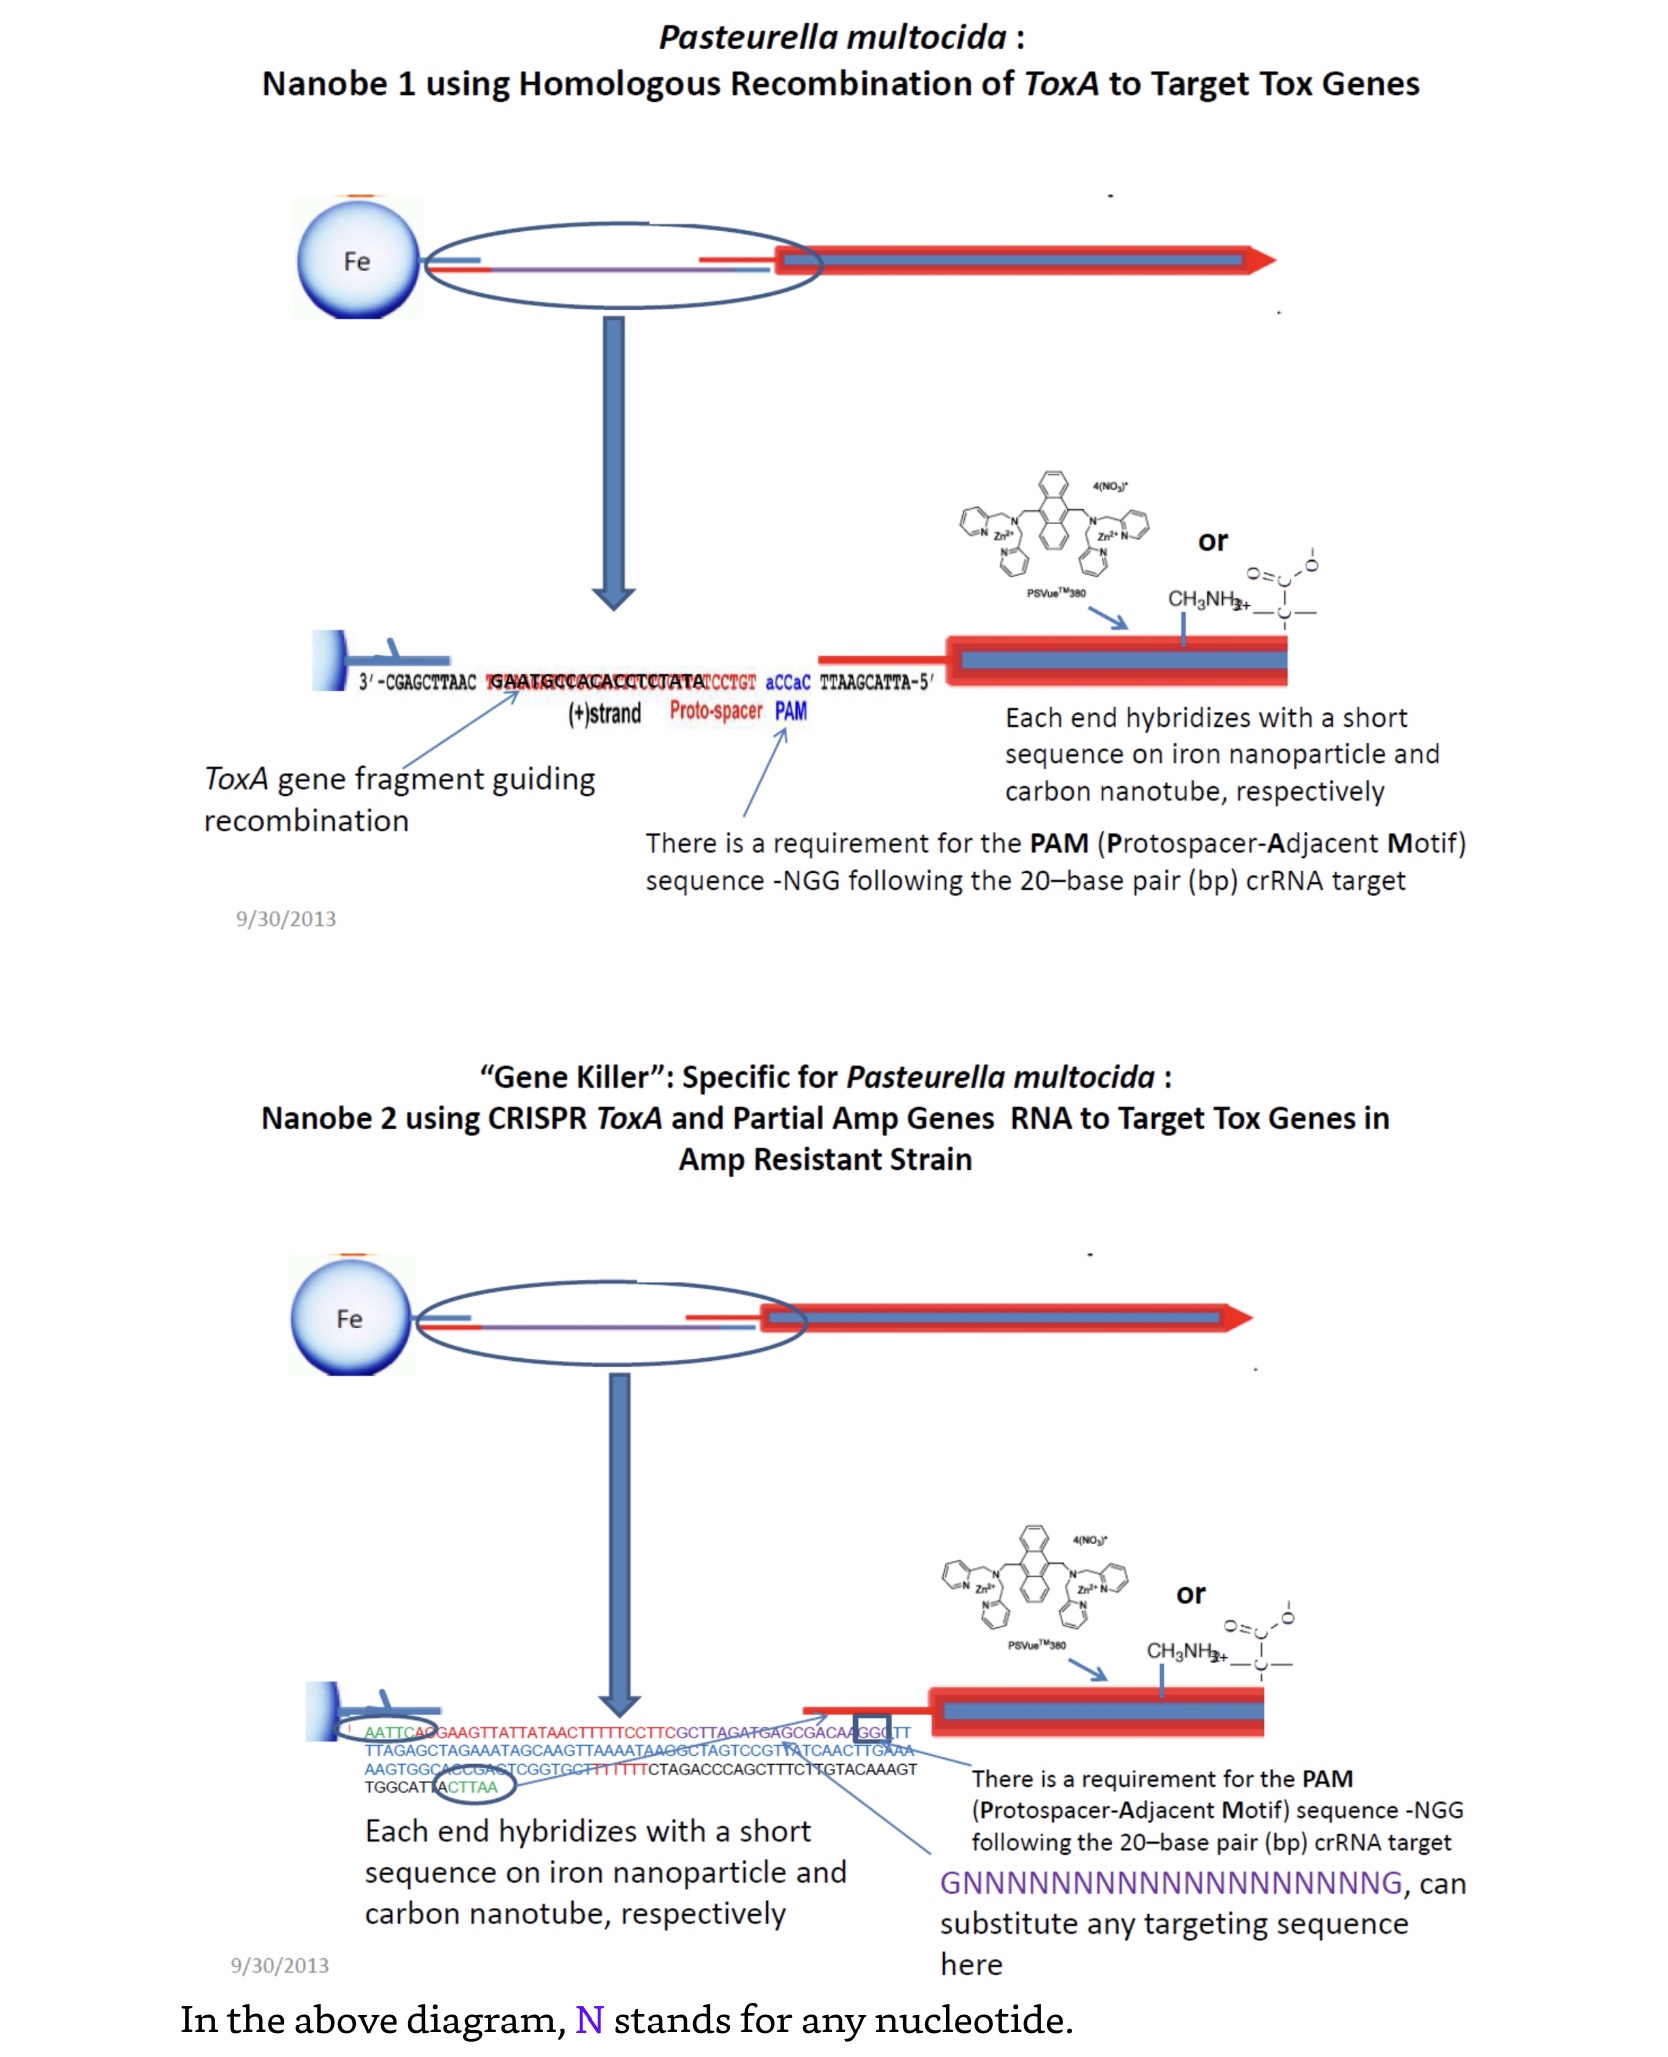
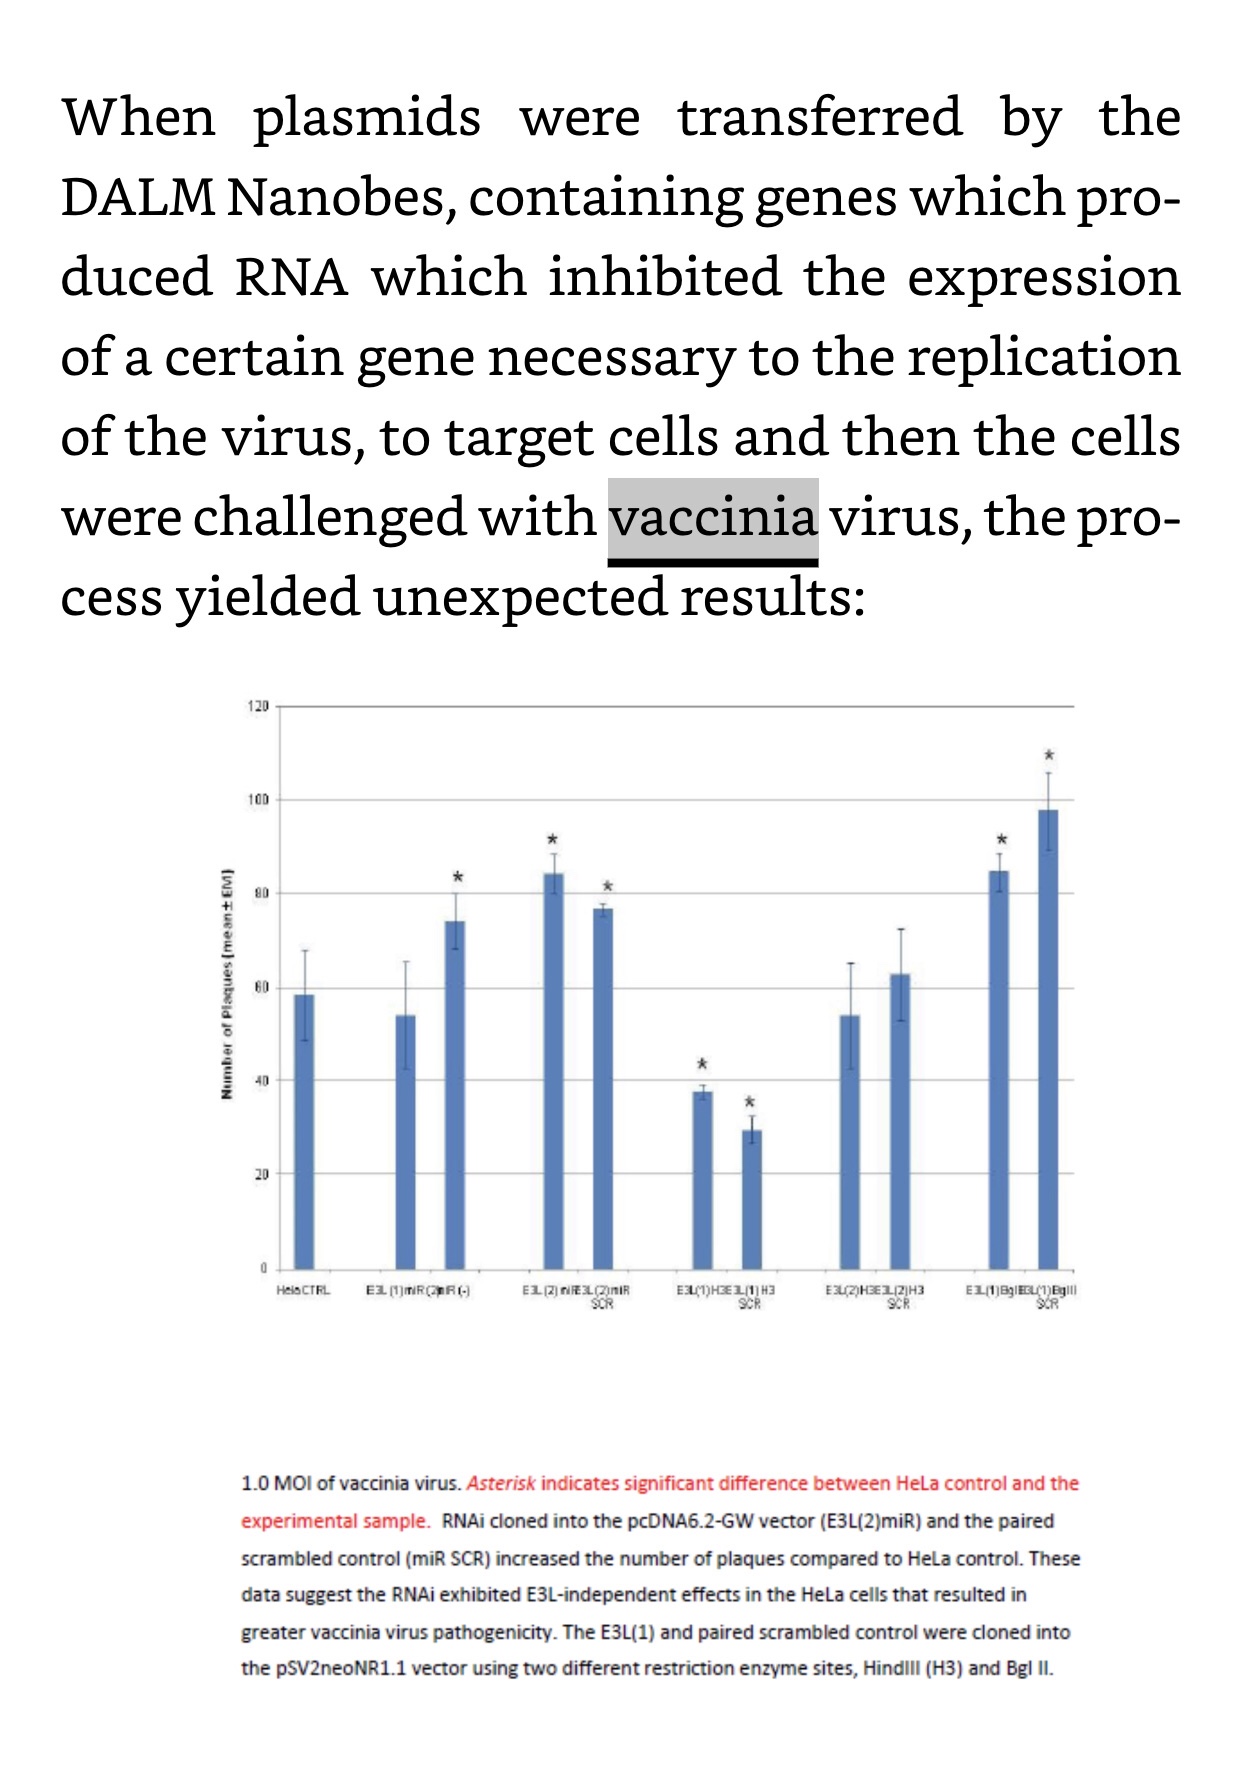
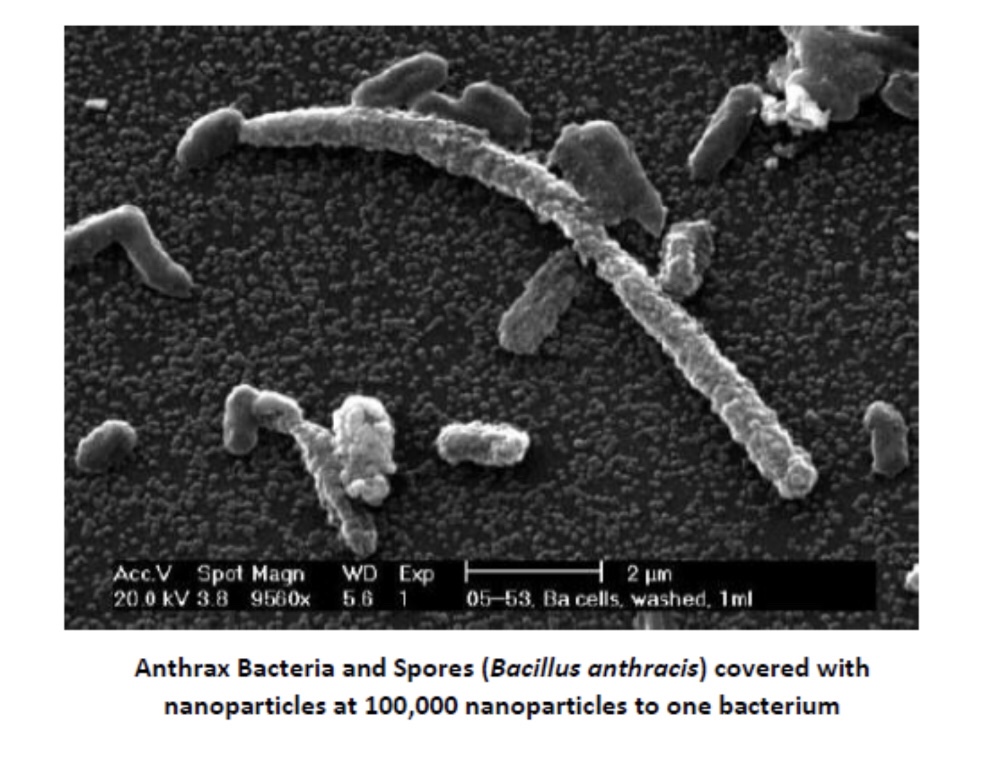
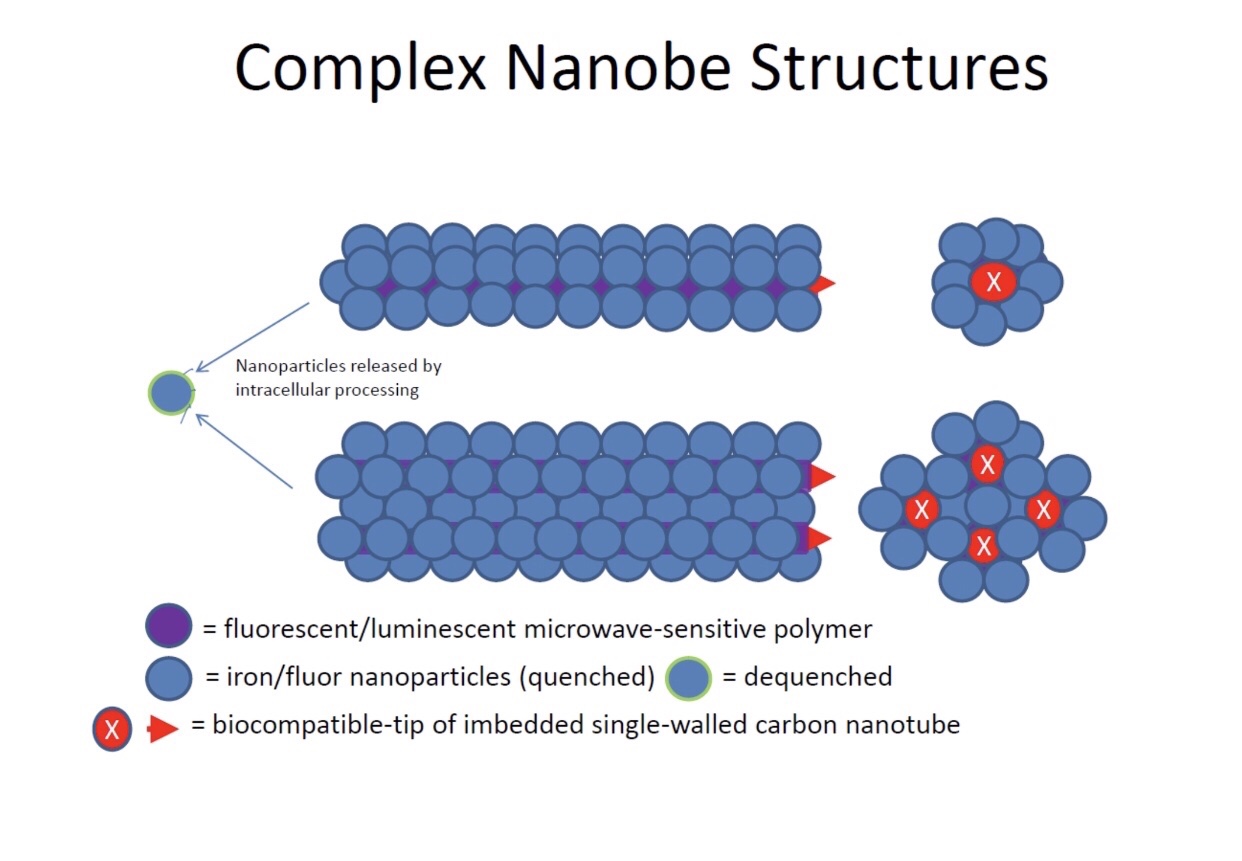
SELEX: Systematic Evolution of Ligands by Exponential Enrichment: The initial process by which single-stranded DNA (or RNA) aptamers were selected and amplified.Selection Express: A rapid method, to replace SELEX, which is compatible with automation and used to manufacture double-stranded DNA aptamers. Fan, M., McBurnett, S. R., Andrews, C. J., Allman, A. M., Bruno, J. G., and Kiel, J. L.. Aptamer Selection Express: A Novel Method for Rapid Single-Step Selection and Sensing of Aptamers. J Biomol Tech 19( 5), 311–319 (December 2008).Tracer tags with de-quenching fluorescent, single-walled carbon nanotube (SWCNT) and magnetic labels on aptamers; the latter facilitating collection and concentration of Especially Dangerous Pathogens. Nanosprayer for applying quenched fluorescently labeled aptamer nanoparticles as “detector and identifier paint” for pathogens on surfaces. De-quenched fluorescent aptamer nanoparticles on fly wings exposed to Bacillus thuringiensis non-pathogenic surrogate in environmental release experiments. Nano sprayers for application of cosmetics, made in China and available in the USAUSAF Air Force Research Laboratory Support of Nanobe Technology The NASA device with multi-channel modified magnetic capture and fluorescent detection chamber internal parts.Using attached Diazoluminomelanin (DALM) nanoribbins to absorb microwave radiation and generate very high electronic temperature nanoplasmas, bursting rapidly expanding anthrax spores. This destructive process also acts as an internal fail safe system to destroy Nanobes or the the cells genetically modified to produce them.Demonstrating the dynamics of kill by the DALM component of Nanobes Diagram of bacterial and eukaryotic cell biosynthesis and transfer of nucleic acid/DALM nanoparticles. Additional magnetic nanoparticles chelate with DALM nanoparticles to facilitate collection and concentration for purification and genetic transfer.DALM polymer spontaneously complexes with DNA or RNA to deliver functional nucleic acids to target cellsDetails of one of the genetic vectors for human and other mammalian cells carried by Nanobes for permanent genetic modification Nanobe patentPCR demonstration of actual transformation with DALM/DNA and/or iron (paramagnetic) nanoparticlesComposite diagram of genetic transfer and modification by synthetic (SWCNT) and biosynthetic (DALM) nanoparticles and re-directing a viral pathogen from a target host cell to an antigen presenting cell to make it into an autogenous vaccine.PCR of HK2 (human kidney cells) demonstrating both synthetic (s-D ) and biosynthetic (v-D) DALM nanoparticle gene transfer (transfection)Tracer and guided synthetic Nanobes and a non-protein, non-antigenic, polymer oxidative DNA cutting and gene replacement system, making the protein (CAS complex), which is antigenic, unnecessaryNanobe design for two-Nanobes delivery of CRISPR; the following illustrations show a specific design for removing the toxin gene from Pasteurella multocida bacteria resistant to ampicillin, which is a cause of Shipping Fever in cattle.Unfinished business: First step to develop anti-viral Nanobes; never completed because of the termination of the USAF AFRL Counterproliferation Team.
Recently, DARPA has sponsored an inhalable CRISPR nano construct which can attack viruses like influenza and SARS-CoV-2, at least in mice and hamsters. The researchers used mRNA coding for the protein Cas13a, which chops up parts of the viral genome required for replication. This treatment is delivered via polymer nanoparticles (https://www.nature.com/articles/s41587-021-00822-w). Before there was CRISPR plug and play by DARPA, there was the Nanobe inhalable plug and play by AFRL, “Chapter 54 Plug and Play..how a component-based design can be used in nanotechnology to produce a highly versatile new set of diagnostics to therapeutic tools and, for the first time, to make a material which is also practical for treatment.” The Black Dragon Trilogy, 2018.
Footnote: Perhaps why this was never developed and I have been excluded from developing it further: “By adding specific aptamer sequences to the surface of the Nanobes, they could be directed to bind to specific neurons with those surface markers to deliver “nano-level stimulation”. This application would meet the nefarious goal of behavior control of specific adversaries by external application of electromagnetic fields which would not affect anyone else exposed. However, this approach could also provide relief for those suffering from various neurological or mental disease and brain injuries, including counter acting addiction, the dual use dilemma.” “Chapter 50 Why is Nanowarfare at War and Not Peace? This chapter discusses the duplicity of bionanotechnology, the “political science” and economics behind the funding of this research and its dual use applications revealed in the open literature and by government policy.”“A high-ranking colleague in the Department of Defense at the Pentagon once called me the Most Dangerous Man Alive. But now, as of this writing, I am the most helpless as a scientist and technologist. The only resource I have left is knowledge. Now I have shared it with you. I only hope you have the wisdom to use it appropriately.”—-The Black Dragon Trilogy by JOHNATHAN KIEL https://a.co/hhbwuTE
Spherical Nanobes which can penetrate bacterial and human and animal cells for diagnostic, therapeutic and genetic modification purposes
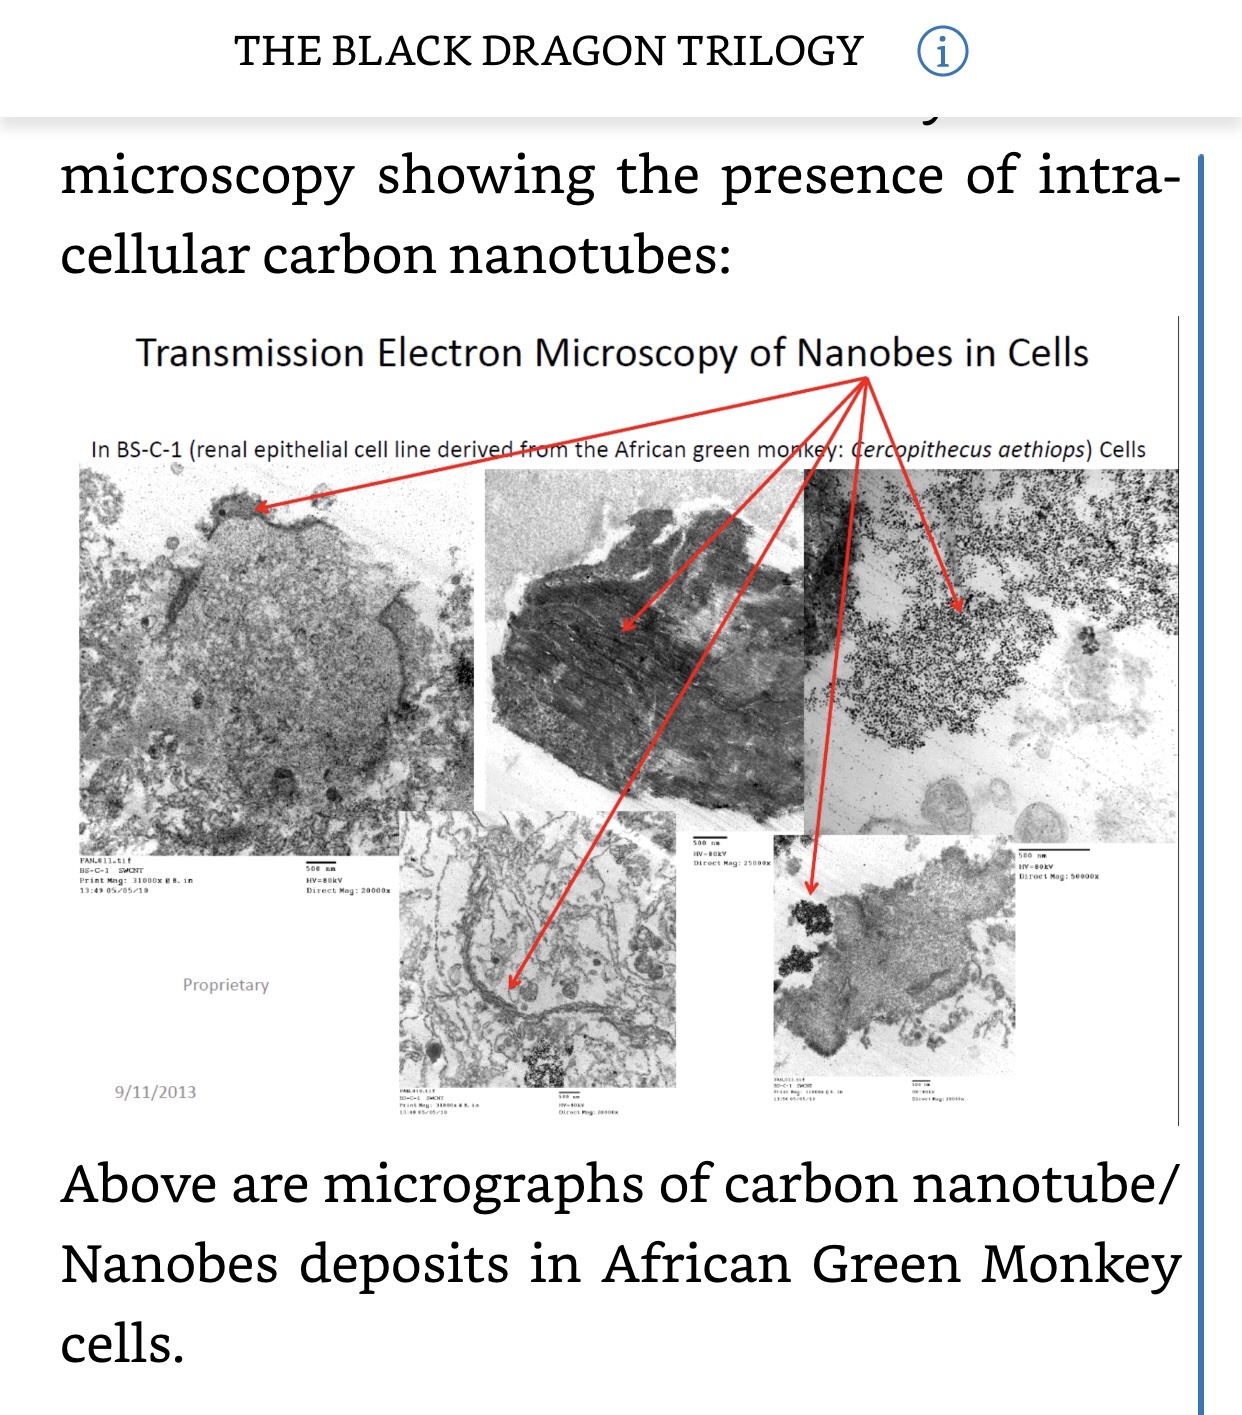
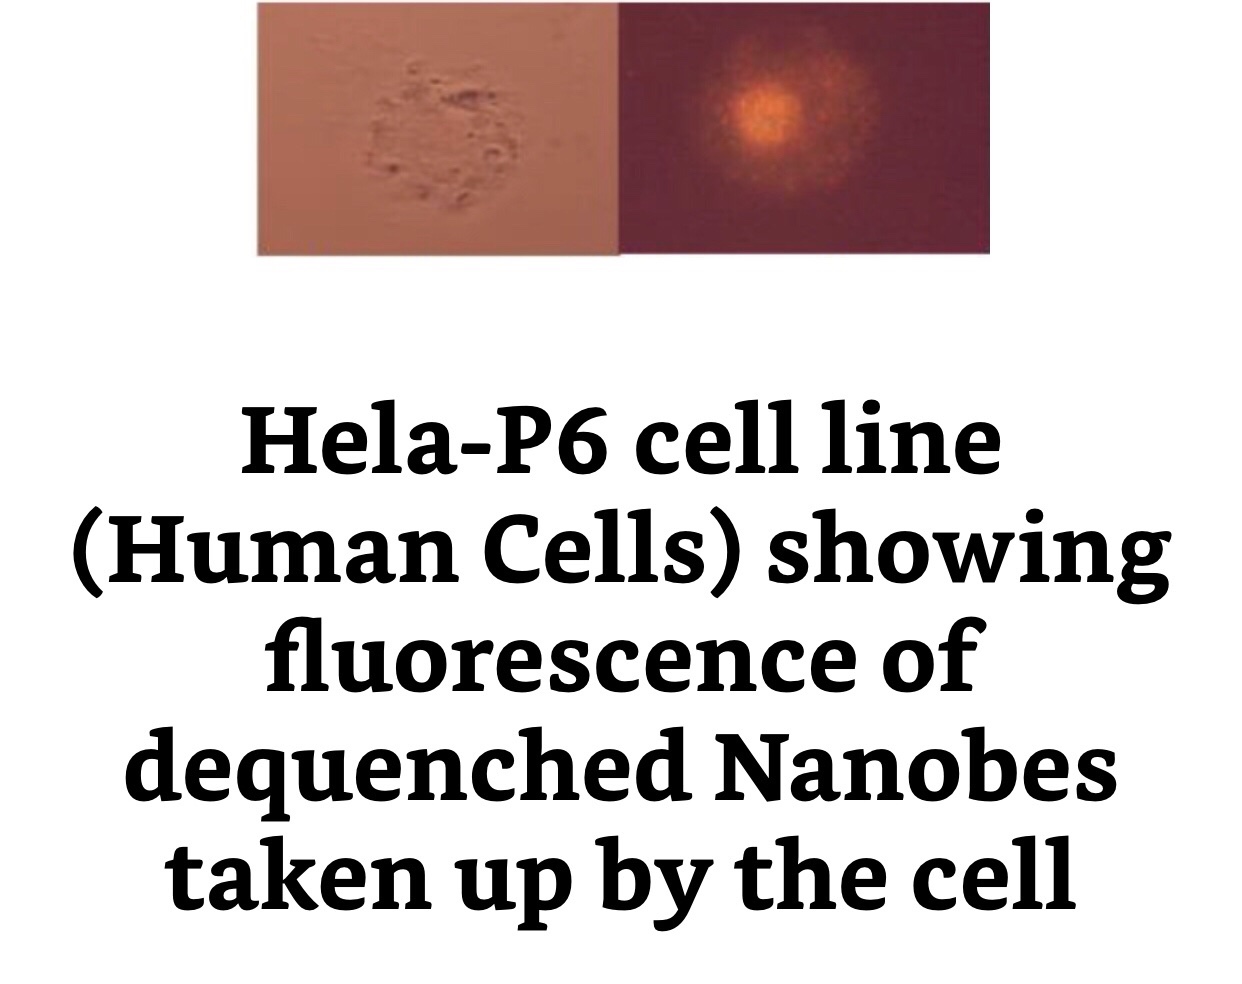
Above is a notional ensemble of spherical Nanobes associated with carbon nanotubes followed by pictures of cells penetrated with these actual structures and traced with fluorescence into the nucleus of a human cell in the last photograph.
This last addition is a warning to always be aware of untoward effects of nano biotechnology and be prepared to counter them without abandoning the benefits of such technology
With the rise of many mutations and variants, the questions arise: 1) will the current vaccines protect and stem the tide of the pandemic? 2) Will the vaccines drive, by selection pressure, the establishment of new more resistant, transmissible and/or pathogenic variants? 3) Will masks and social distancing still be required after vaccination? Variants which emerged in Brazil (known as P.1.), Britain (known as 20I/501Y.V1 or B.1.1.7) and South Africa (known as 20I/501Y.V2 or B.1.351) are now the globally dominant strains because of their apparently enhanced infectivity and transmissibility.
Current vaccines work against the UK B.1.1.7 variant without the E484K mutation. However, recent clinical trials by Novavax and Johnson & Johnson showed that their new vaccines were less effective in South Africa compared with the UK or US, probably because of the high level of virus carrying the E484K mutation. However, Novavax vaccine was reported to have a 60% efficacy in South Africa which is a good response, when compared to influenza vaccine responses of from 40-60 %. Studies have shown that people who have been infected with SARS-CoV-2 generate T cells that target at least 15–20 different fragments of coronavirus proteins. Because of natural variability, a population will generate a large variety of T cells that could attack the virus (https://reader.elsevier.com/reader/sd/pii/S1074761320305379?token=3775A68CFC8B8609E4A6753EF03F560FAF6F4B30D3B821B81F3A1CBF077E6DB8C53232C5B16ACCA1E569F0AE6C5368F3). As I mentioned in an earlier post, it is very hard for the CoVID variant viruses to mutate to escape cell recognition because of this T cell variation, The specificity of antibodies works in favor of variants. A recent pre-print shows a single mutation can defeat monoclonal antibodies against the spike protein of the virus and increased cell receptor binding, unfortunately a rare converging of properties in a single mutation. The mutation has been observed in a recent variant in California, CAL.20C viral variant from clade 20C, lineage B.1.429, that since November 2020 has generated multiple outbreaks and is undergoing massive expansion in California. This L452R mutation allows SARS-CoV-2 positive selection toward strong viral adaptation against containment measures that work on less contagious variants and against increasing population immunity against previous forms. The L452R mutation is at the leucine-452 position in the receptor-binding area of RBD (receptor binding domain) at the interface with the ACE2 receptor. Replacing it with arginine is anticipated to result in both a much stronger receptor binding and escape from neutralizing antibodies https://www.biorxiv.org/content/10.1101/2021.02.22.432189v1.full.pdf. Escape from two monoclonal antibodies has been predicted in a recent Science article https://science.sciencemag.org/content/sci/371/6531/850.full.pdf.
In a preprint published on 9 February, researchers found most T-cell responses to coronavirus vaccination or previous infection do not target regions mutated in two recently discovered variants, including 501Y.V2 (https://www.researchsquare.com/article/rs-226857/v1). Also, the vaccine made by Novavax of Gaithersburg, Maryland, a single-shot vaccine made by Johnson & Johnson of New Brunswick, New Jersey, and a vaccine made by AstraZeneca of Cambridge, UK, and the University of Oxford, UK are less effective at protecting against mild COVID-19 in South Africa, where the 501Y.V2 variant dominates, than in countries where it is now less common. AstraZeneca’s vaccine was only 22% effective against mild COVID-19 in a study of 2,000 people in South Africa, but the trial was too small and participants too young to draw any conclusions about any loss of benefit in protecting against severe disease. However, another recent paper compared the vaccine – induced neutralization of a less contagious version of the SARS-CoV-2 virus from last year (USA-WA1/2020), to the new variants Brazilian P1 and UK variant B.1.1.7 which gave results “roughly equivalent.” Geometric mean titers (GMT) of neutralizing antibodies against the USA-WA1/2020 virus, the UK B.1.1.7 variant, and the P1 variant were 532, 633, and 437, respectively. The GMT against three versions of the South African B.1.3.5 variant were less at 195, 485, and 331, respectively (https://www.medscape.com/viewarticle/947064).
A recent, yet to be peer-reviewed, study of men from 70-84 years of age, who died from COVID-19, increased from 5% of those who tested positive for the older variant, to more than 6%, if confirmed positive for variant B.1.1.7. For men 85 years or older, the risk of dying increased from 17% to 22% of those confirmed positive for the new variant. Therefore, the apparent increase in severity of this new variant has been limited in scope. It may reflect an increased viral load rather than a normalized increase in pathogenicity. There is little evolutionary advantage for a virus to become more pathogenic in a host in preference to transmissibility. This may happen only if there is a maintenance reservoir host in which the pathogenicity is less and from which the virus periodically emerges entering the host more vulnerable to lethality.
As to the third question, until the pandemic has subsided, even vaccinated people, including those who may have gotten upgraded vaccine for new variants, should continue to use masks, social distance, and, of course, continue to use good hand washing practices. Another early treatment to block viral replication has been discovered; a single pill of the investigational drug molnupiravir, when taken twice a day for 5 days, has been shown to eliminate SARS-CoV-2 from the nasopharynx of 49 participants in a new study (https://www.medscape.com/viewarticle/947061). Phase 2/3 efficacy and safety studies of the drug have started. The drug creates viral error catastrophe by inducing replication and mutations until the virus can’t effectively produce viable copies. This new early treatment and the non-pharmaceutical practices are necessary to decrease the total number of viruses in circulation, to greatly decrease the probability of establishing new variants even if they are more transmissible, and especially if those infected shed larger amounts of virus asymptomatically or symptomatically.
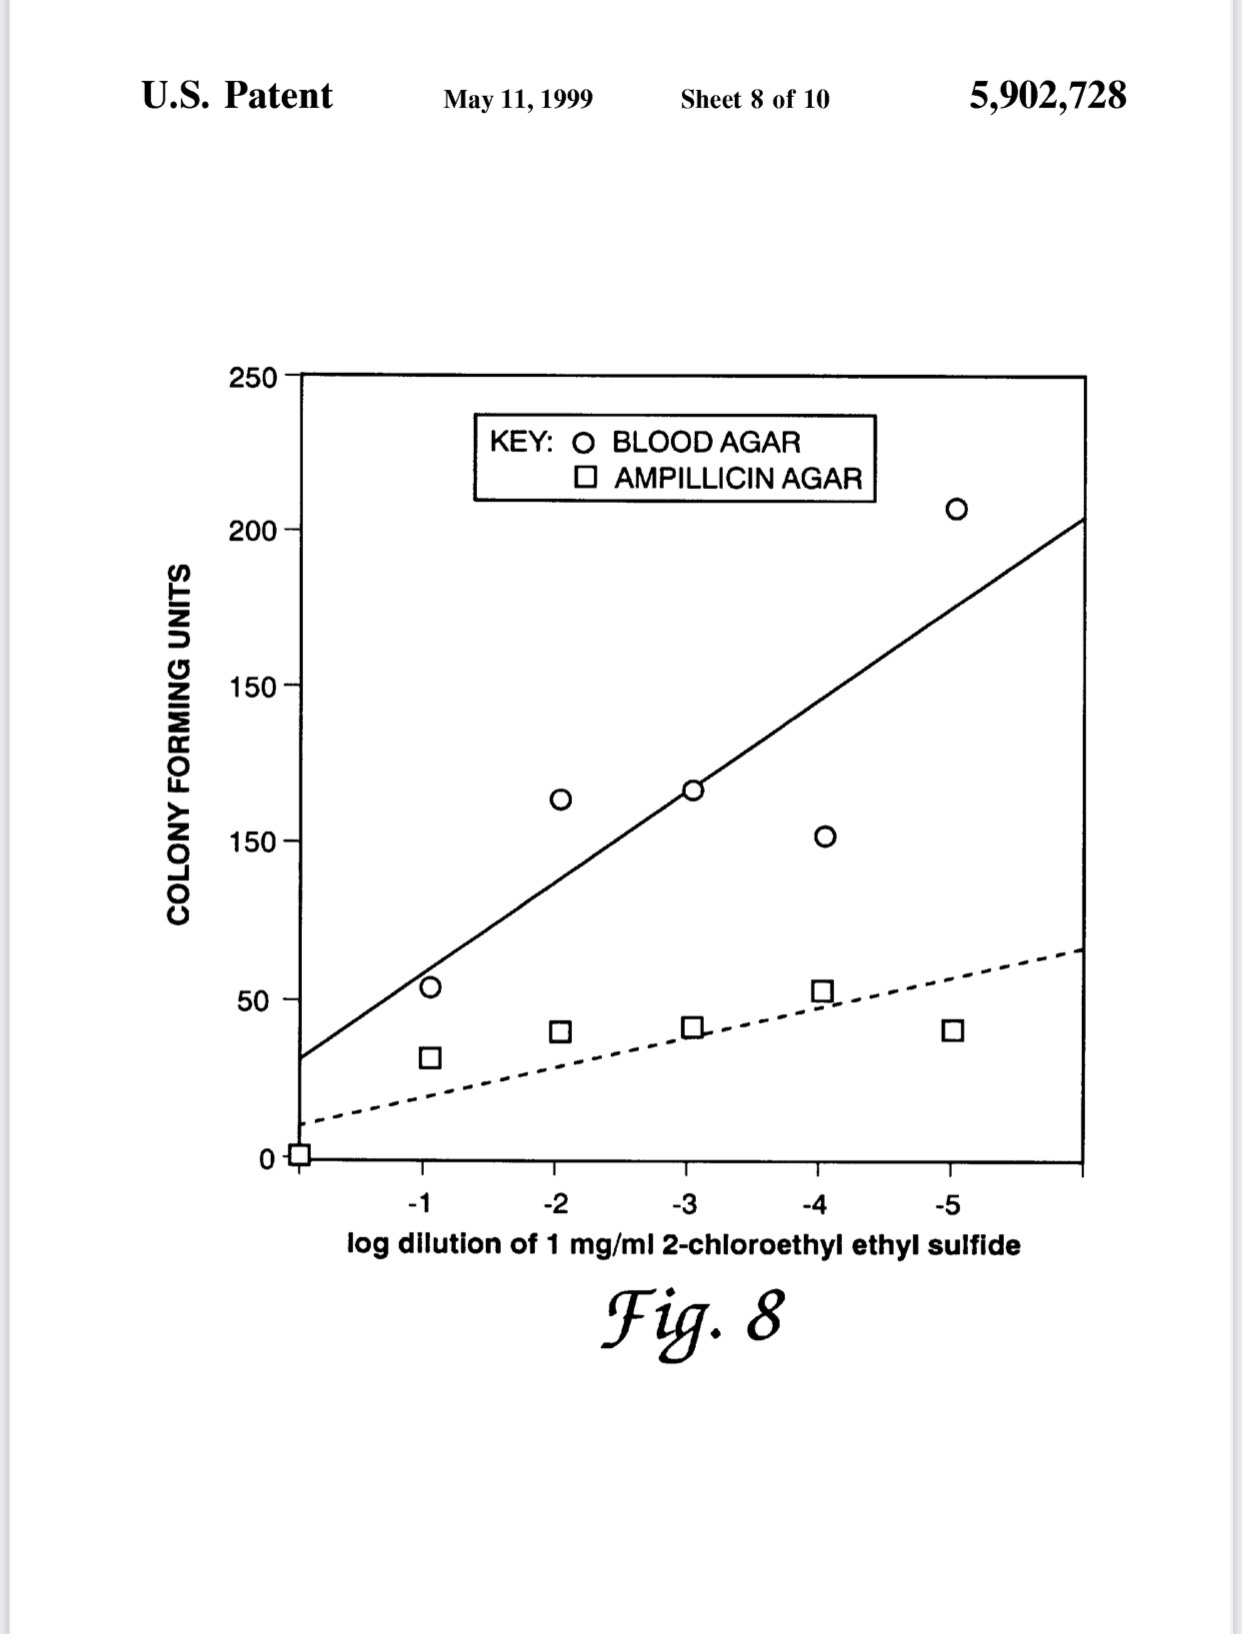
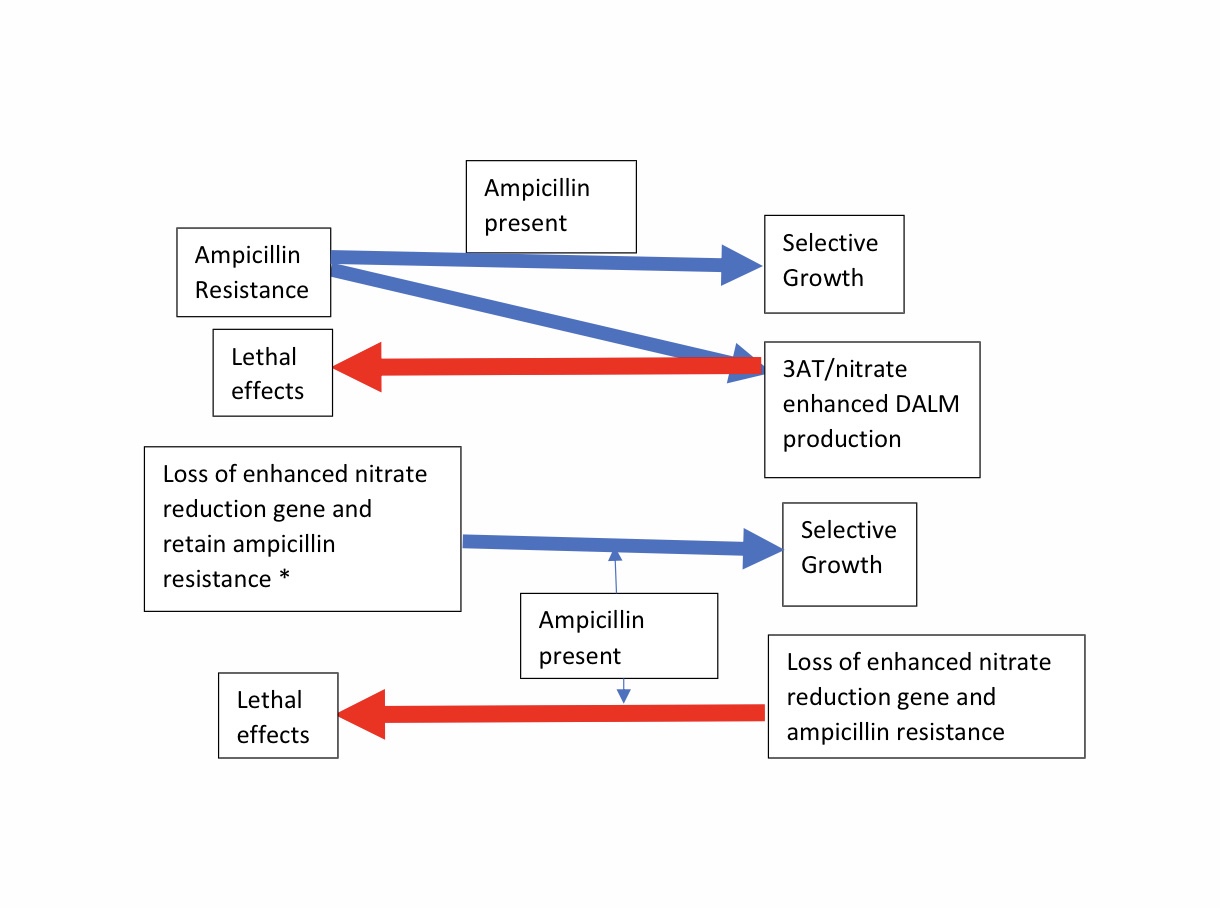
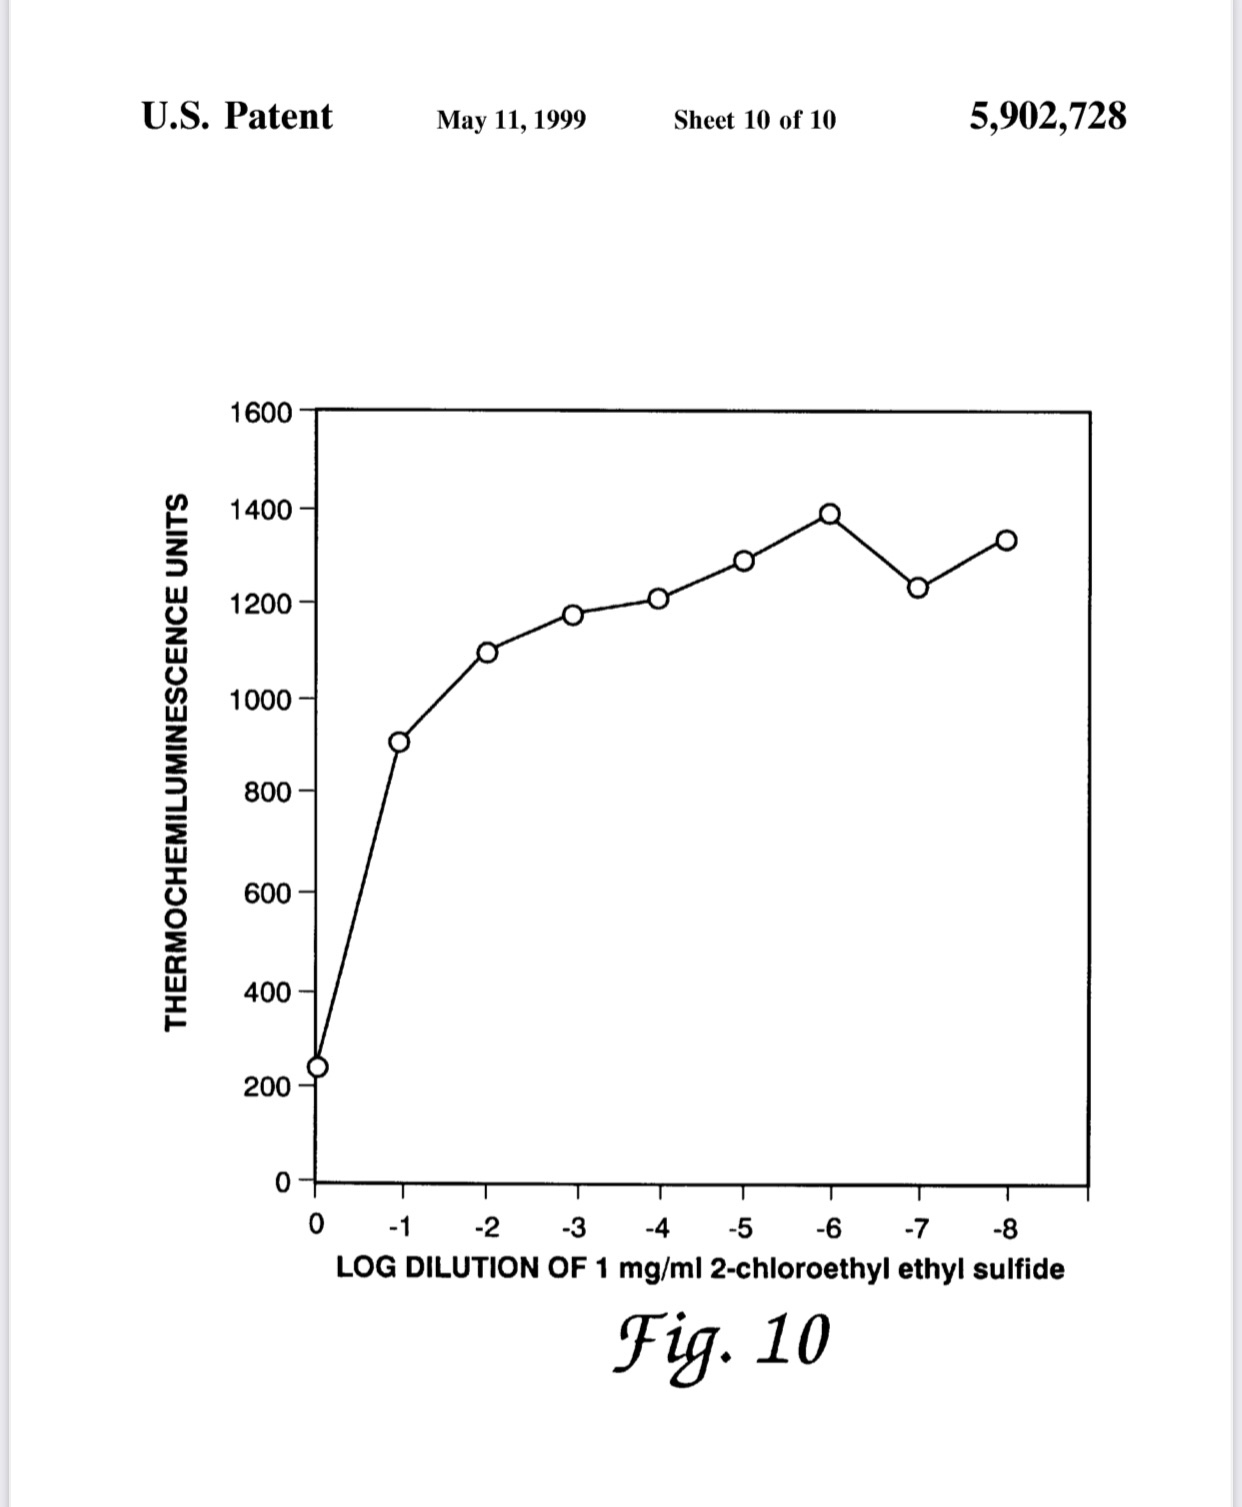
As stated in an earlier post, it is much more difficult to mutate past many different antiviral antibodies or different simultaneous multiple drug therapies. For example, in 1995, a combination drug treatment known as the “AIDS cocktail” was introduced which made AIDS a survivable, chronic disease. This type of therapy is known as highly active antiretroviral therapy (HAART), also called combination antiretroviral therapy (cART). HIV is a virus much more prone to mutations than SARS-CoV-2. Our own research, demonstrated that a mutagen (2-chloroethylethylsulfide) could make bacteria resistant to one but not two antibiotics at the same time in the same microbes without substantial mutations that largely proved lethal for the bacteria (ampicillin and 3-amino-L-tyrosine: Patent #: 5,902,728; date: May11,1999). As the number of mutations increased in the microbial population in order to achieve both ampicillin resistance and 3-amino-L-tyrosine/nitrate resistance, the bacteria became less robust and sacrificed their competitiveness to less resistant subpopulations. The JM109/pIC20RNR1.1 E. coli, genetically modified bacteria by a plasmid, was designed to have conflicting selection pressures when grown in 3-AT medium containing both ampicillin and 3-amino-L-tyrosine/nitrate. The biosynthesis of the DALM polymer was driven by the ampicillin resistance expressed from the same plasmid which contained the gene for enhanced DALM biosynthesis. However, driving DALM synthesis led to lethality. Loss of the ampicillin resistance would spare the bacteria from DALM lethality, but lead to their death by the ampicillin. Therefore, there needed to be a set of simultaneous mutations to spare the bacteria from both these diametrically opposed lethal effects. A similar response would prevent SARS-CoV-2 from escape mutations if hit by several different antiviral approaches simultaneously. The number of mutations in SARS-CoV-2 increase by chance as the circulating population of viruses increases and they become available for natural selection for traits that increase their survivability and transmission. Conversely, limiting their spread and numbers by both pharmaceutical (vaccines and antivirals) and non-pharmaceutical means (masks and distancing) greatly reduce these possibilities. Finally, I illustrate below how the appearance of variants, which evade vaccines and treatments, can be countered by aptamer adapters that restore the effectiveness of these vaccines and treatments.
JM109/pIC20RNR1.1 E. coli inoculated at a billion organisms following growth for 24 hours in 3-AT broth containing the various 10-fold dilutions of the mutagen 2-chloroethylethyl sulfide then transferred to ampicillin LB agar or sheep blood agar for colony counts after 24 hours of growth. The higher to lower mutagen concentrations from left to right show a negative linear correlation with colony counts. The general survivability on blood agar was more sensitive to the mutagen than was the specific antibiotic resistance amongst the survivors, although a substantial number of survivors lost ampicillin resistance. The DALM formation in the 3-AT broth killed off many of those bacteria still maintaining the plasmid with ampicillin resistance. The overall mutation rate increased with increasing mutagen concentration from right to left on the x axis.Separating sensitivity to 3-AT (and nitrate) and resistance to ampicillin by increasing mutations, when they are genetically linked on the same plasmid, seems counterintuitive: At the lower concentrations of mutagen (log -6 to log -8), the survival on blood and ampicillin correlate and show the same trend of response for the spontaneous natural mutation at the lower concentrations; growth in 3-AT medium is lethal because of DALM polymer formation and the ampicillin resistance on the plasmid that enhances that production selects for its expression. To escape this lethal effect while maintaining ampicillin resistance requires very selective mutations. The more mutations the less fit is the surviving bacteria until they become uniformly lethal. This effect is demonstrated in the first rise in survival on blood agar but not on ampicillin agar (loss of ampicillin resistance first). The latter lags but costs in overall fitness as the mutations increase to select for ampicillin resistance separated from 3-AT sensitivity until the mutations increase to lethal. Therefore, it is very difficult to achieve mutations that select for survival of two eliminating treatments, especially if they are genetically and expression linked.Simple diagram of paradoxical selection pressure of Ampicillin/nitrate/3-amino-L-tyrosine growth medium on JM109/pIC20RNR1.1 E. coliThe decline in thermochemilumescence of bacteria grown in 3-AT medium with increasing mutagen concentrations, as an indirect measure of DALM polymer production. This correlation with increased survivability is not as great as expected, but this is probably because polymer production requires many genes as opposed to ampicillin resistance which requires just one. Complete inactivation of the polymer production requires accumulation of too many mutations, leading to death.
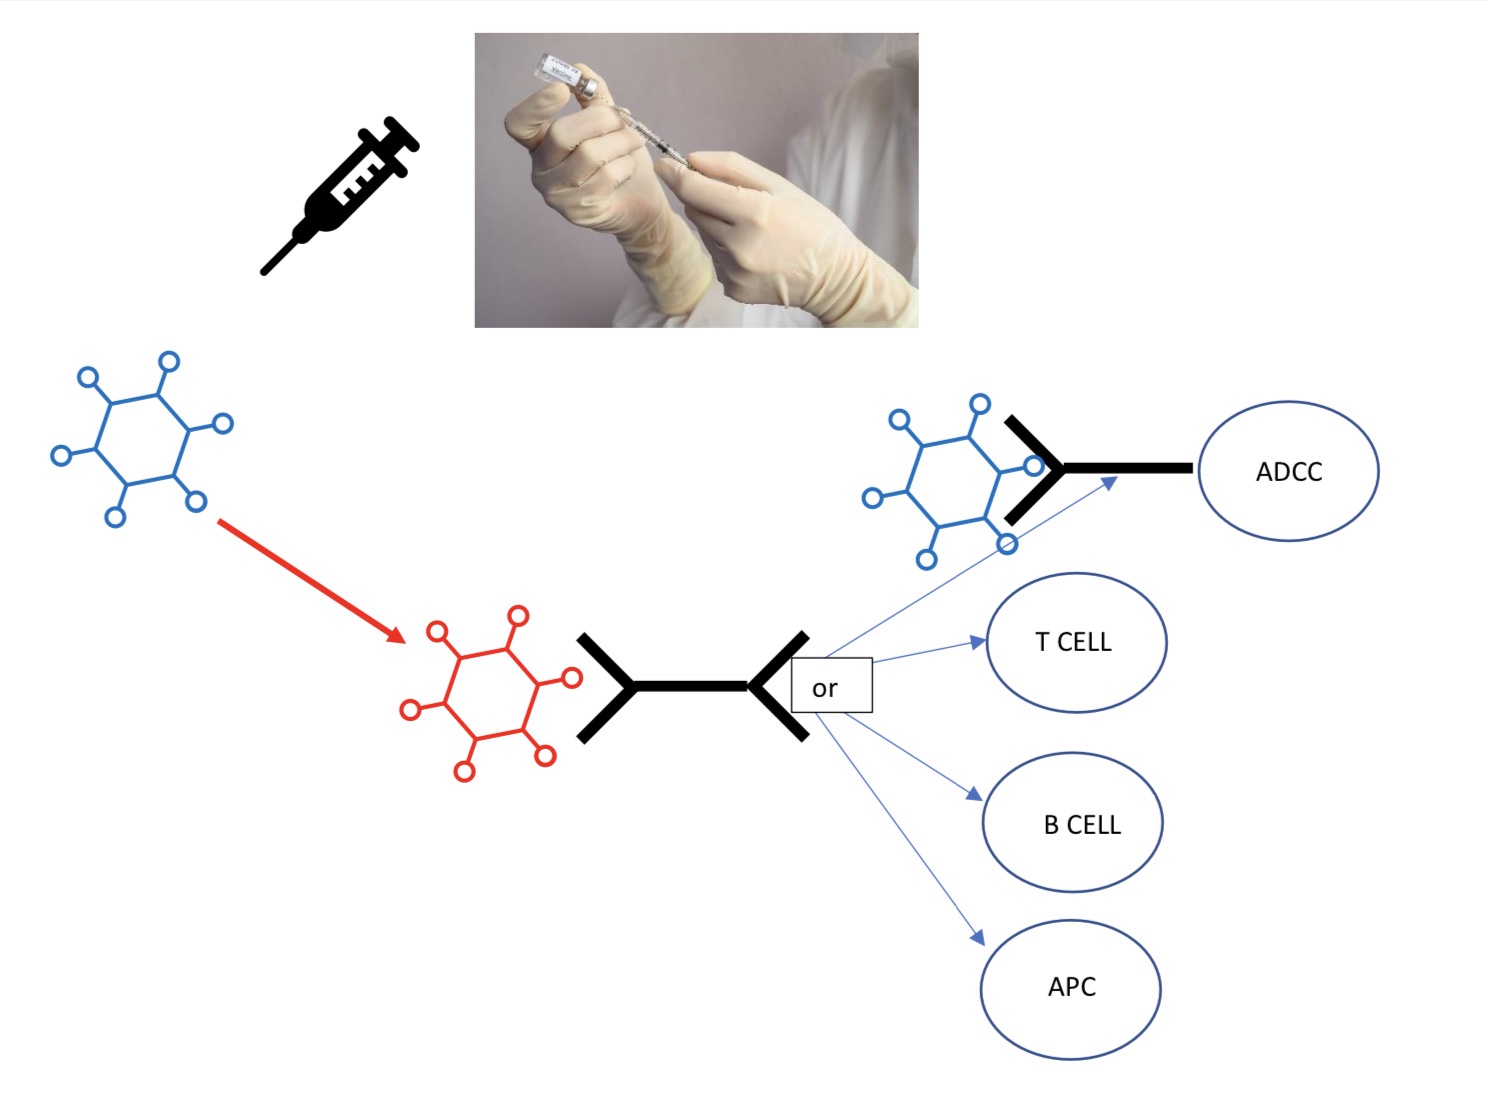
Re-Directing an old vaccine against a new variant of a virus. The blue virus was vaccinated against, then the circulating virus mutated into the red virus which is not protected against by the previous vaccine. The red virus is isolated, then nucleic acid aptamers are selected in vitro against the new virus. Another set of aptamers are selected against ligands on existing antibody against the original blue virus, or against ligands on cells in the immune system to recruit them to attack the virus (NK=Natural Killer cells, cytotoxic T cells, helper T cells and associated B cells). These aptamer sequences can be fused together to provide an adapter (>~~<) which links the binding of the variant virus to mediator (APC, Antigen Presenting Cells; dendrocytes) and effector cells in the immune system. The linkage to pre-existing antibody to the predecessor virus (>~~) allows neutralization of the variant virus and recruitment of Antibody Dependent Cell Cytotoxicity (ADCC; macrophages and granulocytes). The artificial evolution of aptamers, to go into such adapters, against new viral variants will prevent a vaccine from ever becoming obsolete. Double-faced artificial polypeptides, like aptamers, have been computationally designed to re-direct humoral vaccine immunity from existing antibodies against other virus targets to SARS-CoV-2 by having one end of the polypeptide mimicking ACE2 viral receptor and the other a Hepatitis B antigen to bind the previous Hepatitis B vaccine induced antibody to the SARS-CoV-2 virus through the ACE2 viral receptor mimic (https://pubs.acs.org/doi/pdf/10.1021/acs.jpclett.0c03615).
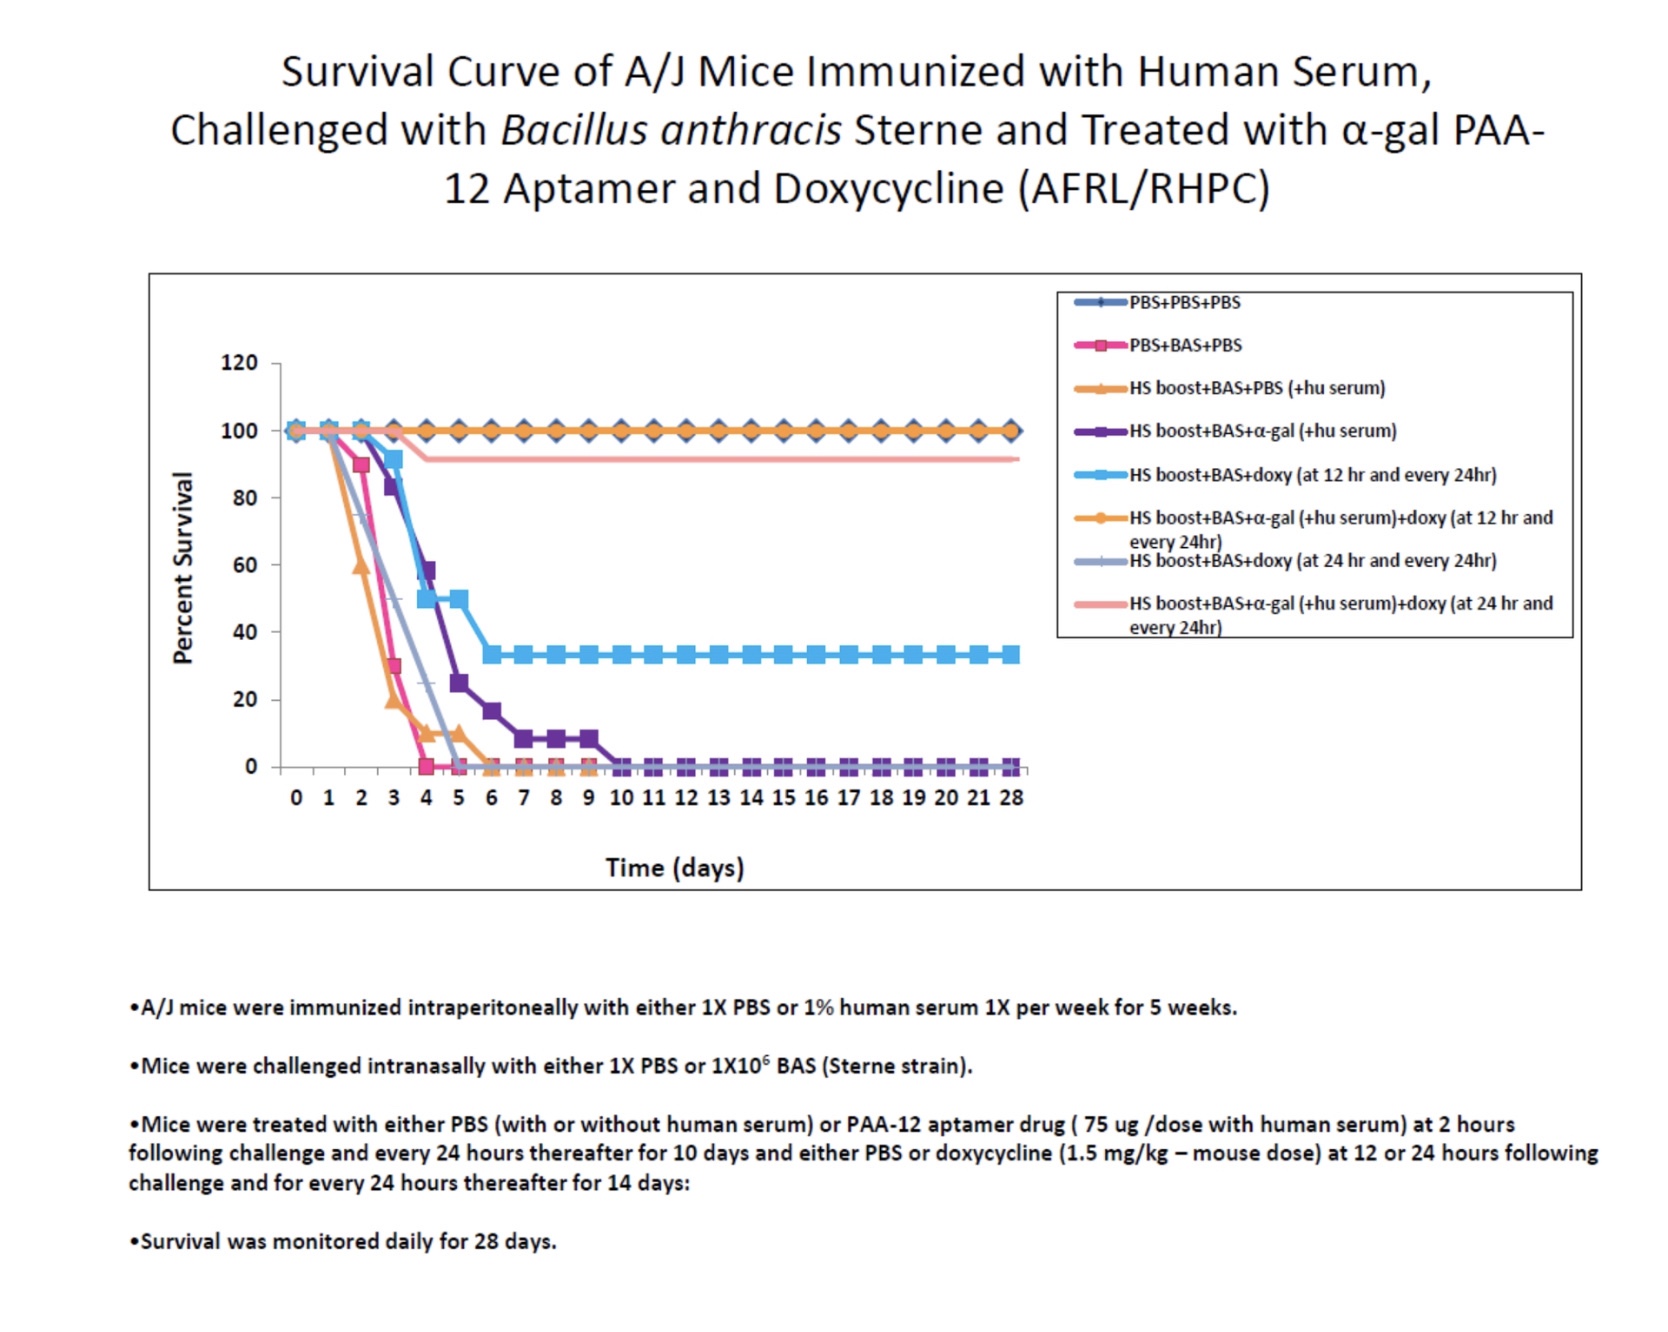
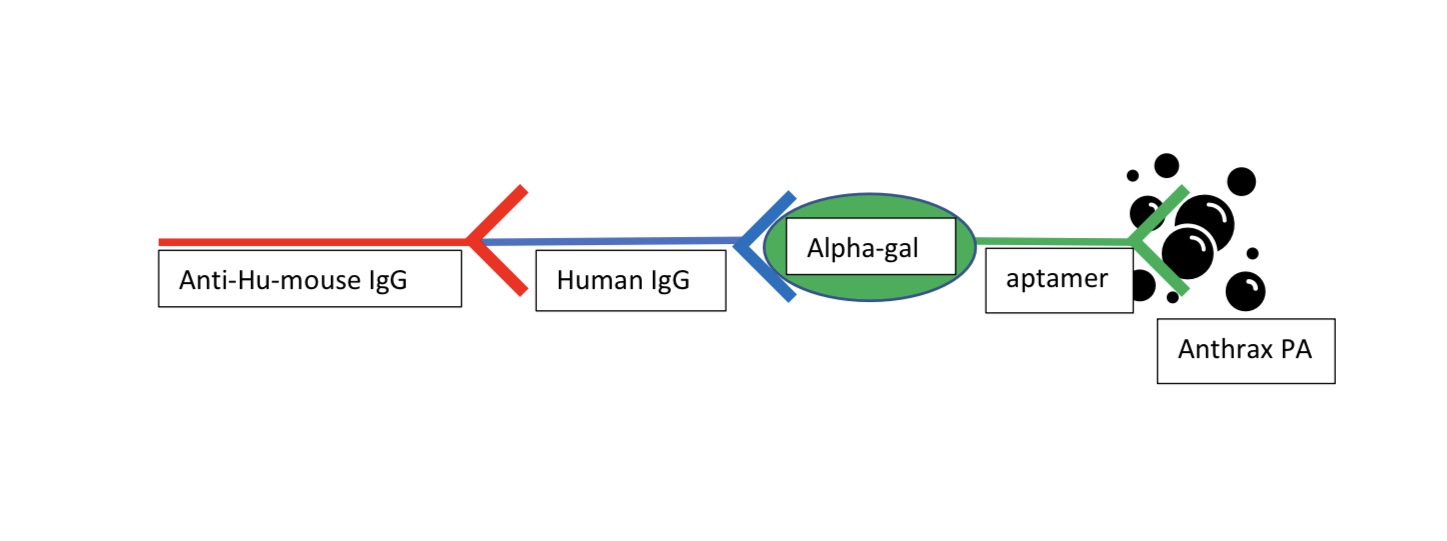
An actual example of redirecting immunity: mouse antibody against human serum, against which mice were previously inoculated, redirected to neutralize anthrax toxin by adapter aptamers in order to prevent death from inhaled anthrax spores in the face of insufficient antibiotic treatment. The antibiotic doxycycline is only bacteriostatic. If the immune system doesn’t kick in or another mechanism becomes activated, the anthrax will grow and overwhelm the host as illustrated by the data. The aptamers only neutralize toxin stoichiometrically, but have no effect on the bacteria directly. Therefore, they also only buy time for the host immune system to end the infection.A simple diagram of the doubly re-directed immunity, represented by the previous data, to eliminate anthrax toxin in mice. Mullis, K.B., Vivekananda. J., Kiel, J.L., Cook, R.M. Chemically Programmable Immunity, US Patent 8,604,184 B2, December 10, 2013; invented by the Nobel Laureate Dr Kary Mullis (December 28, 1944-August 7, 2019).
Bats and children 9 years and under may have something in common in their immune responses to COVID which spares them from severe symptoms— immunotolerance. Bats have several mechanisms to prevent over responsiveness to viruses and limit collateral non-specific damage by inflammation. Humans express minimal baseline levels of type I interferons (IFNs), and they are highly inducible upon stimulation, but many bat species, such as the black flying fox (Pteropus alecto), constitutively express some baseline IFNα, and several IFN-stimulated genes before stimulation. Therefore, they are prepared to inhibit viral replication before it can spread to many tissues and prime an overt response with a heavy viral load. The restricted induction of type I IFNs minimizes production of inflammatory cytokines and reactive oxygen species by innate immune inflammatory and phagocytic cells. The kinetics of the IFN response in bats also differs from those of other mammals, in that it has a faster decline for some bat interferon-stimulated genes post-stimulation. Bats have a reduced production of reactive oxygen species compared to similar-sized non-flying mammals, but retain intact activity of the important antioxidant enzymes like superoxide dismutase. These findings suggest either a more effective scavenging of reactive oxygen species or a lower production of reactive oxygen species by bats, or a combination of both.
Immune tolerance in bats is also expressed in dampening of the STING-dependent type I IFN response in several bat species, resulting from a point mutation in the Stimulator of Interferon Genes (STING) https://www.frontiersin.org/articles/10.3389/fimmu.2020.00615/full. STING is an important pattern recognition receptor which triggers cytosolic-DNA-induced signalling and has a key role in infection, inflammation, and cancer. This mutation has the effect of dampening STING mediated responses to infection with bat-borne RNA viruses, which activate STING by inducing host DNA damage. A more recent study has revealed another key mechanism by which bats naturally dampen host inflammation in response to ‘sterile’ danger signals and infections with RNA viruses. NLR-family pyrin (NLRP3), a key inflammasome sensor that recognizes various cellular stresses and pathogen invasion, is dampened at both the transcription and protein translation level in bats. Importantly, reduced NLRP3-mediated inflammatory responses to RNA viruses have no, or minimal, effect on viral loads https://www.nature.com/articles/s41586-020-03128-0.pdf.
In children, which I have discussed in earlier posts, there is a rapid early interferon response to SARS-CoV-2. Community acquired pneumonia in children younger than 5 years old, with severe and life-threatening symptoms, have significantly increased interleukin-17 (IL-17) production. Immune profiling of these children showed that mucosal-associated invariant T (MAIT) cells from the lungs, but not blood, actively produced IL-17 (MAIT17) https://www.nature.com/articles/s41385-020-0273-y.pdf. Previously, I posted that the IL-17/Th17 pathway plays a major role in regulating the severity of COVID and turning it down by removing viruses early with interferon, reducing the viral load and distribution, limiting the reactive oxygen response of this pathway and, therefore, the collateral damage, as seen in most children exposed to COVID who are less than 9 years old. Th17 lymphocytes promote signals typical of early inflammatory events, and serve as a bridge between innate and adaptive immunity https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2821718/pdf/nihms-152030.pdf. Therefore, they represent the pivot point between a severe and mild antiviral innate immune response and an effective long term protective adaptive immune response. In children, they produce a mild but virus-eliminating early response, and are less likely to yield a sustained adaptive immune memory as in adults, from the infection, a form of immunotolerance. They sacrifice long term immunity for the lower severity of the disease. Stopping the virus before it systemically disseminates is critical because it can otherwise damage blood vessels in many tissues and organs causing retiform purpura, gangrene and vascular permeability, swelling to bleeding, as well as widespread deposition and activation of neutrophils by activating the complement system. It induces a hypercoagulable state with micro- and macroangiopathy. The activation occurs by forming complement cascade activating antibody-antigen complexes or by the alternate complement pathway activated by the spike glycoprotein acting as a lectin (https://www.translationalres.com/action/showPdf?pii=S1931-5244%2820%2930070-0). However, to achieve long term immune memory one might have to first endure a “baptism of fire”.
The loss of smell (anosmia) and disruption or loss of taste (dysguesia or ageusia) are unique symptoms of COVID-19. The sensations of hot peppers and mint can also be lost, but these are transmitted by different neurons, those for pain. The former 2 lack ACE2 viral receptors but some of the pain sensor neurons have them. Most recover smell and taste within 6 months, but some require 2 years or fail to recover the senses at all. During recovery, parosmia may occur, which is the sensing of irrelevant smells unrelated to the objects’ odors. Irrelevant tastes, often unpleasant ones, may also develop. These effects are postulated to be from errors in re-established neuronal connections, which can be corrected, in time, due to the plasticity of the nervous system. Influenza has produced anosmia in the past, and provides some understanding of the symptomology and prognosis. The primary mechanism for the loss of smell and taste with COVID is not infection of neurons but supporting cells that help maintain neuronal function. For smell, these are sustentacular cells, and different supporting cells for taste. The neurons per se are spared, but in the case of the attack on sustentacular cells, the finger-like cilia on the neurons, which contain the smell receptors, are lost because of the loss of the supporting sustentacular cells. Since the neurons are not attacked directly, the loss of smell and taste are not usually irreversible. The pain sensation associated with sensing aromatics like mint and plant capsaicinoids like capsaicin (8-methyl-N-vanillyl-6-none amid) is another matter since these neurons have ACE2 viral receptors https://www.scientificamerican.com/article/mysteries-of-covid-smell-loss-finally-yield-some-answers1/.
A more ominous effect on the Central Nervous System (CNS) of some virus infections and chronic neurodegenerative diseases, that resemble the response to a virus but have no known virus such as Multiple Sclerosis (MS) associated with them, is demyelination. It, like the effects of SARS-CoV-2 on the sustentacular cells, involves supporting cells of neurons, the oligodendrocytes. In MS, the demyelination occurs in the Central Nervous System (CNS), the white matter of the brain and spinal cord, leading to pain, tremors, speech difficulties, loss of balance, vision difficulties, sensation loss and paralysis to various degrees, with multiple isolated episodes of recurrence. The myelin is a fatty coating of the nerve processes that resembles insulation on an electrical wire, strip it away and nerve conduction fails. It has been associated with viral infections, Epstein-Barr virus most recently (https://www.science.org/doi/10.1126/science.abj8222), and genetic pre-disposition leading to this autoimmune disease. Previously, measles, and even closely related canine distemper viruses, were suspected of causing MS. The latter because it commonly causes CNS demyelination in dogs, especially adult dogs. In puppies it starts as a respiratory virus with skin lesions, causing footpads to thicken and harden, leading to its nickname, “hard pad disease” (measles also causes hypersensitivity in the skin causing damage to small blood vessels and a rash, Koplik’s spots). Measles can also attack the CNS directly or secondarily, probably by triggering autoimmunity. CNS involvement, even in uncomplicated measles, is common. Transient EEG abnormalities are detected in 50% of patients. Measles virus is rarely isolated in acute measles panencephalitis. Therefore, it is considered the result of autoimmunity. Distemper does not kill the oligodendrocytes, which make myelin, but inhibits its synthesis. Sterile demyelination can be induced in animals (in guinea pigs, experimental allergic encephalomyelitis (EAE) induced by guinea pig myelin basic protein) by immunization against their own basic protein, a component of myelin. Other viruses like alphaviruses, encephalitis viruses, do not use this mechanism, but open the CNS blood vessels (blood brain barrier) to penetration by lymphocytes and other inflammatory cells causing collateral damage to the brain. SARS-CoV-2 has the potential of following all these neurological pathogenic pathways: damaging blood vessels in the brain to let in inflammatory cells; damaging or altering cells that support neurons (glia); and causing autoimmune responses in the CNS. With as many people as have been infected, all of these are likely to be seen, at one time or another, no matter how rare. Oddly enough, the CNS may provide a way to truncate the disease so mild COVID-19 does not turn into severe to lethal or chronic disease. The answer may be in a class of drugs, Selective Serotonin Re-uptake Inhibitor (SSRI), for anti-depression and anti-anxiety. New data shows fluvoxamine (FLV; Luvox), one such drug, could keep mild COVID-19 from worsening. In a preliminary study, 65 patients who received fluvoxamine (50 mg twice daily) and 48 who did not, the results were the incidence of hospitalization being 0% (0/65) with fluvoxamine and 12.5% (6/48) with no treatment. At 14 days, residual symptoms persisted in 0% (0/65) with fluvoxamine and 60% (29/48) with no treatment, (David Seftel and David R Boulware, Prospective cohort of fluvoxamine for early treatment of COVID-19, published by Oxford University Press on behalf of Infectious Diseases Society of America, 2021, and https://jamanetwork.com/journals/jama/articlepdf/2773108/jama_lenze_2020_pc_200006_1607119471.77989.pdf). Fluvoxamine has a well-established mechanism of action as an anti-inflammatory (Dorian A. Rosen et al, Modulation of the sigma-1 receptor−IRE1 pathway is beneficial in preclinical models of inflammation and sepsis, Sci Transl Med 11, eaau5266. DOI: 10.1126/scitranslmed.aau5266, 2019; https://stm.sciencemag.org/content/scitransmed/11/478/eaau5266.full.pdf). The related SSRI drug Fluoxetine (Prozac) has a long history of anti-inflammatory action against stress-induced oxidative cell damage; https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4876141/pdf/PRP2-4-e00231.pdf.
The ER stress sensing protein IRE1alpha, and the closely related protein IRE1beta, are able to powerfully affect the inflammatory behavior of both immune and non-immune cells. A major ER stress sensor, inositol-requiring enzyme (IRE1) is selectively activated by the Toll-like receptor 4 (TLR4) for the ligand lipopolysaccharide (LPS), bacterial endotoxins. IRE1 regulates inflammatory cytokine production via both its endonuclease activity and transcriptional regulation. IRE1 activity is required for cytokine production, likely via XBP1-mediated transactivation of interleukin-6 (IL-6) and tumor necrosis factor–alpha (TNF-alpha). FLV, an antidepressant drug, has low-nanomolar affinity for S1R, ER-resident protein sigma-1 receptor, which has also been reported to have anti-inflammatory properties. In one set of experiments, a high dose of LPS (6 mg/kg) was administered with FLV (20 mg/kg) at the same time. FLV treatment protected mice from mortality and reduced serum IL-6. S1R can also dampen inflammation in human cells. Heparinized peripheral blood from healthy donors was stimulated in the test tube with LPS (10 ng/ml) in the presence or absence of FLV (20 micromolar), and the production of inflammatory mediators was measured. FLV significantly reduced LPS-induced IL-6, IL-1beta and IL-12, and decreased IL-8 production in cells from all donors. These data indicated that the anti-inflammatory action of the FLV S1R ligand is conserved across species. Taken together, these anti- inflammatory effects and the benefits to COVID treatments, correlate with what I have said about the inflammatory effects and mechanisms of COVID in earlier posts and provides hope these off-the-shelf drugs will provide relief to both acutely severely affected patients as well as long haulers with neurological symptoms.