
The immune system’s first line of defense, innate immunity, may be responsible for SARS-CoV-2 immunosuppression by over producing TNF alpha (tumor necrosis factor) https://www.cell.com/action/showPdf?pii=S0092-8674%2820%2931067-9. This could explain recent reports of re-infection. TNF is the first cytokine to appear in the blood within minutes after an injury or stress. Other pro-inflammatory mediators like IL-1 or IL-6 appear later. The name “tumour necrosis factor” came from the cytokine’s causing vascular activation and thrombosis resulting in necrosis of subcutaneous tumors in mice. TNFR1, also known as p55, a TNF receptor present on all cells, when cross-linked by TNF, generates a pro-inflammatory response. It activates NF-κB, mitogen-activated protein kinases, anti-apoptotic responses, and generation of other pro-inflammatory cytokines such as IL-1, IL-6, and GM-CSF. When not acting appropriately, TNF binding to TNFR1, yields such autoimmune diseases as rheumatoid arthritis. An alternative receptor for TNF, TNFR2 has positive beneficial effects. TNFR2, also known as p75, has restricted tissue distribution and activates different signalling pathways. It is important for repair and homeostasis, and the cells with the highest expression of TNFR2 are T regulatory lymphocytes. TNRF2 gene knockout mice have enhanced pathology, such as poor survival following coronary artery damage. However, several monoclonal specific ant-TNF antibodies, which counteract the negative effects of TNF, have been FDA approved over the years for rheumatoid arthritis, which may reduce the lethality and long term adverse effects of COVID, if TNF is the proven cause of the severe effects. There are five approved anti-TNFs: (1) infliximab, a chimaeric IgG anti-human monoclonal (Remicade®); (2) etanercept, a TNFR2 dimeric fusion protein, with an IgG1 Fc (Enbrel®); (3) adalimumab, a fully human monoclonal antibody (mAb) (Humira®); (4) golimumab, a fully human mAb (Simponi®) and (5) certolizumab, a PEGylated Fab fragment (Cimzia®). https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4279876/. Another piece of evidence that TNF and its receptor TNFR1 are important in COVID is that children seem to be resistant to the severe effects, except in some instances when they display multiple organ inflammation, Kawasaki-like syndrome, because they produce a lot of the anti-inflammatory cytokine IL10. The responses of neonates compared to adults change from increased IL-10 as neonates to balanced IL-10/T helper type 1 (Th1)/Th2/Th17 cytokine levels early in life. This allows protection from pathogens but reduces the chances of a cytokine storm https://www.nature.com/articles/s41390-020-0881-y.pdf. In 1995, in my book Type B Cytochromes: Sensors and Switches, pointed out the importance of IL10 to reduce the effects of TNF which was linked to the oxidative burst which produced superoxide, hydrogen peroxide by the enzyme NADPH oxidase, and alternatively nitric oxide (NO) by nitric oxide synthase enzyme (NOS) by white blood cells: “Lymphokines provide extra-macrophage regulation of NO production. IL-10, produced by CD4 + lymphocytes of the Th-2 subset, not only inhibits synthesis of gamma-interferon by both T cells and NK cells, but also inhibits the synthesis of NOS by mouse macrophages. Another lymphokine, IL-13, inhibits TNF production, generally downregulates macrophage LPS responses, but assists in upregulating gamma-interferon production. This interleukin also inhibits HIV replication in vitro and immunity to tranplanted tumors. Also, NOS induction is directly involved in allograft rejection in transplantation, as one of the earliest events noted. Even though NO has been shown to be generally immunosuppressive for lymphocyte proliferation, human lymphocytes can produce picomolar concentrations of NO that are essential as a messenger initiating lymphocyte responses, including DNA synthesis.” Thus a measured NO response is beneficial but a large amount can lead to immunosuppression or failure to develop immune memory. This level could perhaps be adjusted to optimal by treatment with such NO traps as 3-amino-L-tyrosine. Recently, a paper has appeared to contradict this scenario. Severity in adult COVID-19 appears to be related to a combination rise in IP-10, IL-6 and IL-10. IP-10 causes inflammation induced by gamma interferon. The combination may be an indicator of immune exhaustion in adults or merely concomitant effect rather than cause. However, based on depletion of certain immune cells (basophils migrating to the lungs and lymphocytes and dendrocytes) and a left shift of lymphocytes to more immature and replicating forms, noted in the paper, this confusion over what COVID does to the immune system is time and tissue related (when and where measured). TNF not changing generally, as noted in this recent paper, https://www.nature.com/articles/s41591-020-1038-6.pdf, can be because it’s produced very locally and affects only lymph nodes and other lymphoid tissues, without generalized rise in levels and effect.
Warning! COVID-19 is a Wake Up Call that the US is Not Prepared for a Natural or Nefarious Biological Agent Attack by Choice: Forewarned is Only Forearmed when You Do Not Ignore or Forget the Warning
This blog has intentionally tried to avoid political or socioeconomic arguments for the US failures to mitigate the COVID-19 pandemic within its borders, but the actions and lack of appropriate actions of the Federal to State to Local government bodies have made this avoidance impossible. My past observations have addressed the question: “What drives research in infectious disease, or for that matter, any scientific research? We would like to believe it is the level of the threat to humanity or food and fiber sources and domestic animals, or the need for all humankind to grow in knowledge and wisdom. Some feel in the private, corporate world, it is solely profits. Public funded research and academic research may be thought of as driven by national pride in science and technology leadership and, even as a tool for facilitating science, technology, engineering and mathematics (STEM) education, even for better jobs and standard of living. However, the main driver, at least at present, seems to be communication containing sensationalism and catchy headlines which generate concern or just raw fear. I call this “political science”, the driver of all other science by control of the purse strings through public marketing and faddism to generate pressure to fund.” The Black Dragon Trilogy; https://a.co/itfIq0o. In face of this motivation, a politically driven anti-science and anti-public health movement has occurred at the Federal Executive Administration and State House levels, leading to such counter protective measures as faddish unproven treatments, false characterization of SARS-CoV-2 virus and the disease, COVID-19, and fractured guidance on personal protection measures with downright banning of local government mandates for protective masking, social distancing and public health regulation of business and group activities. The WH is once again oppressing science and it is directly related to preventing the next COVID. Science Magazine – August 28, 2020 – page 1039. The results of all this have been inevitable: More than 5.5 million Americans infected since the start of the pandemic and at least 172,000 dead. America continues to fail because of failed political leadership: Georgia, Texas, Florida. Besides the lack of unified political will being a major hindrance, the compartmentalization of the problem has made matters worse. Beth Cameron, former Senior Director for Global Health Security and Biodefense in the NSC, wrote, “When President Trump took office in 2017, the White House’s National Security Council Directorate for Global Health Security and Biodefense survived the transition intact.“Its mission was the same as when I was asked to lead the office, established after the Ebola epidemic of 2014: to do everything possible within the vast powers and resources of the U.S. government to prepare for the next disease outbreak and prevent it from becoming an epidemic or pandemic. One year later, I was mystified when the White House dissolved the office, leaving the country less prepared for pandemics like covid-19”. Tim Morrison, former senior director for counterproliferation and biodefense on the NSC, wrote in another Washington Post Op-Ed, “It is true that the Trump administration has seen fit to shrink the NSC staff. But the bloat that occurred under the previous administration clearly needed a correction. … One such move at the NSC was to create the counterproliferation and biodefense directorate, which was the result of consolidating three directorates into one, given the obvious overlap between arms control and nonproliferation, weapons of mass destruction, terrorism, and global health and biodefense. It is this reorganization that critics have misconstrued or intentionally misrepresented. If anything, the combined directorate was stronger because related expertise could be commingled” There is controversy on how to describe these changes but the changes at the NSC’s Directorate for Global Health Security and Biodefense in 2018, departure of some members due to “streamlining” efforts under John Bolton, led the “pandemic response team” as a unit to be largely disbanded. This led to confusion just as did the shifting of hospital COVID-19 data collection from the CDC to HHS and back again and failed and delayed implementation of CDC pandemic plans. Furthermore, delays in filling professional job slots at CDC have also contributed to the overall failure and mismanagement of the pandemic response. Seeing SAR-CoV-2 as separate political, economic, National security (military), public health, medical and veterinary problems, and self-isolating from a global science-based response and establishing a physical “fortress-against-the-world” response has shipwrecked us where we are. In this blog and my books, I have tried to convey that this is a global problem that requires global cooperation and collaboration, including among government agencies, not stove-piping them through a high level political screening agency. High level coordination is necessary but not high level screening and suppression. Freedom to act locally with central support and high level policy guidance is good, but central micromanagement of execution is bad. The US military has learned this lesson since the Vietnam War and has had this in their doctrine for years , and its effectiveness and efficiency has been demonstrated to be superior to centralized control of execution which was characteristic of the former Soviet Union and now of Russia. To be more specific about how the Biodefense problem is inseparable from the pandemic public health problem, let me give you a short history of the military Biodefense issues. Prior to the dissolution of the Soviet Union, December 31, 1991, unbeknownst to the US, the Soviets had continued to develop a massive biological warfare infrastructure. One of their production vats capacity was larger than the entire Iraqi biowarfare production. The Soviets had 2 levels of agents: tactical (like anthrax) and strategic (like smallpox). Tactical would be used locally on troops in the battlefield and strategic would be delivered in an intercontinental ballistic missile warhead against an entire population, including civilians, to destroy the will and means of a nation to execute a war. Of course, asymmetric warfare use of bio weapons by terrorists and special forces made them weapons of mass terror (WMT) rather than weapons of mass destruction (WMD). If I were to describe SARS-CoV-2 in military (Russian) terms, it would be a strategic WMT and WMD. In 6 short months, it has killed and incapacitated a large number of the population, damaged the economy, restricted industrial production, handicapped military operations, divided the public politically, caused panic and social unrest, disrupted education, overwhelmed the medical system and enhanced all these vulnerabilities associated with disparities in wealth, jobs, and access to adequate health care. I would say it has done grave damage to the National Security of the United States. What other Army could have mobilized and marched across the world so fast? Can there be any question that this is a defense, National Security and public health issue simultaneously? The US offensive biowarfare program started after the beginning of WWII, October 1943, at Dugway Proving Grounds, Utah, and ended in 1972. In 1969, President Nixon had terminated the US offensive biological warfare program and ordered all stockpiled weapons destroyed. National Security decisions 35 (November 1969) and 44 (February 1970) had ended the programs for microbes and toxins, respectively. The only Institution supposedly to remain was the US Army Medical Research Institute of Infectious Diseases (USAMRIID), established to continue the development of medical defenses against biological attack and development of treatments for medical casualties caused by infectious disease, which, up until recent times, has caused more casualties than combat. In 1972, more than 100 nations (including the US and Soviet Union) had signed the Biological and Toxin Weapons Convention (BWC), the world’s first treaty (albeit weak in enforcement) banning an entire class of weapons. The agreement prohibited the possession of biological agents except for “prophylactic, protective, or other peaceful purposes.” Obviously, the Soviet Union did not live up to it. During The US offensive program, the US was more interested in using “incapacitating agents” (Venezuelan Equine Encephalitis Virus, Brucella bacteria, and tularemia bacteria) than lethal agents such as plague and anthrax, although these were researched. When the US realized there were still state sponsored and terrorist biowarfare programs, it enacted the Biological Weapons Anti-Terrorism Act of 1989 (BWATA, Pub.L. 101–298, enacted May 22, 1990). The agents then fell into Tier categories with the most dangerous agents for humans and animals in Tier 1 Select agents and toxins – A subset of select agents and toxins have been designated as Tier 1 because these biological agents and toxins present the greatest risk of deliberate misuse with significant potential for mass casualties or devastating effect to the economy, critical infrastructure, or public confidence, and pose a severe threat to public health and safety: Bacillus anthracis, Bacillus cereus Biovar anthracis, Botulinum neurotoxins, Botulinum neurotoxin producing species of Clostridium, Burkholderia mallei, Burkholderia pseudomallei, Ebola virus (CP at Brooks investigated cloned subunits because we did not have a BSL4 lab), Francisella tularensis, Foot-And-Mouth Disease virus, Marburg virus, Rinderpest virus, Variola major virus (Smallpox virus), Variola minor virus (Alastrim) (CP used vaccinia virus as an investigative stand in for Smallpox) and Yersinia pestis. The bolded agents are the Tier 1 or related Tier 1 agents we investigated in the Counterproliferation Group at Brooks City-Base, USAF, San Antonio, Texas. Even though Foot-And-Mouth Disease virus and Rinderpest virus are animal viruses only, they could devastate agriculture, disrupt the food supply, and do great economic harm, true strategic weapons. Also FMDV is truly aerosolizeable and can spread on the wind for miles.

Division of Select Agents and Toxins
1600 Clifton Road, NE, Mailstop H21-7
Atlanta, GA 30329
Telephone: 404-718-2000
770-488-7100 (after hours)
Fax: 404-718-2096
Email: LRSAT@cdc.gov
Animal and Plant Health Inspection Service
Agriculture Select Agent Services
4700 River Road, Unit 2, Mailstop 22, Cubicle 1A07
Riverdale, MD 20737
Telephone: 301-851-3300 opt. 3 (voice only)
Fax: 301-734-3652
Email: AgSAS@usda.gov
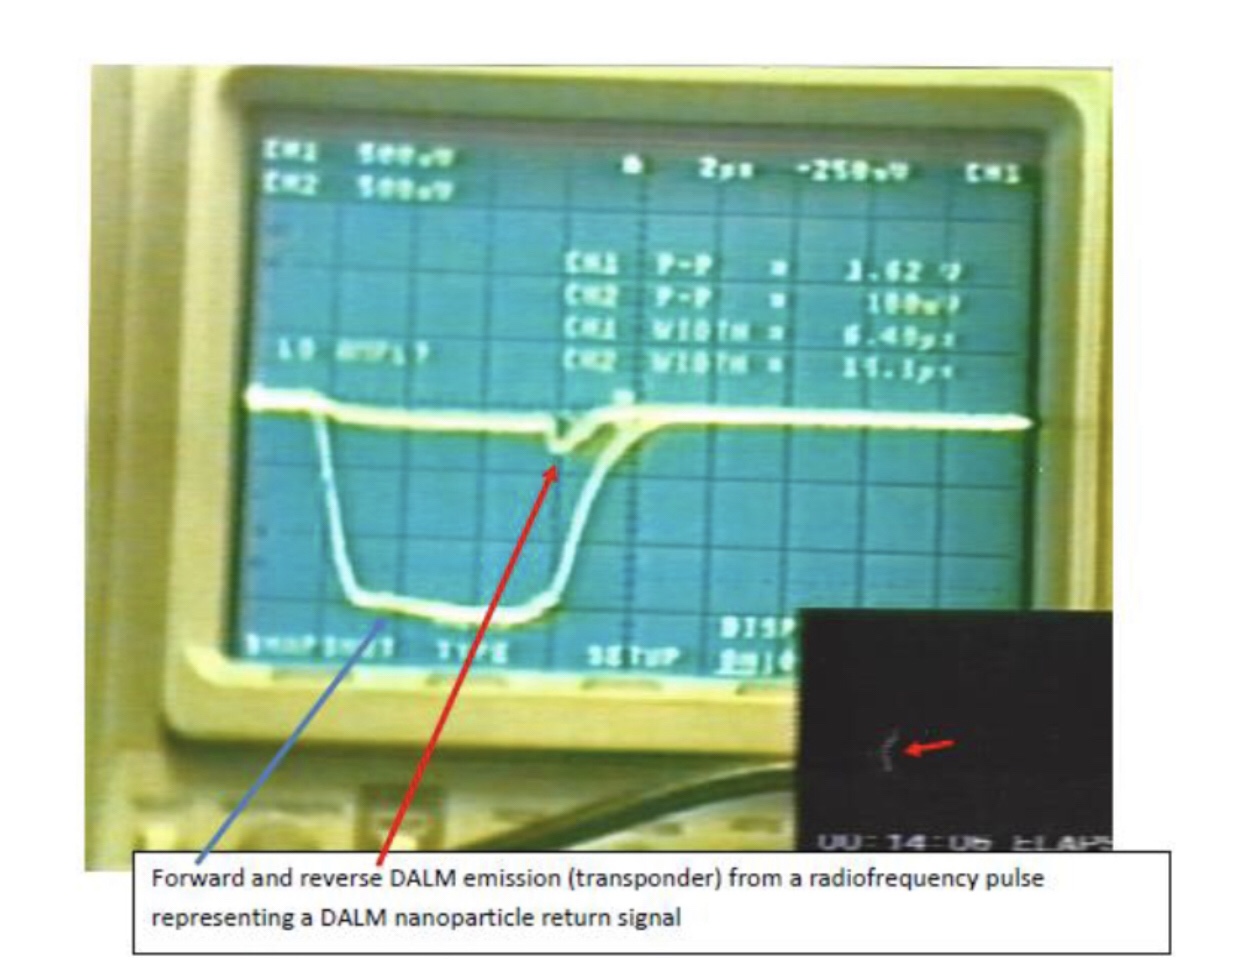
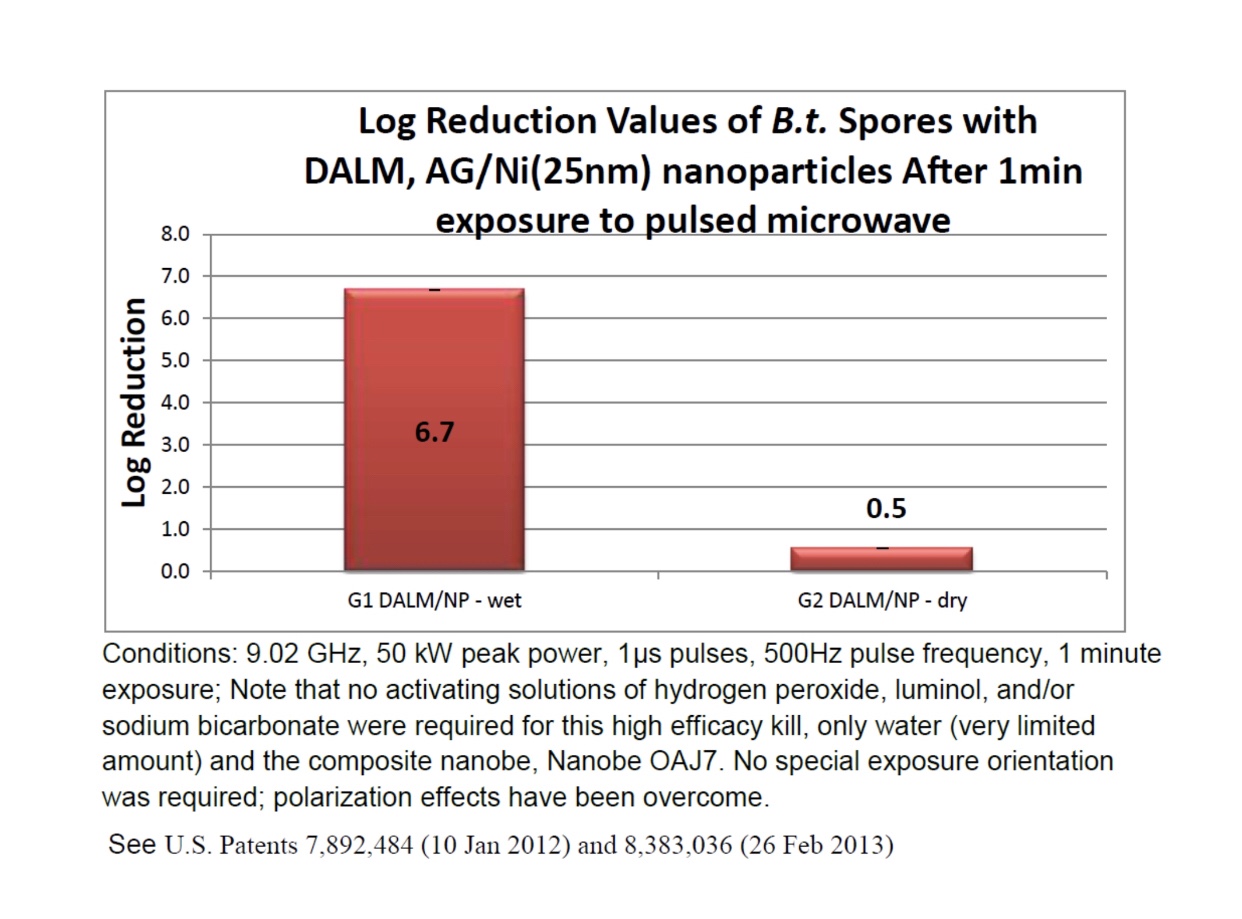
However, it is unrealistic to think that restricting the access to these agents in the US can control and prevent nefarious use of these or other biological agents not on such a list. This fact led to Nanobes, discovered by the Brooks CP team and described in earlier posts in perhaps esoteric terms for most, falling into no-man’s land, and have not been put to good and most appropriate use to fight SARS-CoV-2 and other emerging infectious agents. As noted, they were designed to detect, identify, tag with fluorescence and collect magnetically, known and unknown pathogens under minimal and adverse conditions in non-permissive territory by Special Forces with minimal technical execution. They were also designed to be dispersed over wide and distant areas with light weight equipment and be recovered at least in part. They could also be activated not only to identify and collect agents but to kill them with pulsed microwaves, even in cells and tissues as well as on environmental surfaces. They were designed to transform bacterial hosts or transfect animal and human cells to manufacture biosynthetic replicates which could perform the same functions as the synthetic originals. This could be even done in the field with minimal equipment and supplies (disposable fermenters and lyophilized bacterial production hosts and media which could be reconstituted with water after a specific binding Nanobe was selected out of a random library for amplification). This versatile solution became perceived as a potential versatile weapon which side stepped domestic and international law. I warned of the consequences of not using it and, if not, not being prepared for its use by others in a closed scientific meeting in 2009 just prior to ending the CP group research and my retirement. The Russians and, especially the Chinese, followed that part of our work which was published in the open scientific literature and in patents. They have since pursued similar non-military applications evidenced by their open scientific literature publications. By their own admission they foresaw other applications: “the Chinese military ambition, was first described in Military Review, July-August 2005 by Guo Ji-wei and Xue-sen Yang. Paraphrasing what these goals are: (1) Crypticity: Biotechnological Warfare is convenient, easy to use, has a small logistics tail (very prone to Terrorist or Special Forces use); (2) Controllability and recoverability: Can be used to measured effect from kill to non-lethal with the option to offer “mercy” in exchange for surrender; and (3) Biotechnological vs. Biological Weapons: Biotechnological Warfare should not be considered Biological Warfare and side-steps any international law or treaty restrictions.”—The Black Dragon Trilogy. All this has left me exhausted and frustrated. I only hope more people will read and share my books and blog posts so the information they contain might reach the right people to make a difference before it is too late.


Commercial as well as custom nano sprayers can be used to dispense. “The electrosprayer can continuously apply up to 10 ml of liquid containing over 2 million Nanobes per ml spread over a period of 24 hrs from a package the size of an iPhone. One gram of 20-nm particles can be spread over a 10mX10mX1 Km rectangular cube and maintain the same approximate concentration as in the nanosprayer (2,400,000 per cubic cm).”
“This proposal combined novel device development with state of the art nanoscale bioelectromagnetics. Because of the unprecedented novelty of the wireless nanoelectrode device( s), we did not anticipate the immediate use of the technology in the CNS”—The Black Dragon Trilogy. https://www.npr.org/2020/10/27/927263593/a-cia-officer-visits-moscow-returns-with-mysterious-crippling-headaches
Selection Pressure from Monoclonal Antibody Drives Mutations in SARS-CoV-2: Why Natural Polyclonal and T Cell Immunity is Better
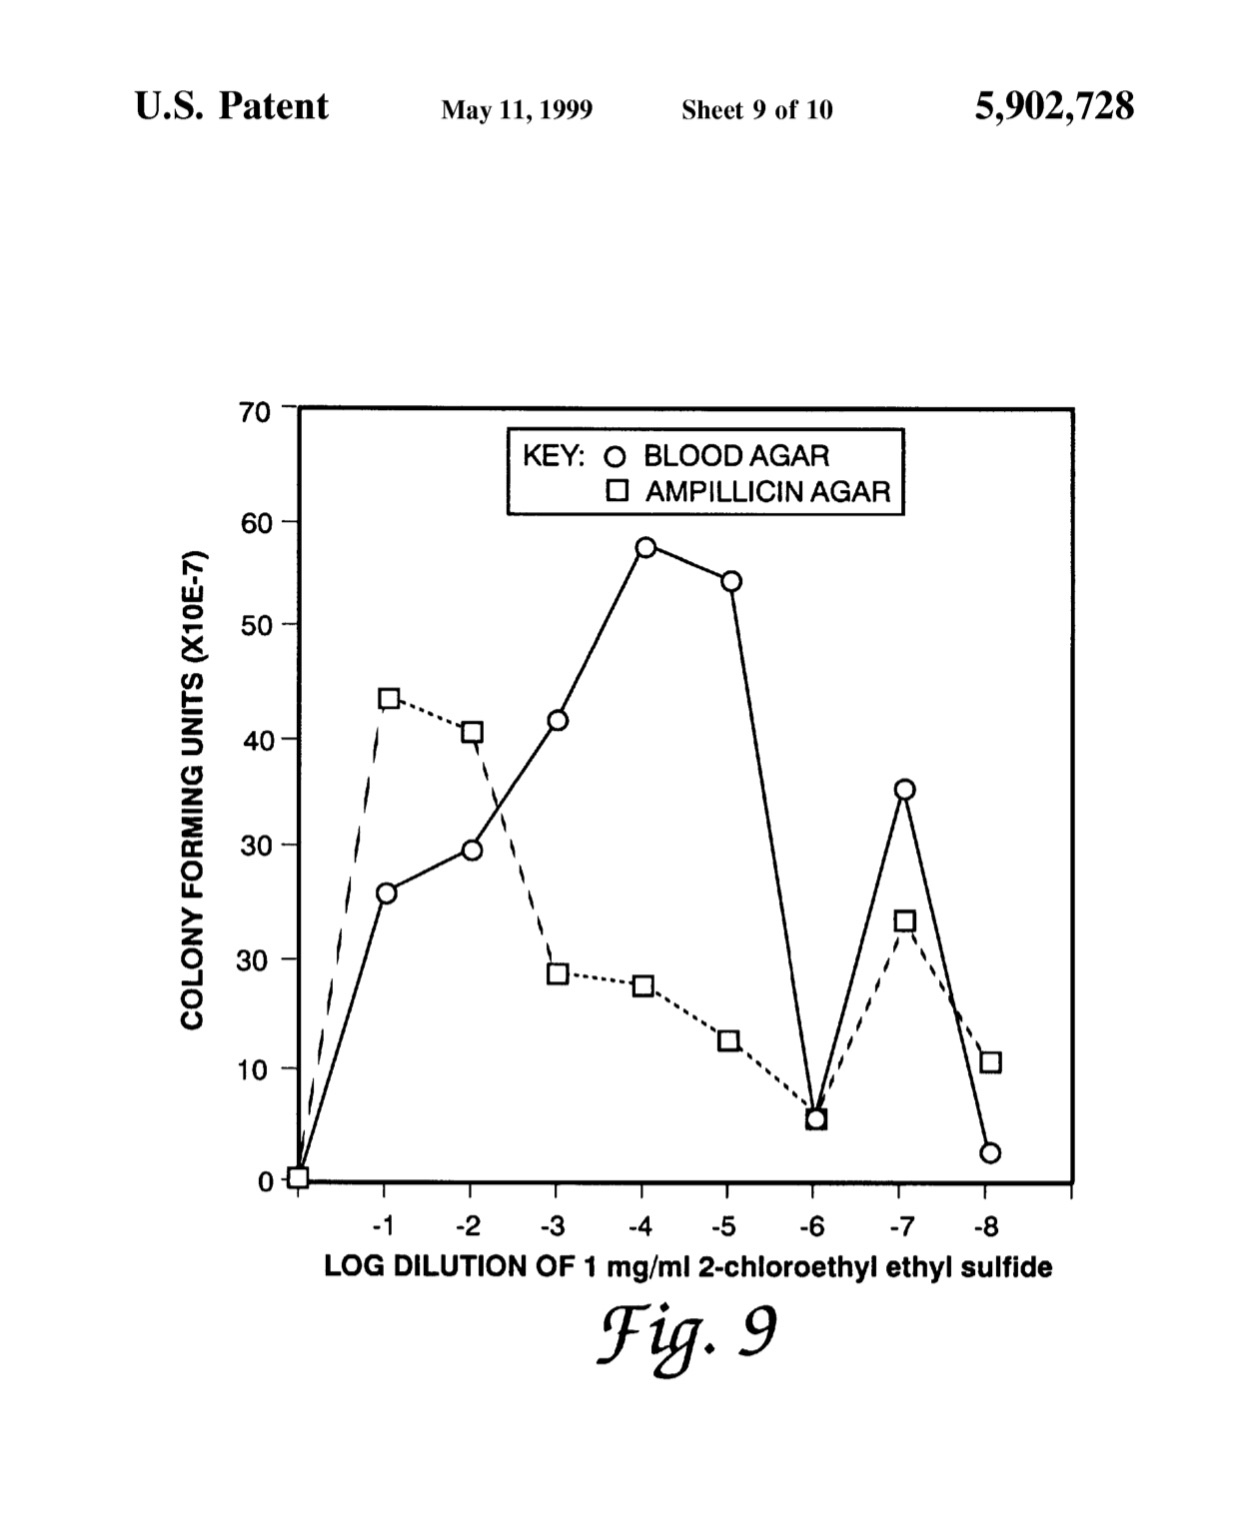
A recent study in Science magazine (https://gtxcel.omeclk.com/portal/wts/uemckdyf000aeg3VDqj9szALvfeTjSdoNYhxH3VWRnROps%7Eqfc%7C8mc) supports the idea that monoclonal antibody against a rapidly growing and spreading virus like SARS-CoV-2 is not necessarily a good idea because it can select for mutants that are resistant to the neutralizing effects and replace those that are sensitive. Polyclonal antibodies thwarted this escape because it is much more difficult to mutate past many different antiviral antibodies as is also seen with multiple drug therapies. For example, in 1995, a combination drug treatment known as the “AIDS cocktail” was introduced which made AIDS a survivable , chronic disease. This type of therapy is known as highly active antiretroviral therapy (HAART), also called combination antiretroviral therapy (cART). Our own research, demonstrated that a mutagen (2-chloroethylethylsulfide) could make bacteria resistant to one but not two antibiotics at the same time in the same microbes (ampicillin and 3-amino-L-tyrosine: Patent #: 5,902,728; date: May11,1999):
Deep Dive: More on Attribution, the Origin of SARS-CoV-2 and Other Coronaviruses Crossing to Other Species and Humans: Can a Leopard Change its Spots?
It’s not that easy for a virus like a coronavirus, which is very host species specific and has a proofreading replicating enzyme, RNA dependent RNA polymerase, to mutate to infect a new species without considerable environmental selection pressure. Even all the hype about the mutated strain of SARS-CoV-2, D614G, implying it will evade immunity, is not quite that bad. SARS-CoV-2 isolates, with the D614G mutation in the viral spike (S) protein, predominate over time in infected populations, the change enhancing viral transmission. This change is not about better binding to receptors but about better processing for the virus to enter the cell and complete its replication, likely changing its infectious dose. Although ideally it takes only one virion to infect a cell, in practice many fail and a certain number of viral particles are required per cell to have successful infection and replication (multiplicity of infection). However, SG614 (the new mutant) did not bind ACE2 more efficiently than SD614 (original virus) and the viruses containing these S proteins were neutralized with comparable efficiencies by convalescent plasma from recovered patients. These results show SG614 is more stable than SD614, consistent with epidemiological data suggesting that viruses with SG614 transmit more efficiently, but are not more pathogenic nor would they escape vaccination.(https://www.scripps.edu/news-and-events/press-room/2020/20200611-choe-farzan-sars-cov-2-spike-protein.html). The origin of the original human version of the virus, unlike implied by the retroactive gene analysis mentioned in an earlier post, is not by simple mutation. A proactive study, using pseudo type viruses, not a coronavirus, but a vesicular stomatitis virus chimera with a plasmid-produced coronavirus spike protein added after its replication and carrying a light-producing firefly luciferase gene as a marker of infection, showed that the changes needed to crossover to humans were greater than could reasonably be accounted for by mutation alone. In contrast to changing individual amino acids, the proactive constructs showed that clade 2 and 3 (different genetic groups with other host specificities) receptor binding domains containing the clade 1 closest receptor-contacting amino acid residues are compatible with human ACE2. Coronaviruses frequently undergo recombination, gaining large amounts of genetic material at once. The data of the study indicated it is possible that recombination with a clade 1 virus provided compatibility with human ACE2. Interestingly, the SARS-CoV-2 contains most of the contact points with human ACE2 that are found in clade 1, as well as some amino acid variations that are unique to clades 2 and 3. Taken together with the chimera receptor assay results, the implication is that SARS-CoV-2 arose from recombination between clade 1 and the other clades (https://www.nature.com/articles/s41564-020-0688-y.pdf). Some new data on binding of Pangolin coronavirus to human cells opens it again as an immediate source of SARS-CoV-2. However, the fact that the Pangolin virus binds better to human ACE2 than Pangolin ACE2, opens the unstated possibility that this virus might be a result of an anthroponosis event that transferred coronavirus from humans to Pangolins followed by recombination with another Pangolin virus to yield the current virus under discussion. This is an especially plausible scenario because of the long term illegal animal trade in Pangolins in the region https://www.nature.com/articles/s41467-021-21006-9.pdf.
On Paper Diagnostics for Infectious Agents using Nanobes (Specific Aptamers) which Could Be Used for Rapid Home Diagnosis of SARS-CoV-2 (in saliva) or Adapted Rapidly for New Emerging Biological Agents (May 2015 Longitude Prize Submission)

All the previous Nanobe posts have led to this one to show how the nanotechnology could be applied to the COVID-19 crisis. Aptamers against SARS-CoV-2 have already been made (Yanling Song et al. Discovery of Aptamers Targeting the Receptor-Binding Domain of the SARS-CoV‐2 Spike Glycoprotein. Anal. Chem. 2020, 92, 9895−9900; from China; unlike the US DoD, they have not abandoned this technology). Nanobes could be extended from diagnostics to treatment to autogenous vaccine by immune response redirection as it was intended to do for bio dense against agents that threaten the military where solutions need to be applied to as close as possible to the threat rapidly, even in non-permissive territories under the most primitive and restrictive conditions. The example above was designed for bacteria, not just viruses, to determine viability and antibiotic/antimicrobial sensitivity. A single virus diagnostic, as for SARS-CoV-2, would be a much simpler design.
The Department of Homeland Security is having a industry day today for Mediao Advisory: DHS to Hold Virtual Industry Day Seeking Innovative Solutions for Coronavirus Response. However, they have chosen to exclude nanotechnology and biotechnology, like that described in this blog and already vested in by the US government but abandoned. These are already poised to solve the problems addressed in their solicitation: The topic call is seeking commercially available technology solutions to address the following pandemic-related needs
- Testing & validation to ensure data privacy standards across contact tracing apps
- Video analytics for self-service TSA checkpoints
- Rapid sanitization of large surfaces
- Data aggregation across authoritative and non-authoritative sources
- Enhanced point-of-entry screening methods at DHS facilities
Tuesday, August 18, 2020
09:30 a.m. – 1:00 p.m. PT – Department of Homeland Security staff will discuss mission challenges, technology needs and doing business with SVIP. Speakers include: Melissa Oh, SVIP Managing Director, DHS S&T; Anil John, SVIP Technical Director, DHS S&T; John Fortune, Screening at Speed Program Manager, DHS S&T; Teresa Quitugua, Deputy Director, National Biosurveillance Integration Center (NBIC); William Pharis, Program Manager, DHS S&T; Kevin Grottle, Program Manager, DHS S&T.
What Defending Against a Real Aerosol and Lethal Infectious Agent is Like: Anthrax Spores

It’s hard to see anything that is positive about COVID-19. It, unlike agents like anthrax spores, is airborne but not a true aerosol transmitted agent. It can be effectively blocked by masks, distancing and good hand and other hygiene.
Hot off the Presses: Positive Immune Response is More Robust to SARS-CoV-2 Than Previously Thought
T cell memory and mucosal immunity develop in asymptomatic as well as mildly symptomatic individuals infected with SARS-CoV-2. Anti-CoV-2 antibody was detected in serum and saliva, with peak IgG levels by 16-30 days after disease onset. Whereas anti-CoV-2 IgA antibodies rapidly decayed, IgG antibodies remained up to 115 days in both saliva and serum (https://www.medrxiv.org/content/10.1101/2020.08.01.20166553v1 and https://www.medrxiv.org/content/10.1101/2020.07.18.20155374v1). Those recovered from mild COVID-19 developed SARS-CoV-2-specific IgG antibody and neutralizing plasma, as well as virus-specific memory B and T cells which persisted, and in some cases increased over three months following symptoms’ appearance. Furthermore, the SARS-CoV-2-specific memory T and B cells exhibited potent antiviral immunity: memory T cells secreted IFN-γ and increased in number after second viral exposure, while memory B cells expressed receptors that neutralized virus and led to expressed neutralizing antibodies (https://www.medrxiv.org/content/10.1101/2020.08.11.20171843v2). Most importantly, SARS-CoV-2-specific T cells were detectable in antibody-seronegative exposed family members and recovered individuals with a history of asymptomatic and mild COVID-19. The data shows that SARS-CoV-2 induces robust, broad and highly functional memory T cell responses, implying natural exposure, vaccination, or infection may prevent reinfection and severe COVID-19 (https://www.cell.com/cell/pdf/S0092-8674(20)31008-4.pdf?_returnURL=https%3A%2F%2Flinkinghub.elsevier.com%2Fretrieve%2Fpii%2FS0092867420310084%3Fshowall%3Dtrue .
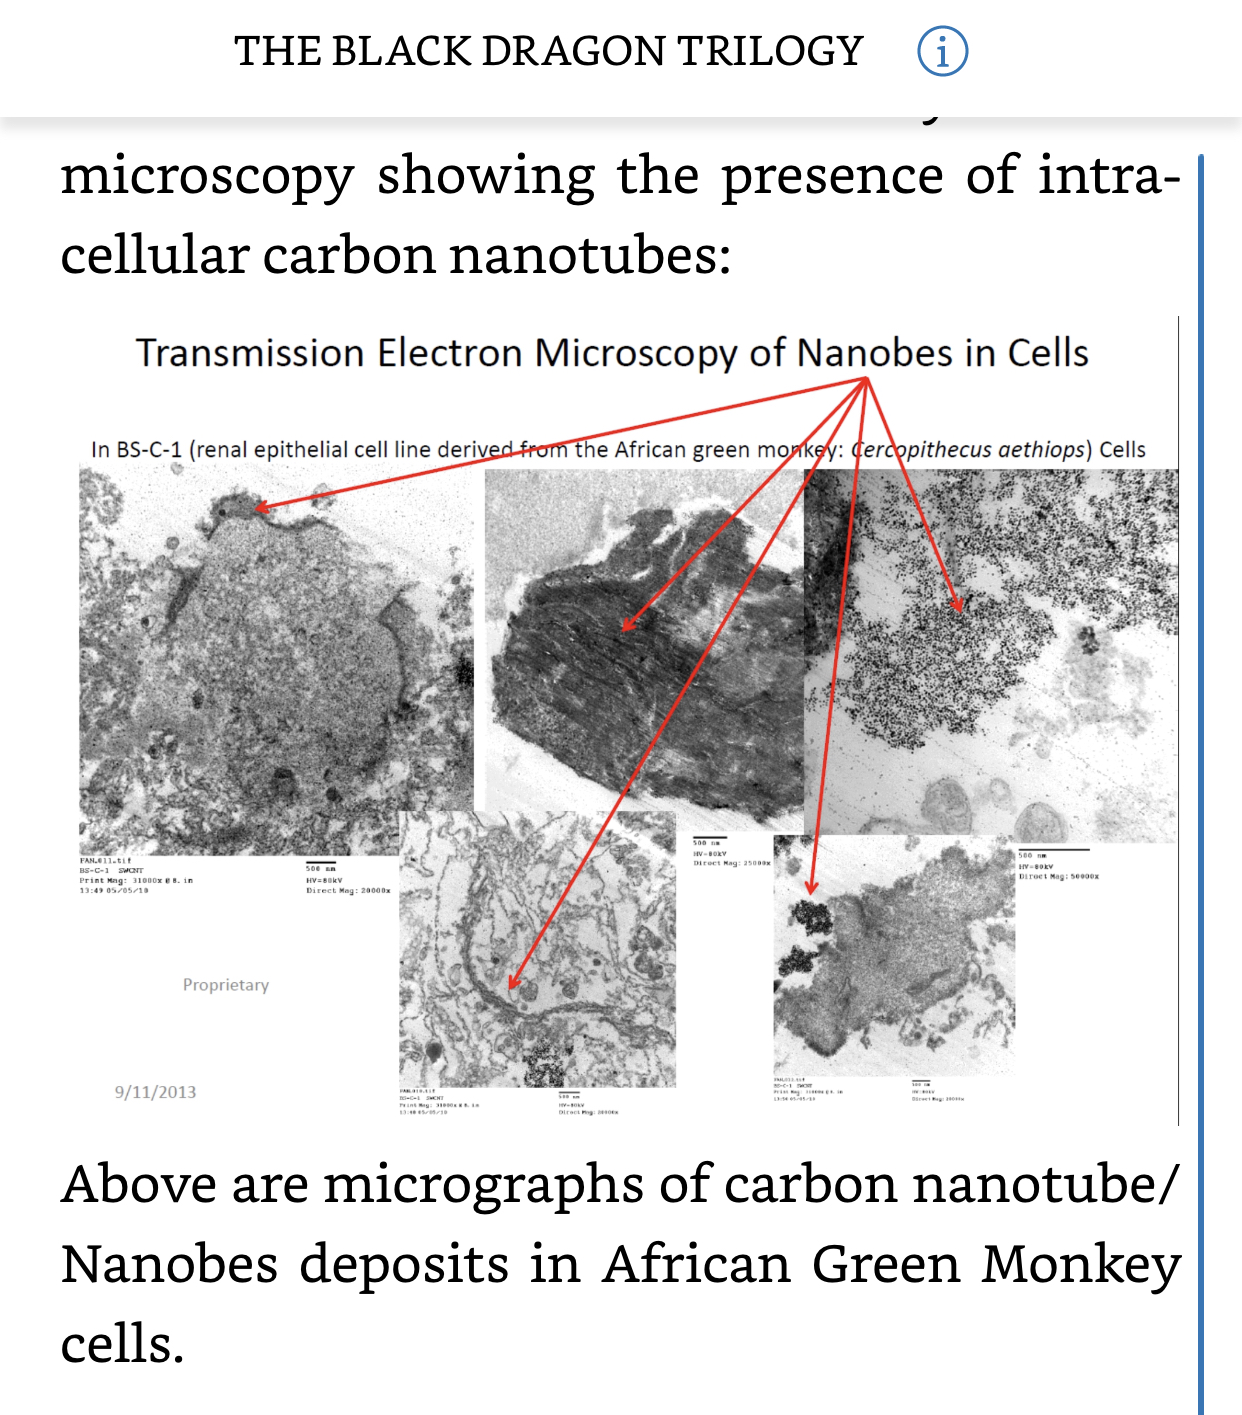
Carbon Nanotube (Crystalline) Nanobes in Green Monkey Cells and PCR Evidence (Electrophoretic Gel) of DALM Polymer Nanobes Transferring Genes to Human Kidney Cells
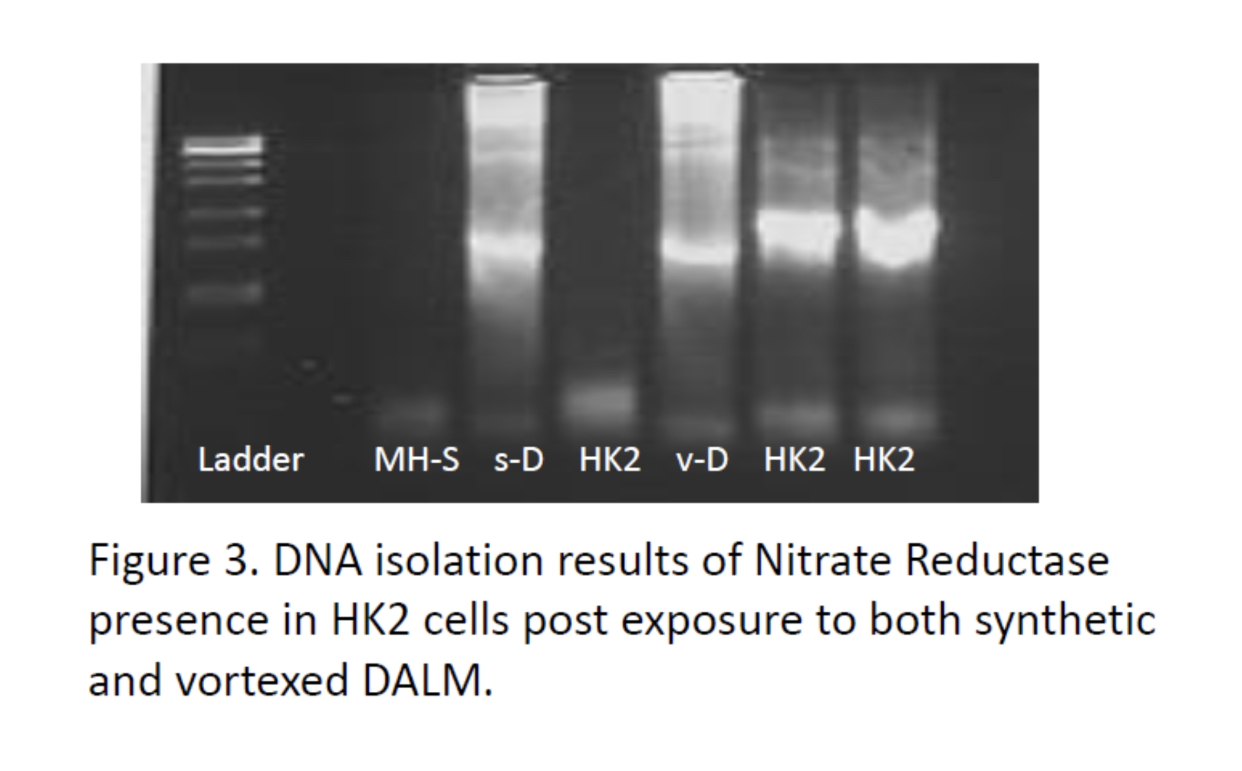
S-D was synthetic DALM Nanobes and v-D was biosynthetic replicate Nanobes.
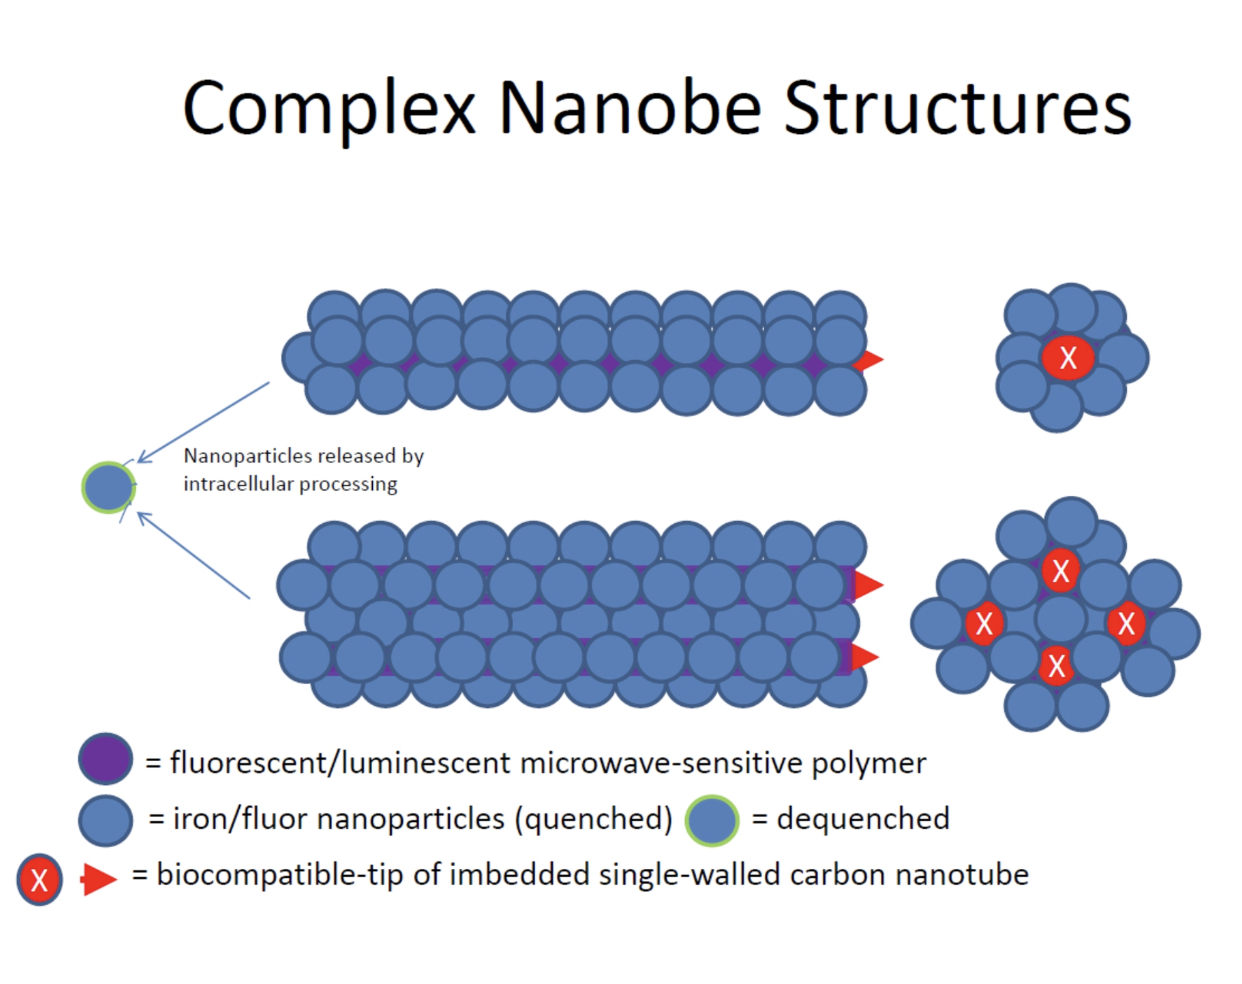
Crystalline Structure of Synthetics Nanobes: Viral-like Link Between the Chemical and the Living
Finding Unknown Microbes with Nanobe Aptamer Components: Bringing Them Back Alive
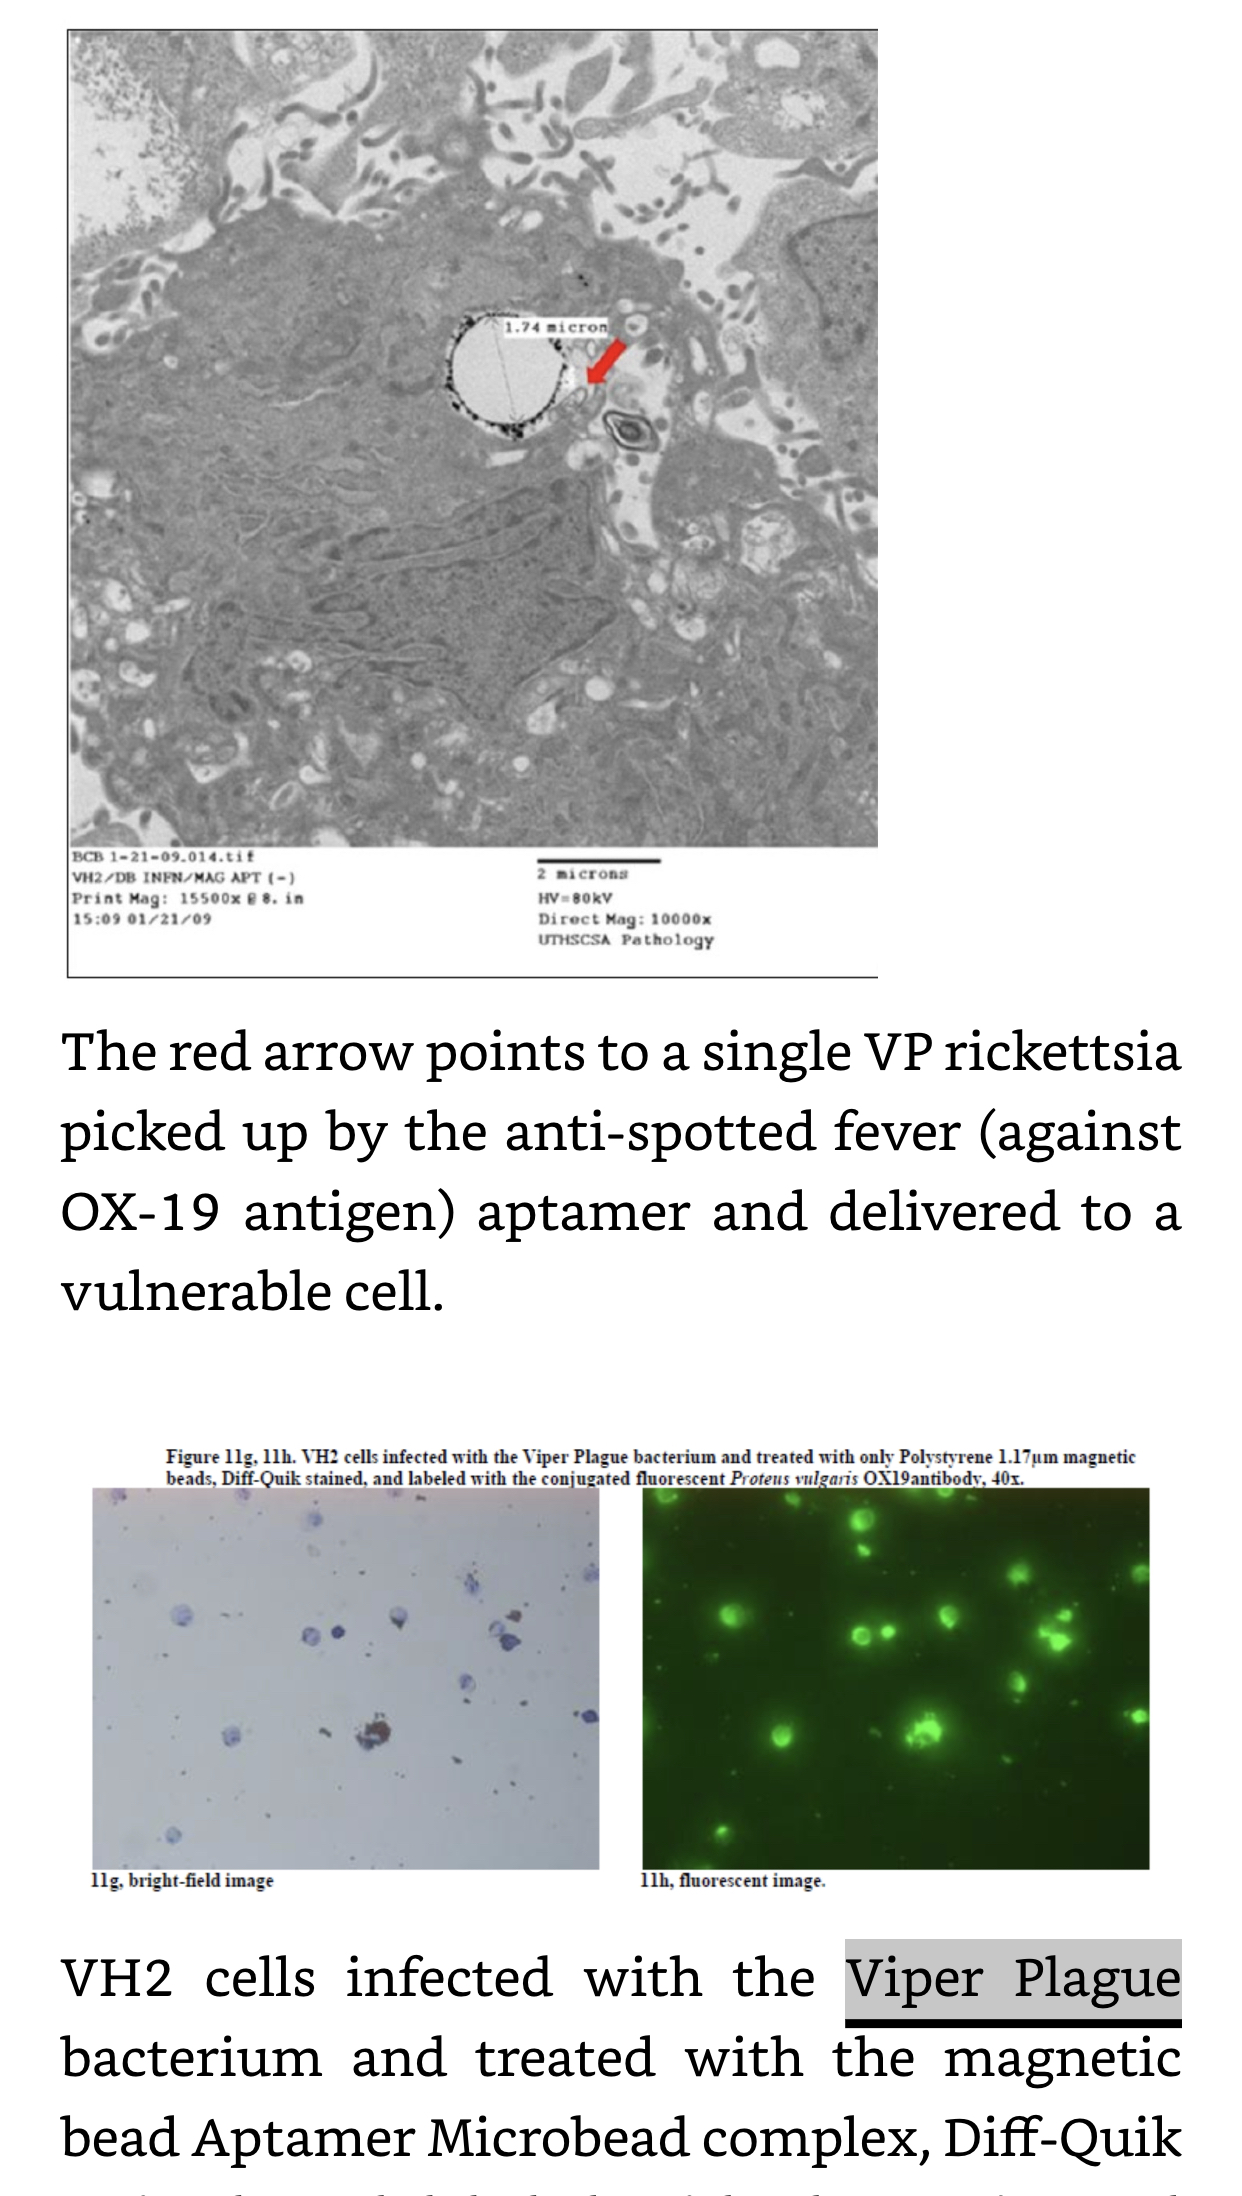
Nanoparticles with broad spectrum of species-binding coating microbeads captures (magnetically) living unknown spotted fever- like microbe from Ghana West Africa and brings it back alive for successful isolation and culture (growing microbe tracked in cell culture by fluorescent tag).
Developing Fluorescent Nanobes for Detecting Anthrax Spores

Cold Plasma Gas Surface and Air Infectious Agent Decontamination
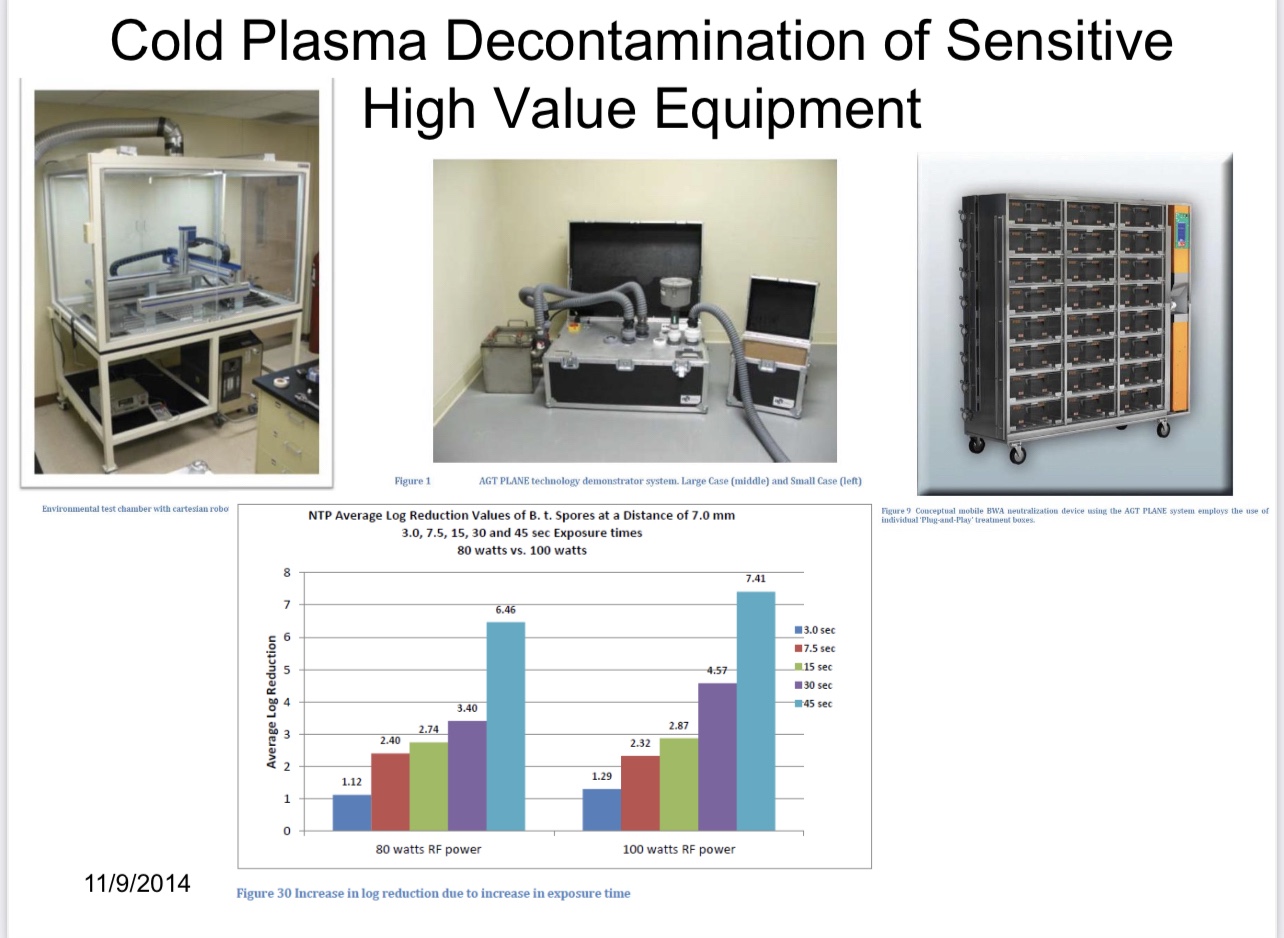

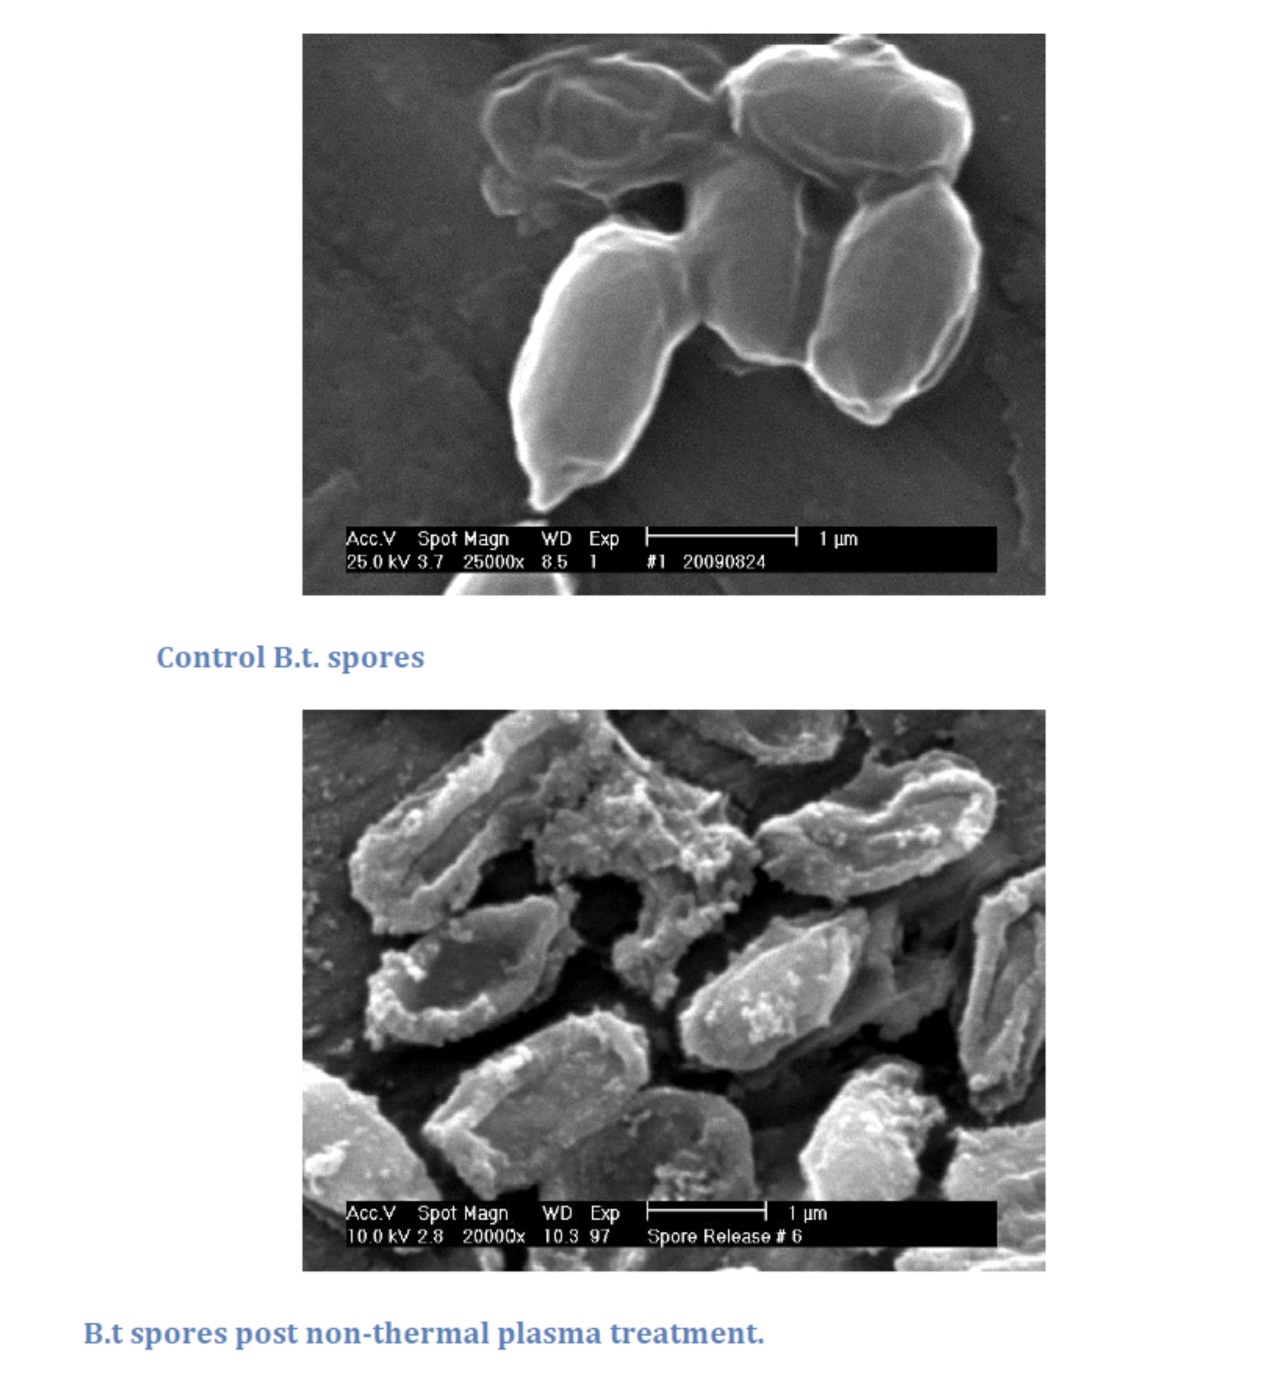

Safe on skin,
Cold Plasma could also be used to scrub air of SARS-CoV-2 virus. Growing out of the USAF Counterproliferation program.
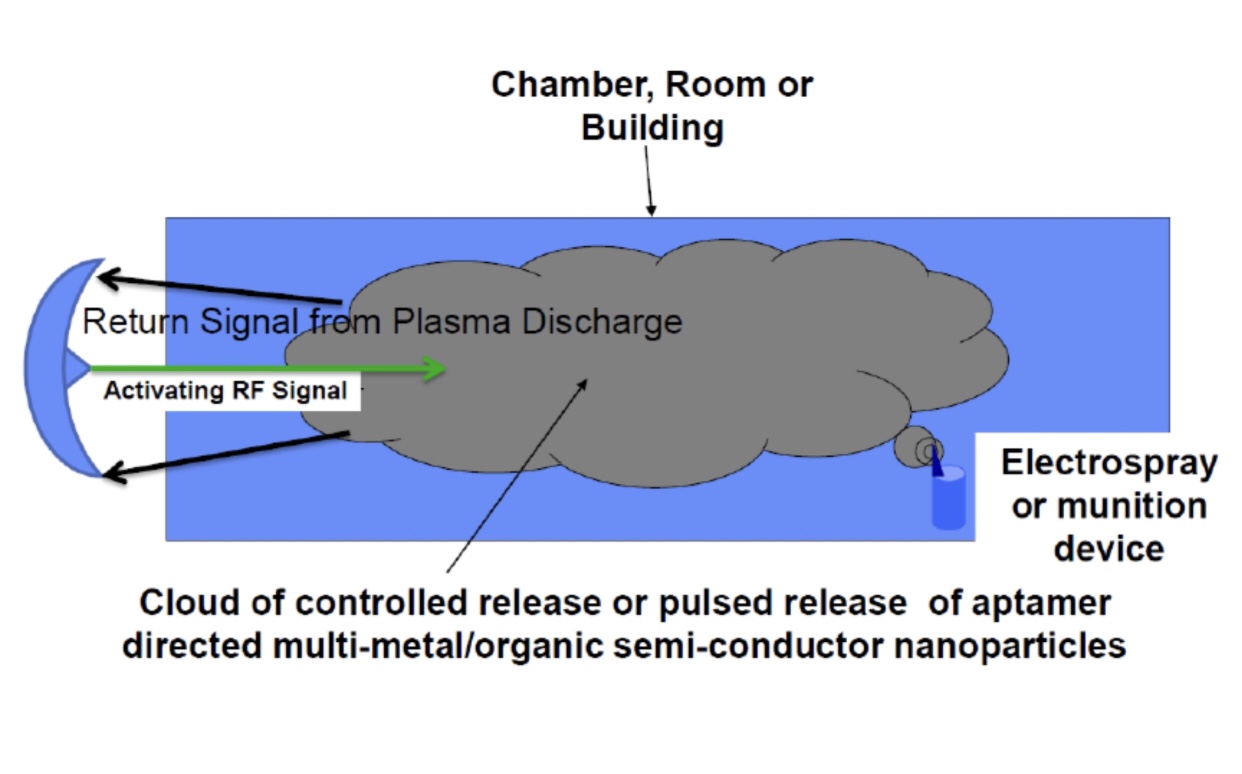

Cold plasma has promise for use against brain cancer. https://www.labroots.com/trending/cancer/18893/using-plasma-scalpels-chemotherapy-brain-cancer

